




Introduction to AAV
Incidence & prevalence
AAV is a rare, severe small vessel vasculitis that affects multiple organs and has a high acute mortality risk.1
Types of AAV
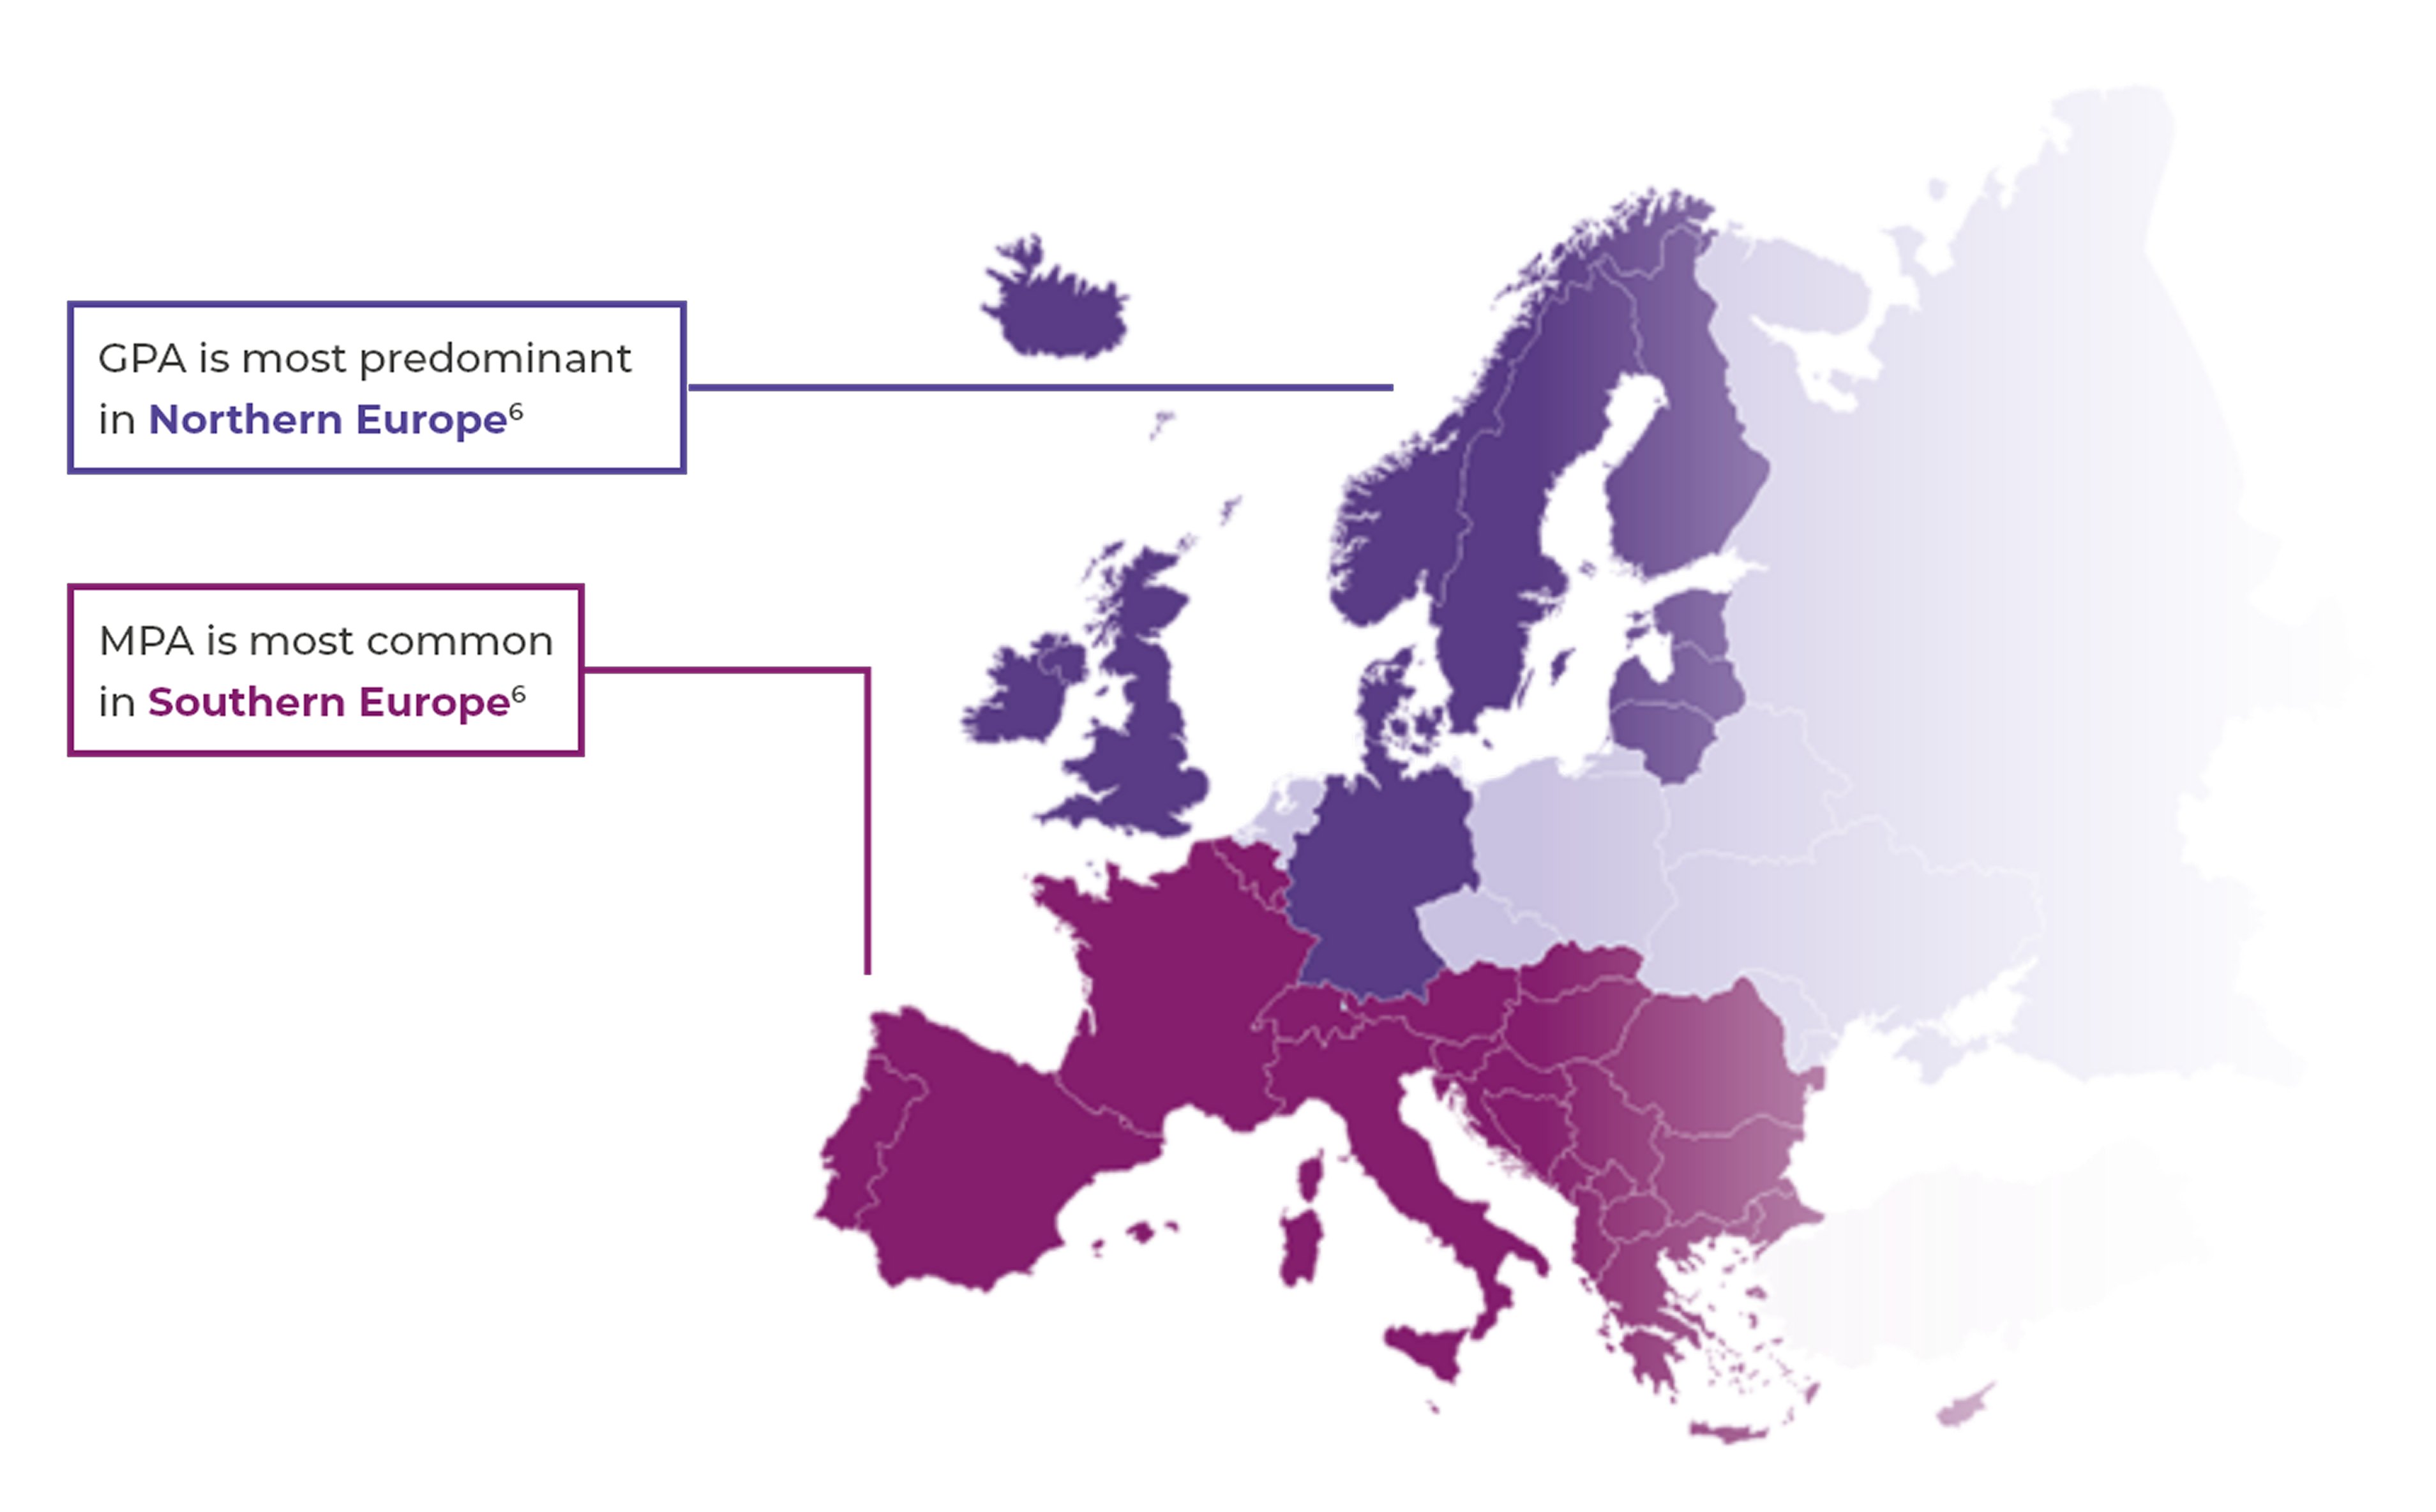
The two most common subtypes of AAV are granulomatosis with polyangiitis (GPA, previously called Wegener’s) and microscopic polyangiitis (MPA). The other subtype is eosinophilic granulomatosis with polyangiitis (EGPA, previously called Churg-Strauss syndrome).2,3 This website will focus mainly on GPA and MPA.
AAV is a rare disease2
- Global prevalence: 30–218 per million4
- European incidence: 13–20 per million per year2,4
AAV occurrence
- AAV can affect both younger and older people, but is rare in children and young people and incidence rises with age2,5
- AAV occurs slightly more frequently in men (annual incidence rate approximately 60%) than in women2,5
References & footnotes

Abbreviations
AAV, ANCA-associated vasculitis; ANCA, anti-neutrophil cytoplasmic antibody; EGPA, eosinophilic granulomatosis with polyangiitis; GPA, granulomatosis with polyangiitis; MPA, microscopic polyangiitis
References
- Hutton HL, et al. ANCA-Associated Vasculitis: Pathogenesis, Models, and Preclinical Testing. Semin Nephrol 2017;37(5):418–35.
- Watts RA, et al. Classification, epidemiology and clinical subgrouping of antineutrophil cytoplasmic antibody (ANCA)-associated vasculitis. Nephrol Dial Transplant 2015;30(Suppl 1):i14–22.
- Yates M, et al. EULAR/ERA-EDTA recommendations for the management of ANCA-associated vasculitis. Ann Rheum Dis 2016;75(9):1583–94.
- Mohammad AJ. An update on the epidemiology of ANCA-associated vasculitis. Rheumatology (Oxford) 2020;59:iii42–50.
- Watts RA, et al. Epidemiology of systemic vasculitis: a ten-year study in the United Kingdom. Arthritis Rheum 2000;43(2):414–9.
- Watts RA, et al. The global burden of anti-neutrophil cytoplasmic antibody vasculitis: High but unquantified. Rheumatology (Oxford) 2017;56(9):1439–40.
GCC-AVA-2500012 | Date of preparation: October 2025
Introduction to AAV
Incidence & prevalence
AAV is a rare, severe small vessel vasculitis that affects multiple organs and has a high acute mortality risk.1
Types of AAV
The two most common subtypes of AAV are granulomatosis with polyangiitis (GPA, previously called Wegener’s) and microscopic polyangiitis (MPA). The other subtype is eosinophilic granulomatosis with polyangiitis (EGPA, previously called Churg-Strauss syndrome).2,3 This website will focus mainly on GPA and MPA.
AAV is a rare disease2
- Global prevalence: 30–218 per million4
- European incidence: 13–20 per million per year2,4
AAV occurrence
- AAV can affect both younger and older people, but is rare in children and young people and incidence rises with age2,5
- AAV occurs slightly more frequently in men (annual incidence rate approximately 60%) than in women2,5
References & footnotes
Abbreviations
AAV, ANCA-associated vasculitis; ANCA, anti-neutrophil cytoplasmic antibody; EGPA, eosinophilic granulomatosis with polyangiitis; GPA, granulomatosis with polyangiitis; MPA, microscopic polyangiitis
References
- Hutton HL, et al. ANCA-Associated Vasculitis: Pathogenesis, Models, and Preclinical Testing. Semin Nephrol 2017;37(5):418–35.
- Watts RA, et al. Classification, epidemiology and clinical subgrouping of antineutrophil cytoplasmic antibody (ANCA)-associated vasculitis. Nephrol Dial Transplant 2015;30(Suppl 1):i14–22.
- Yates M, et al. EULAR/ERA-EDTA recommendations for the management of ANCA-associated vasculitis. Ann Rheum Dis 2016;75(9):1583–94.
- Mohammad AJ. An update on the epidemiology of ANCA-associated vasculitis. Rheumatology (Oxford) 2020;59:iii42–50.
- Watts RA, et al. Epidemiology of systemic vasculitis: a ten-year study in the United Kingdom. Arthritis Rheum 2000;43(2):414–9.
- Watts RA, et al. The global burden of anti-neutrophil cytoplasmic antibody vasculitis: High but unquantified. Rheumatology (Oxford) 2017;56(9):1439–40.
GCC-AVA-2500012 | Date of preparation: October 2025
Introduction to AAV
System organ damage
AAV can result in systemic organ damage and failure, with the kidney and lung as major targets1-3
AAV can result in damage to vital organs such as the lungs, kidneys, nervous system, gastrointestinal system, skin, eyes and heart.3,4 Both GPA and MPA show a lot of clinical commonality, whereas EGPA is distinctly different.2
As many as 23% (n=11/48) of PR3- and MPO-ANCA positive patients who require RRT at the time of diagnosis die within 6 months and 29% (n=14/48) do not regain renal function.5* In patients with renal involvement at diagnosis, ESRD occurs in 13% (n=9/72) of PR3- and MPO-ANCA positive patients within 3 years of diagnosis. Compared with a short prodromal phase, patients with a long prodromal phase (>22 weeks between first AAV symptoms and diagnosis) are more likely to have proteinuria present at 6 months and are at double the risk of 3-year ESRD, which underlines the importance of early diagnosis in order to improve renal outcomes.6†
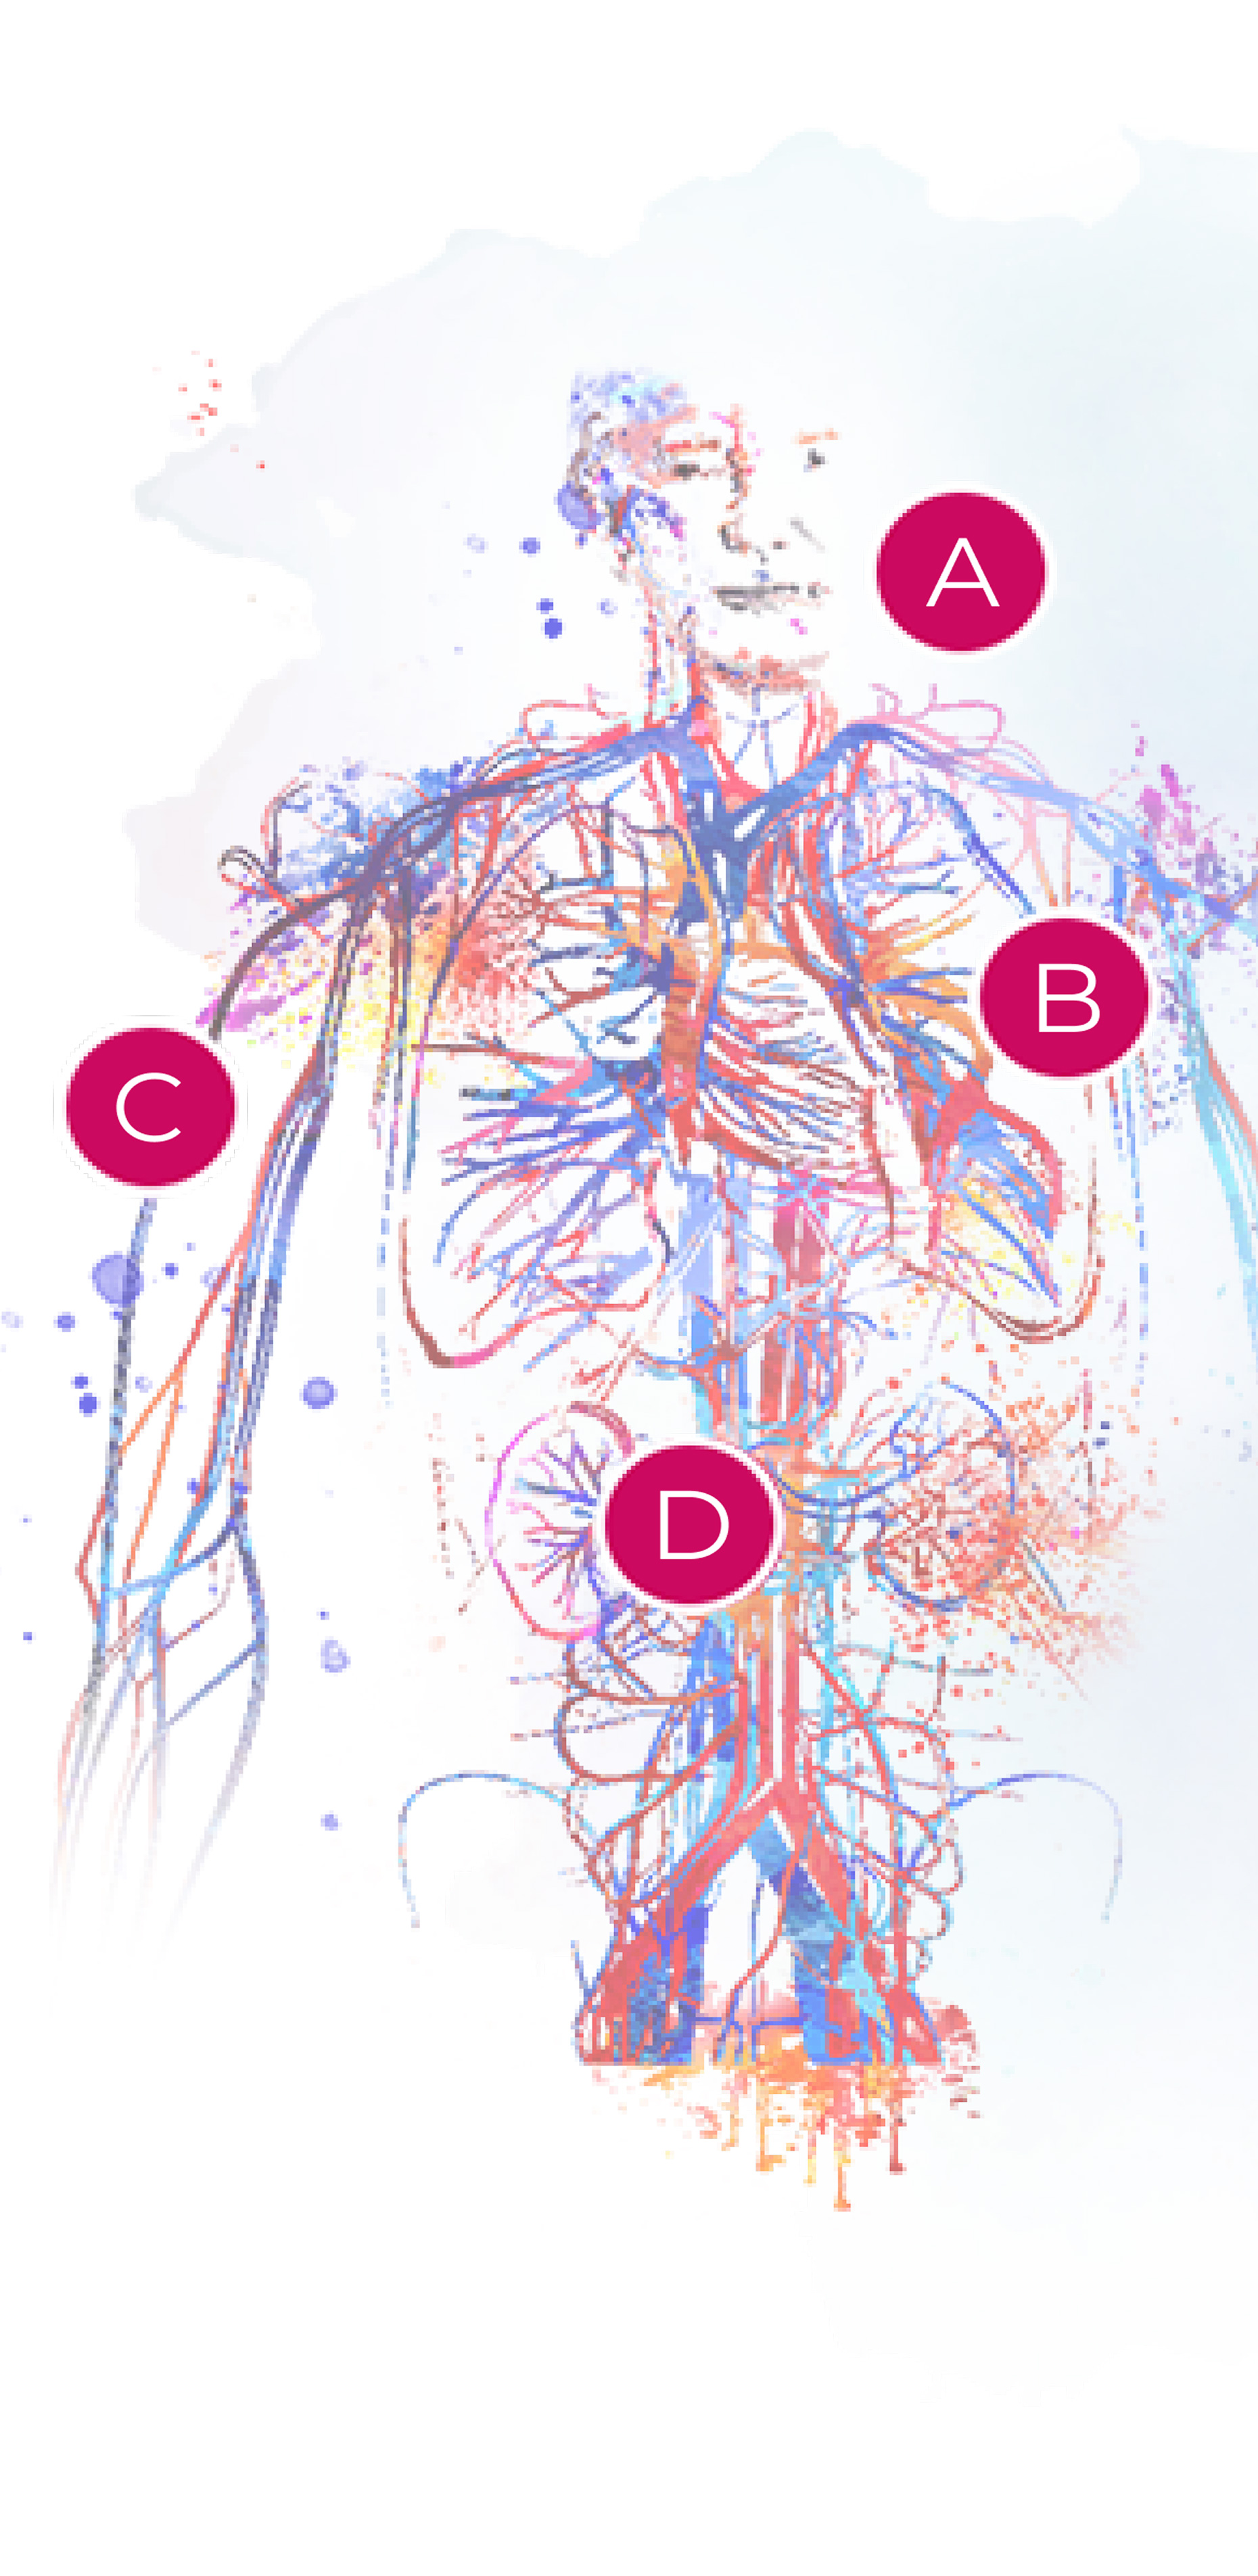
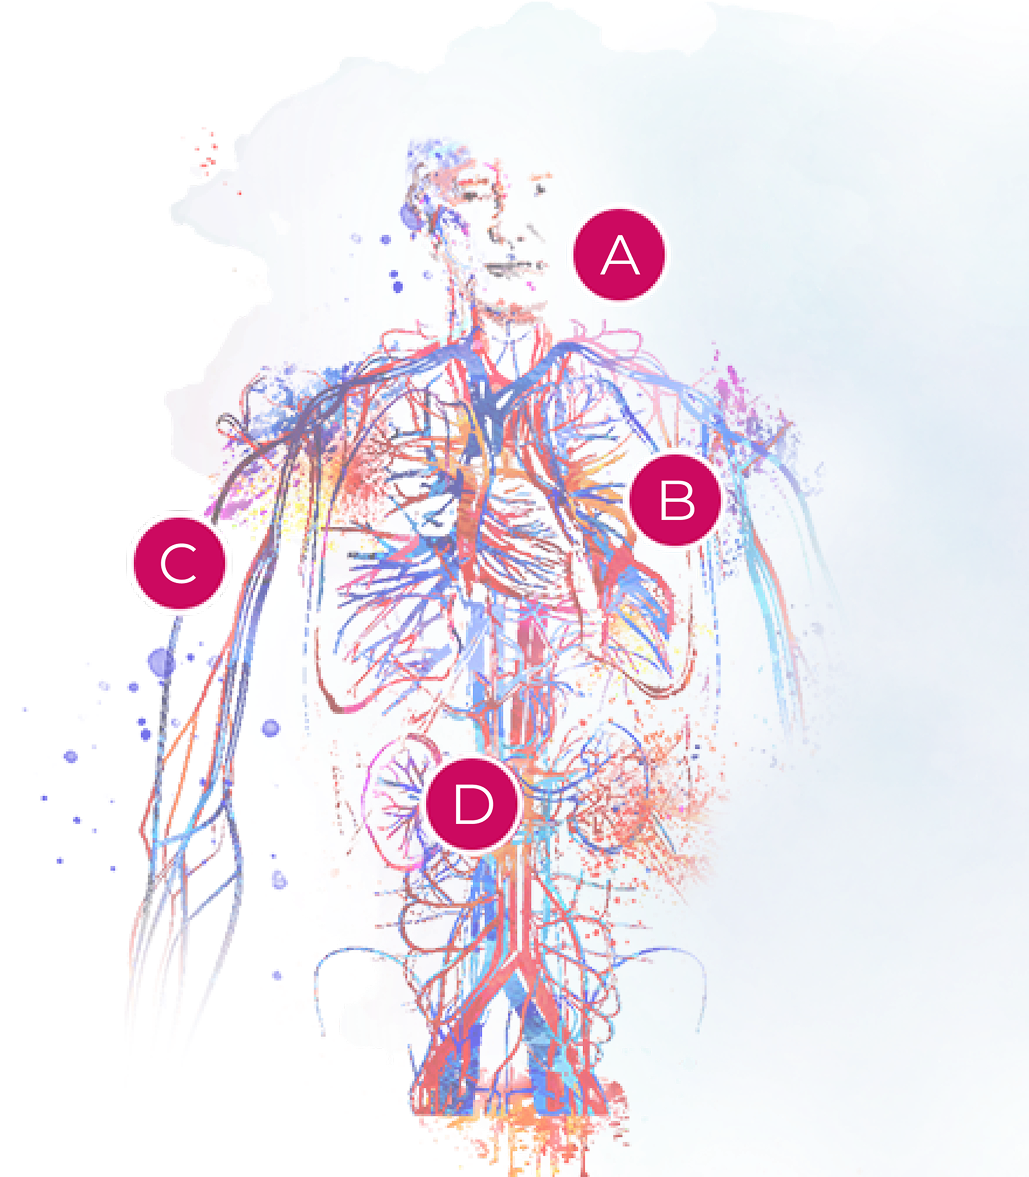
A. ENT2
Frequency
GPA: 50–95%; MPA: 2–30%; EGPA: 20–80%
Manifestations
GPA: Crusting rhinitis, destructive sinusitis, saddle-nose deformity, nasal septum deformity, otitis media
MPA: Not specific, not destructive, not granulomatous
EGPA: Allergic rhinitis, non-destructive sinus polyposis
B. Lungs2
Frequency
GPA: 60–80%; MPA: 60–80%; EGPA: 50%
Manifestations
GPA: Lung plain and/or excavated nodules, alveolar haemorrhage, bronchial and/or subglottic stenosis
MPA: Alveolar haemorrhage
EGPA: Transient patchy infiltrates and eosinophil pleural effusion, but rarely nodules
C. Skin2
Frequency
GPA: 10–50%; MPA: 35–60%; EGPA: 50–70%
Manifestations
GPA and MPA: Purpura
EGPA: Purpura, pseudourticarial rash
D. Kidneys2
Frequency
GPA: 60–80%; MPA: 80%; EGPA: 20%
Manifestations
GPA, MPA and EGPA: Pauci-immune necrotising extra-capillary glomerulonephritis
GPA and MPA patients accumulate organ damage from a combination of vasculitis activity and glucocorticoid-related AEs7–9
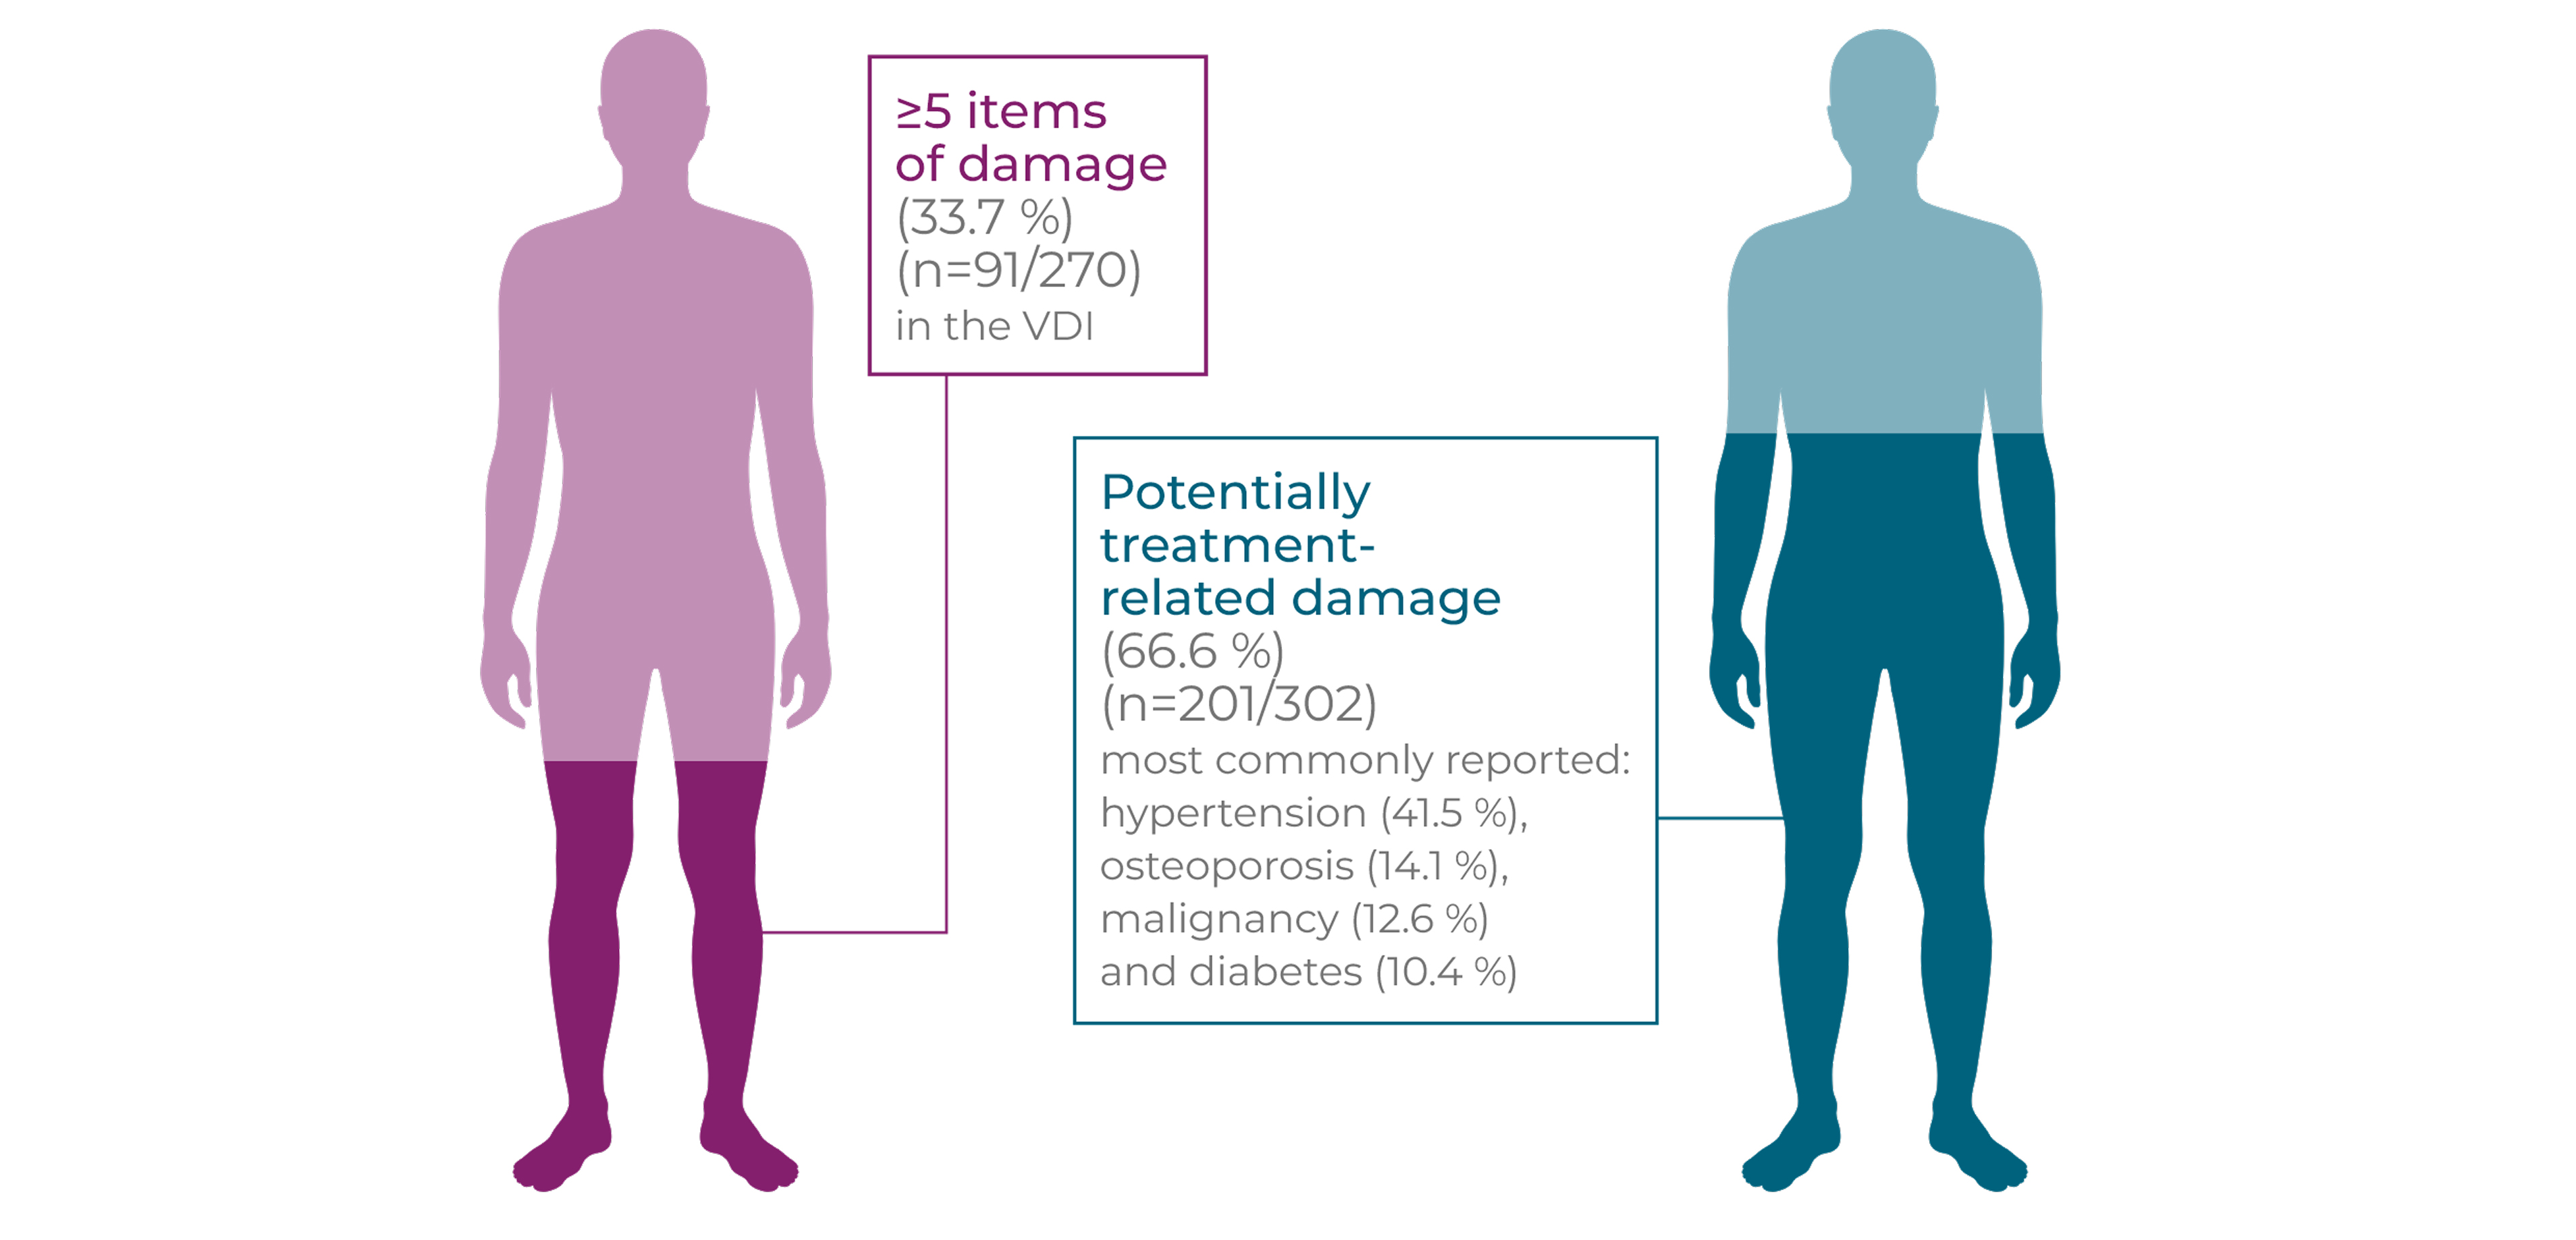
Long-term and repeated high-dose glucocorticoid use is associated with an increased risk of new onset/worsening of diabetes mellitus, hypertension, osteoporosis, avascular necrosis of bone, malignancy, cataracts and other debilitating side effects.7,8‡§ In a study following newly diagnosed GPA and MPA patients for up to 7 years, the frequency of damage, including potentially treatment-related damage, rose over time (p<0.01). Patients initially experience early increased damage following diagnosis (n=270), with 81.5% (n=220/270) of patients experiencing ≥1 item in the VDI at 6 months compared to 24.4% (n=66/270) of patients at baseline, with renal (proteinuria and GFR <50 mL/minute) and cardiovascular (hypertension) damage the most frequent. Severe damage, a VDI score ≥5, increases over time and at long-term follow-up 33.7% (n=91/270) of patients had severe damage. Hypertension was the most commonly reported item at long-term follow-up. At baseline, 4.8% (n=13/270) of patients had hypertension. Within 6 months, this rose to 17.0% (n=46/270) and at long-term follow-up 41.5% (n=112/270) of patients had hypertension (p<0.01 ).8§
High levels of long-term vasculitis damage were independently associated with increased cumulative glucocorticoid use (p=0.016).9§
This serious morbidity is accompanied by a significantly increased long-term mortality risk, with a hazard ratio of 2.41 (95% CI: 1.74–3.34) in GPA patients compared with age- and sex-matched controls.8–10§**
At a mean of 7 years post diagnosis in patients with GPA or MPA…8§
References & footnotes
Footnotes
*AAV patients with (n=212; mean age: 58 years; PR3-ANCA positive: n=138; MPO-ANCA positive: n=65; ANCA negative: n=9) and without (n=61; mean age: 52 years) renal involvement (active urinary sediment, proteinuria, impaired renal function or biopsy) diagnosed and treated with AAV at a single centre in the Netherlands between January 1990 and December 2007 who were followed until death, loss to follow-up or December 2010.5
†Retrospective data collected from patients (n=72; mean age: 64 years) with a clinical AAV diagnosis (Chapel Hill disease definitions and PR3-/MPO-ANCA positive) and renal involvement at diagnosis (rise in serum creatinine >30% and/or erythrocyturia [≥10 red blood cells per high-power field and/or red blood cell casts]) in a single-centre cohort (Northwest Clinics, Netherlands) between 1 February 2005 and 1 February 2015.6
‡Patients (n=524) with newly diagnosed GPA or MPA (adapted Chapel Hill disease definitions) recruited into four EUVAS RCTs in 42 hospitals in 11 European countries and Mexico between 1995 and 2005, and followed for 1 year.7
§Patients (n=735 recruited; mean age: 57.6 years) with newly diagnosed GPA (55%) or MPA (45%; adapted 1994 Chapel Hill disease definitions, clinical presentation, and positive ANCA serology and/or histology) recruited into six EUVAS RCTs between 1995 and 2009. Long-term follow-up data (n=535 eligible patients; GPA: 53%; MPA: 48%; mean age: 57.7 years) were available from four RCTs (n=467/535 with data available; mean follow-up: 7.3 years) with VDI data from 302/535 patients (GPA: 55%; MPA: 45%; mean age: 56.8 years; mean follow-up: 7.1 years) and VDI + glucocorticoid data from 296/535 patients (GPA: 56%; MPA: 44%: mean age: 56.6 years).8,9
**Data collected from patients with a first diagnosis of incident GPA (n=465; mean age: 60.3 years) and non-GPA-matched (sex, age, year of birth and GPA diagnosis year) controls (n=4613; mean age: 60.3 years) from the United Kingdom (The Health Improvement Network) between 1992 and 2013. Mortality data were obtained from the 2003–13 cohort.10
Abbreviations
AAV, ANCA-associated vasculitis; AE, adverse event; ANCA, anti-neutrophil cytoplasmic antibody; CI, confidence interval; EGPA, eosinophilic granulomatosis with polyangiitis; ENT, ear, nose and throat; ESRD, end-stage renal disease; EUVAS, European Vasculitis Study Group; GFR, glomerular filtration rate; GI, gastrointestinal; GPA, granulomatosis with polyangiitis; MPA, microscopic polyangiitis; MPO, myeloperoxidase; PR3, proteinase 3; RRT, renal replacement therapy; RCT, randomised controlled trial; VDI, Vasculitis Damage Index
References
- Hutton HL, et al. Semin Nephrol 2017;37(5):418–35.
- Pagnoux C. Eur J Rheumatol 2016;3(3):122–33.
- Kitching A, et al. Nat Rev Dis Primers 2020;6(1):71.
- Al-Hussain T, et al. Adv Anat Pathol 2017;24(4):226–34.
- De Joode AAE, et al. Clin J Am Soc Nephrol 2013;8(10):1709–17.
- Houben E, et al. BMC Nephrol 2017;18(1):378.
- Little MA, et al. Ann Rheum Dis 2010;69(6):1036−43.
- Robson J, et al. Ann Rheum Dis 2015;74(1):177–84.
- Robson J, et al. Rheumatology (Oxford) 2015;54(3):471–81.
- Wallace ZS, et al. Semin Arthritis Rheum 2016;45(4):483–9.
Additional
DE-FCM-2100195
Introduction to AAV
Mortality & morbidity
AAV leads to an increased risk of mortality, especially in the first year after diagnosis1,2*
In the first year after a GPA or MPA diagnosis (n=524), the mortality rate is 10.7% (n=56)1*
Of these patients: Half (50%) of mortality in the first year is due to treatment-related infection1
In clinical trial settings, the cumulative survival rate at 2 and 5 years in patients with newly diagnosed GPA and MPA is 85% and 78%, respectively.3†
Population-based data suggest that the long-term mortality rate in patients with AAV has improved considerably over the past two decades, but is still not as good as matched controls.2‡
In a study following individuals for a median 5.2 years, the mortality rate in incident GPA or MPA patients receiving current treatment was 2.6 times higher than an age- and sex-matched general population (p<0.0001).3†
References & footnotes
Footnotes
*Patients (n=524) with newly diagnosed GPA or MPA (adapted Chapel Hill disease definitions) recruited into four EUVAS RCTs in 42 hospitals in 11 European countries and Mexico between 1995 and 2005, and followed for 1 year.1
†Patients (n=535; median age: 61 years) with newly diagnosed GPA (53%) or MPA (47%; adapted 1994 Chapel Hill disease definitions, clinical presentation, and positive ANCA serology and/or histology) recruited into four EUVAS RCTs in 70 general and university hospitals in 15 countries between 1995 and 2002 with a median 5.16 years of follow-up for all patients. A control cohort was matched for age, sex, year and country.3
‡Data collected from patients with a first diagnosis of incident GPA (n=465; mean age: 60.3 years) and non-GPA matched (sex, age, year of birth and GPA diagnosis year) controls (n=4613; mean age: 60.3 years) from the United Kingdom (The Health Improvement Network) between 1992 and 2013, and divided into two cohorts based on the year of diagnosis (1992–2002 and 2003–2013).2
Abbreviations
AAV, ANCA-associated vasculitis; ANCA, anti-neutrophil cytoplasmic antibody; EUVAS, European Vasculitis Study Group; GPA, granulomatosis with polyangiitis; MPA, microscopic polyangiitis; RCT, randomised controlled trial
References
- Little MA, et al. Ann Rheum Dis 2010;69(6):1036−43.
- Wallace ZS, et al. Semin Arthritis Rheum 2016;45(4):483–9.
- Flossmann O, et al. Ann Rheum Dis 2011;70(3):488–94.
Introduction to AAV
Referral, diagnosis & follow-up
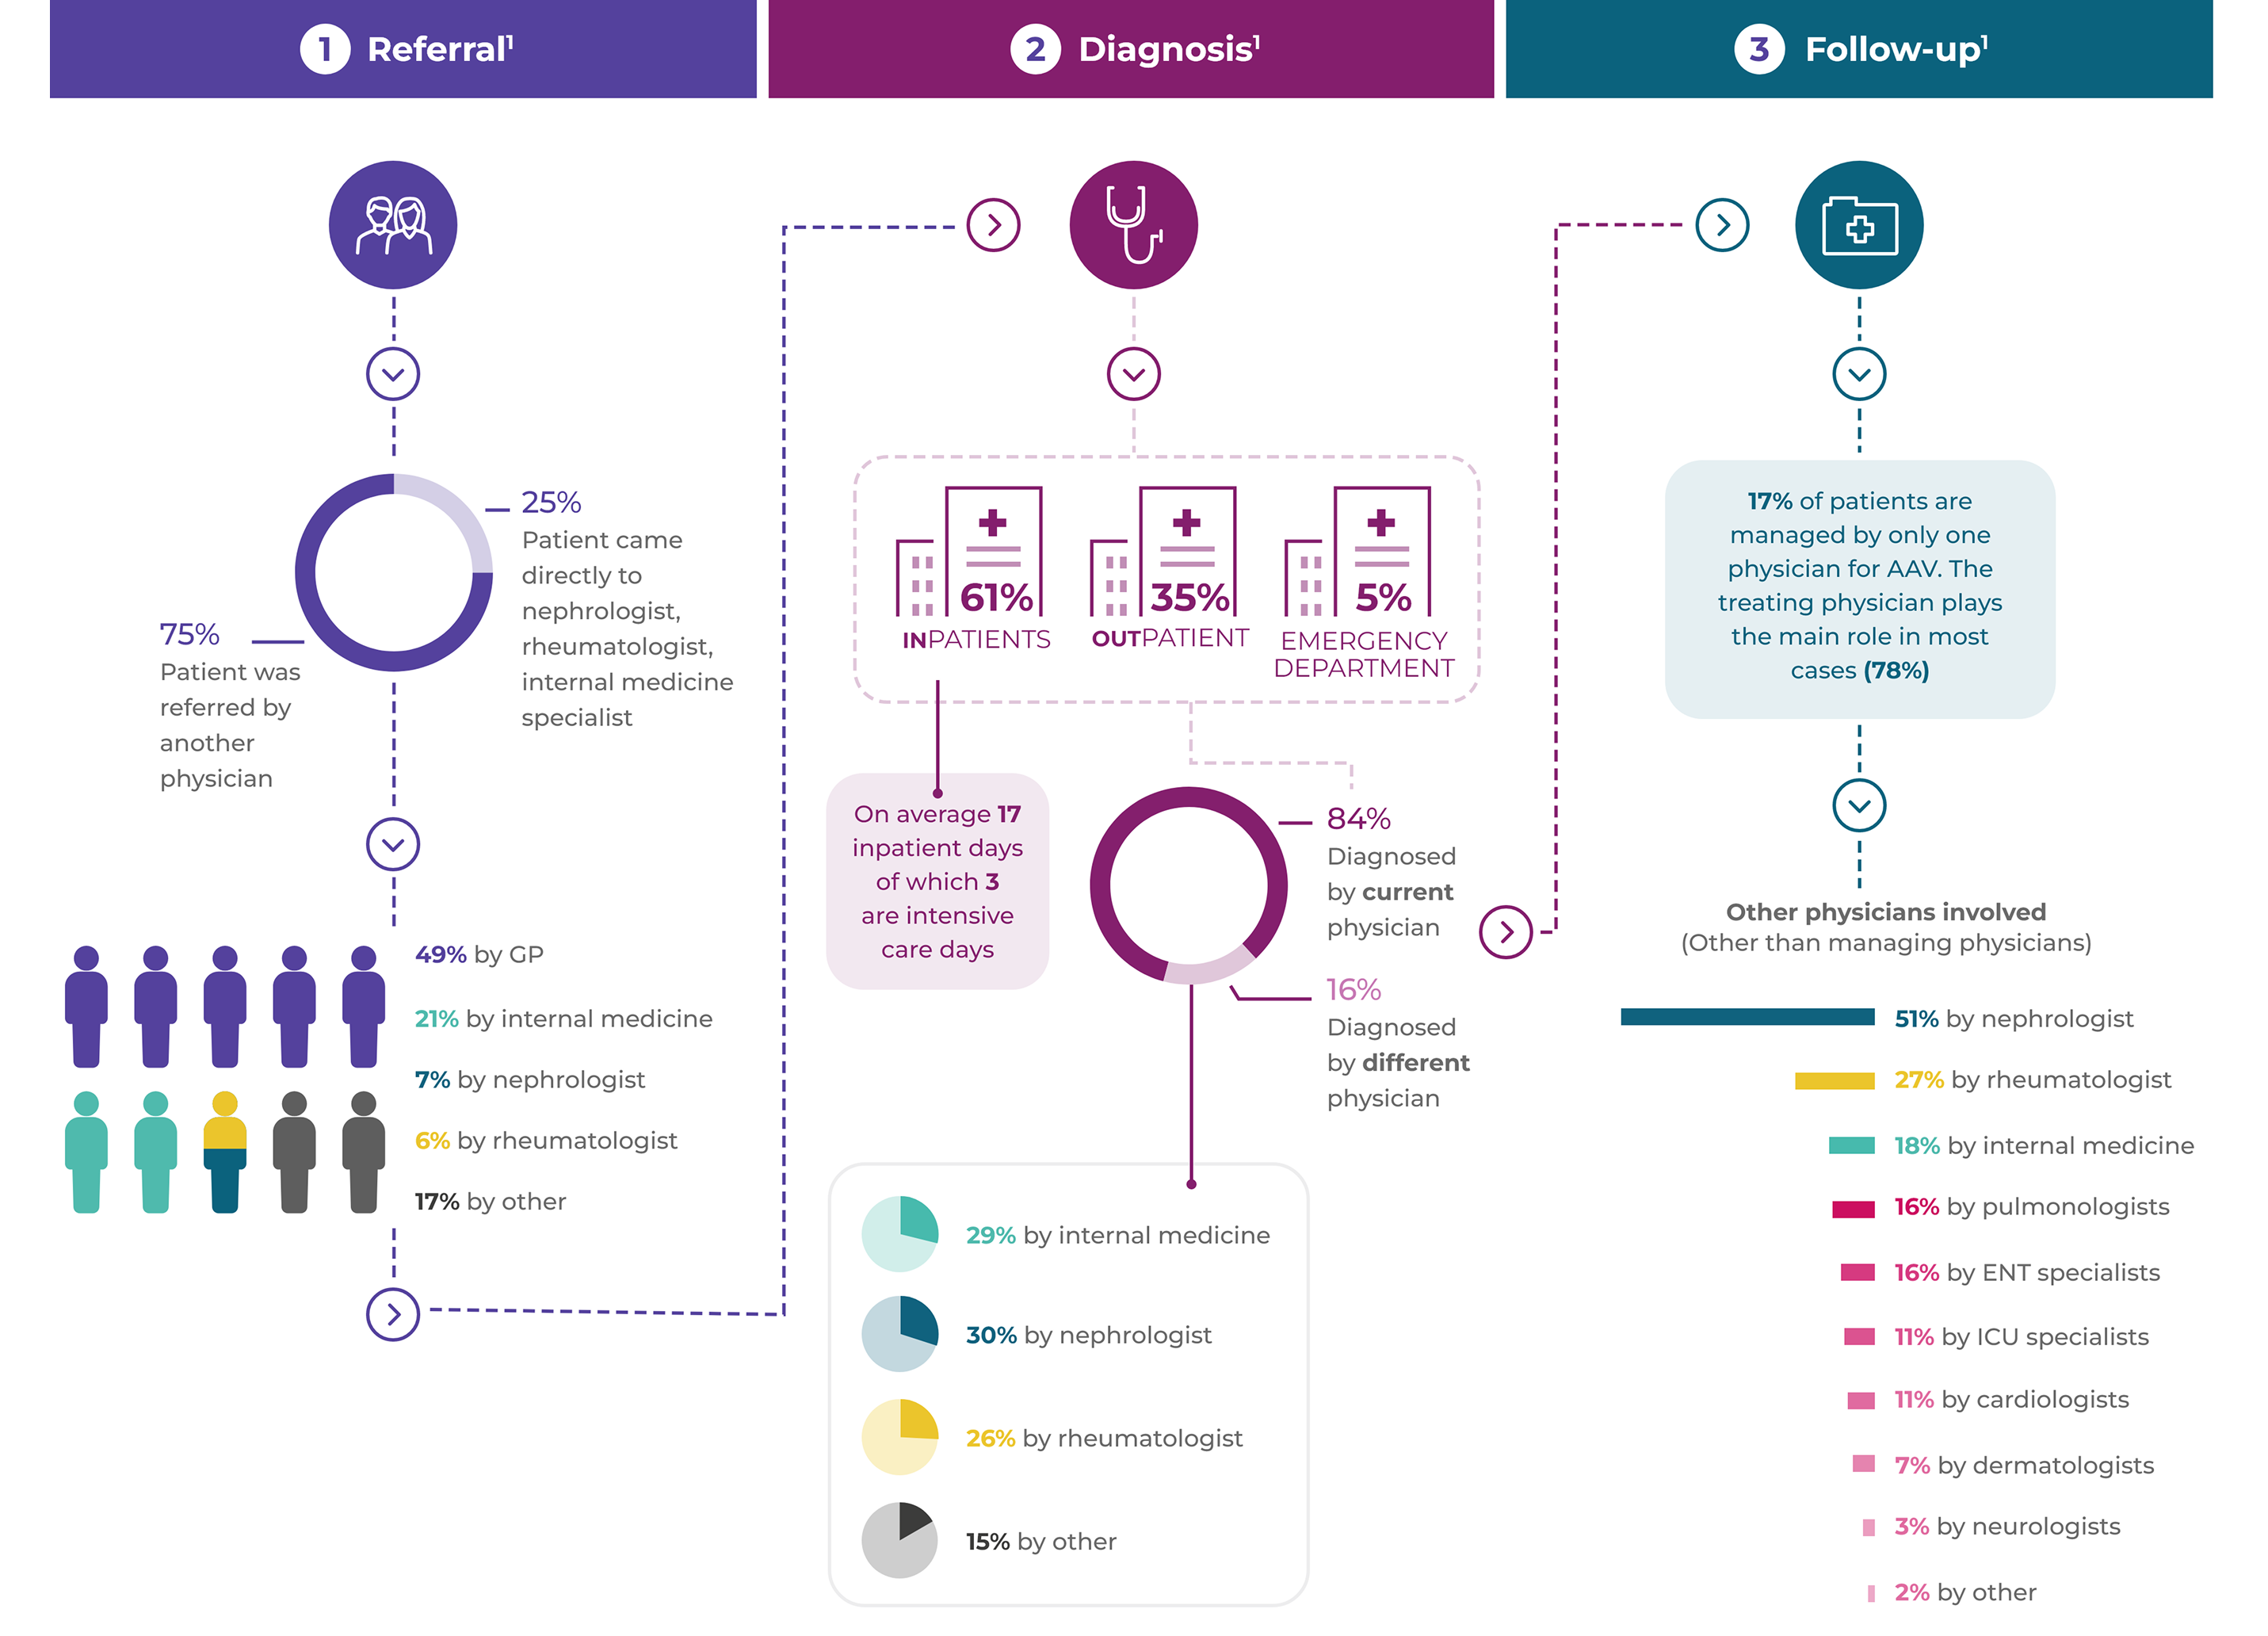
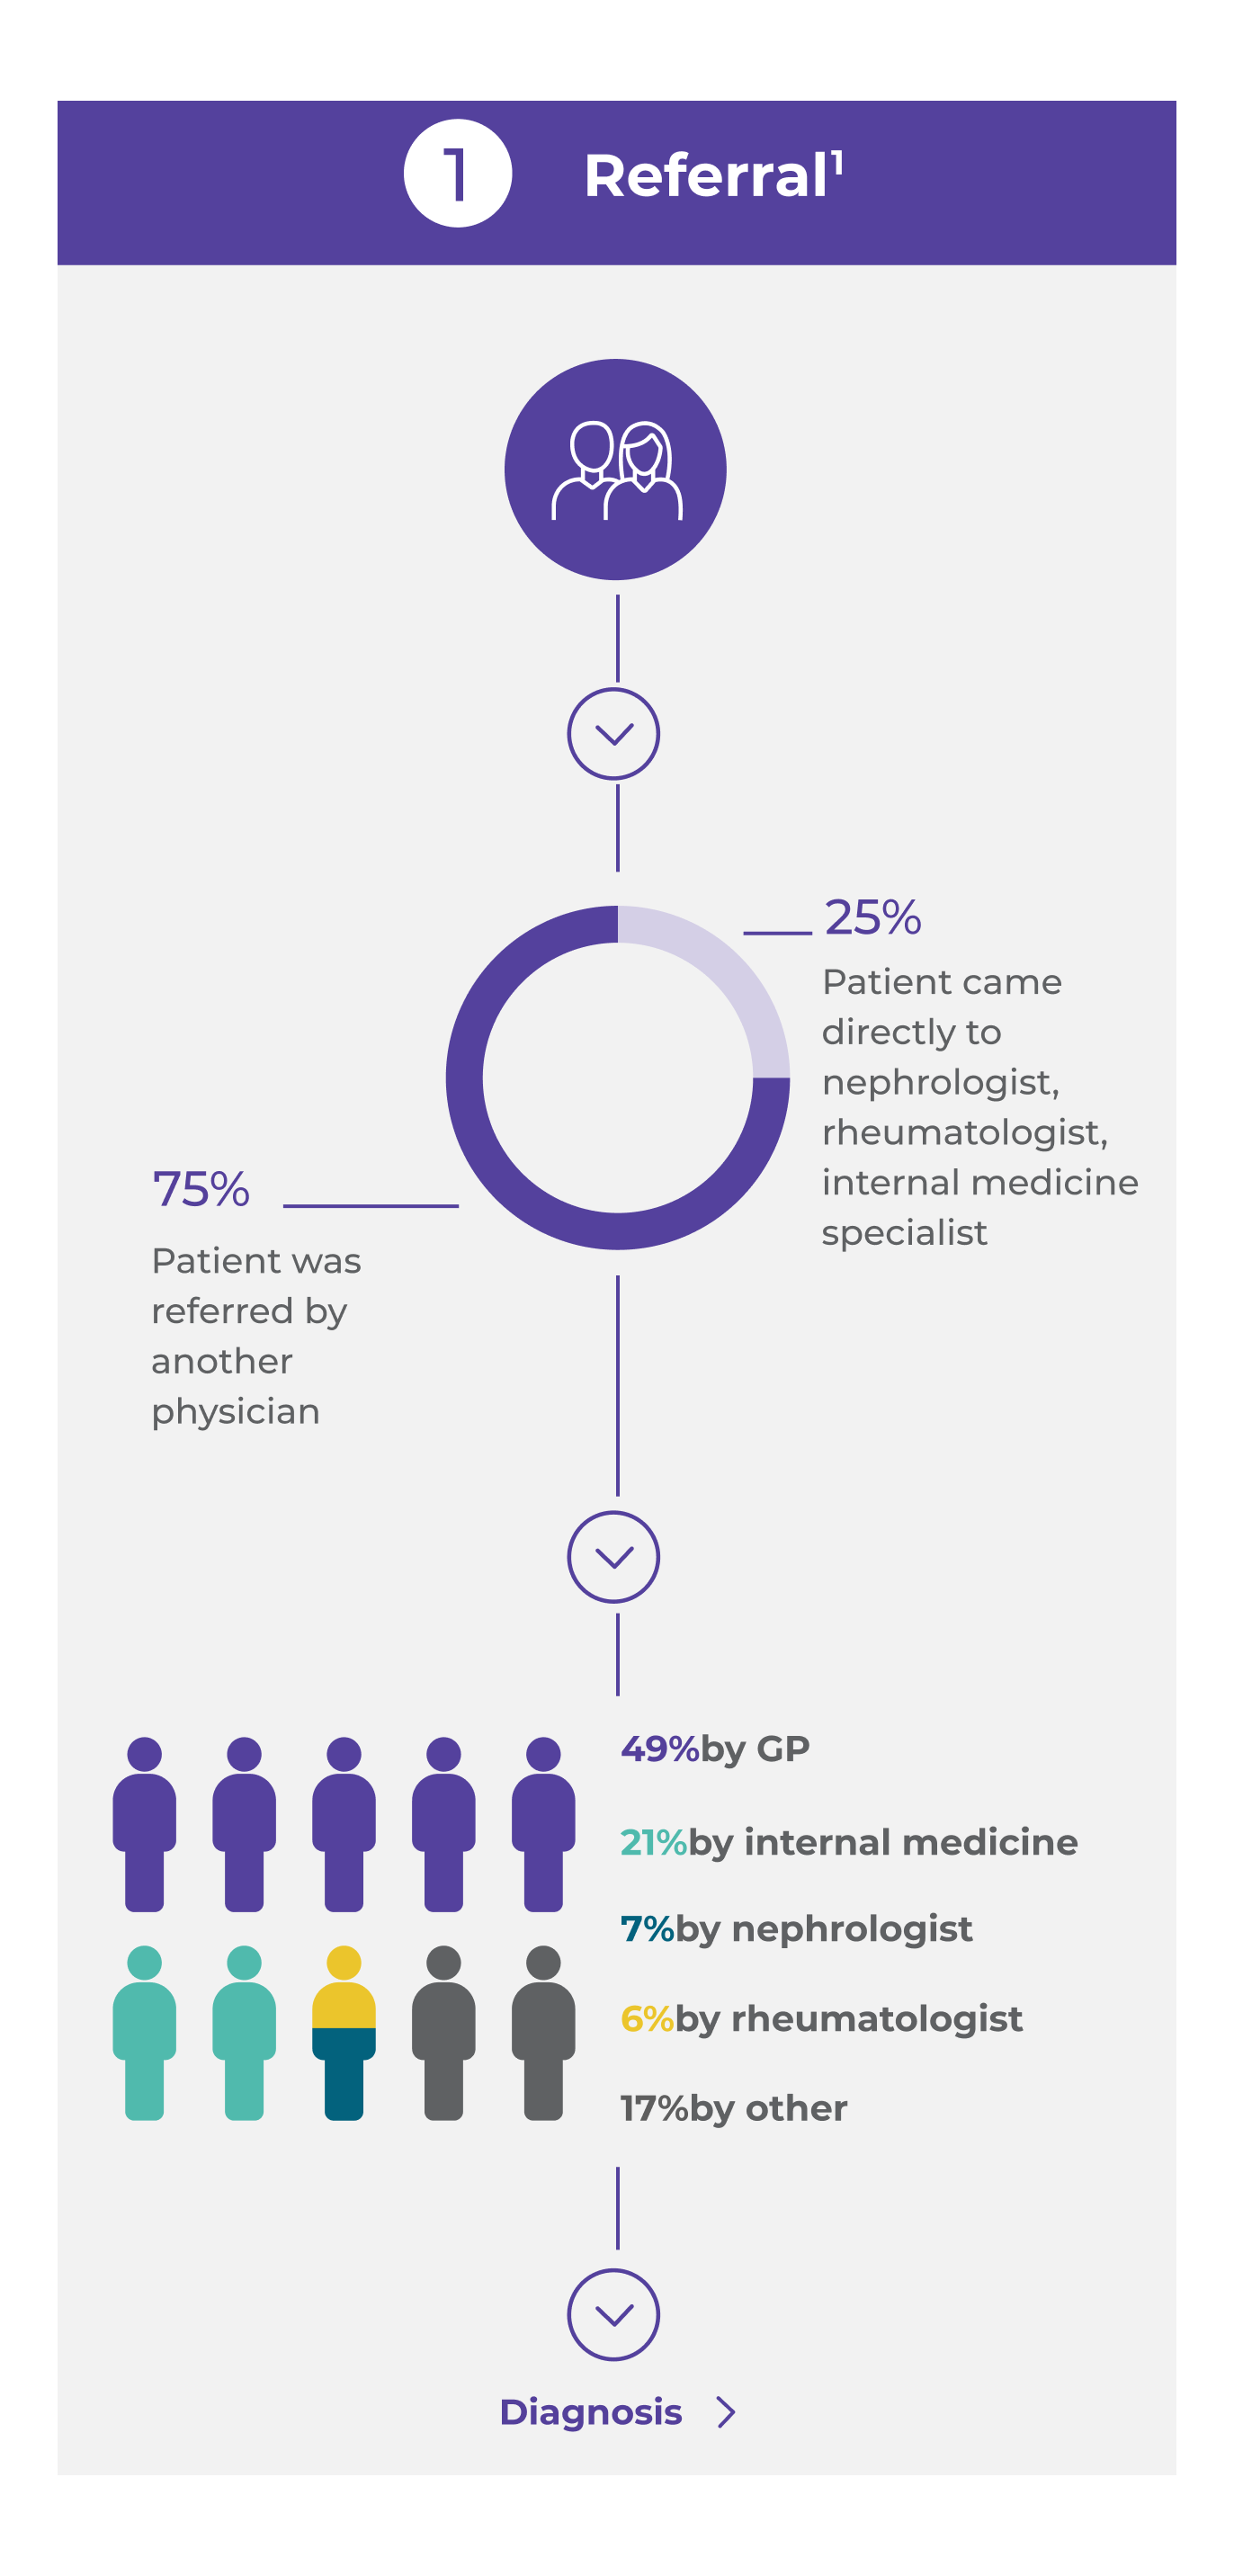
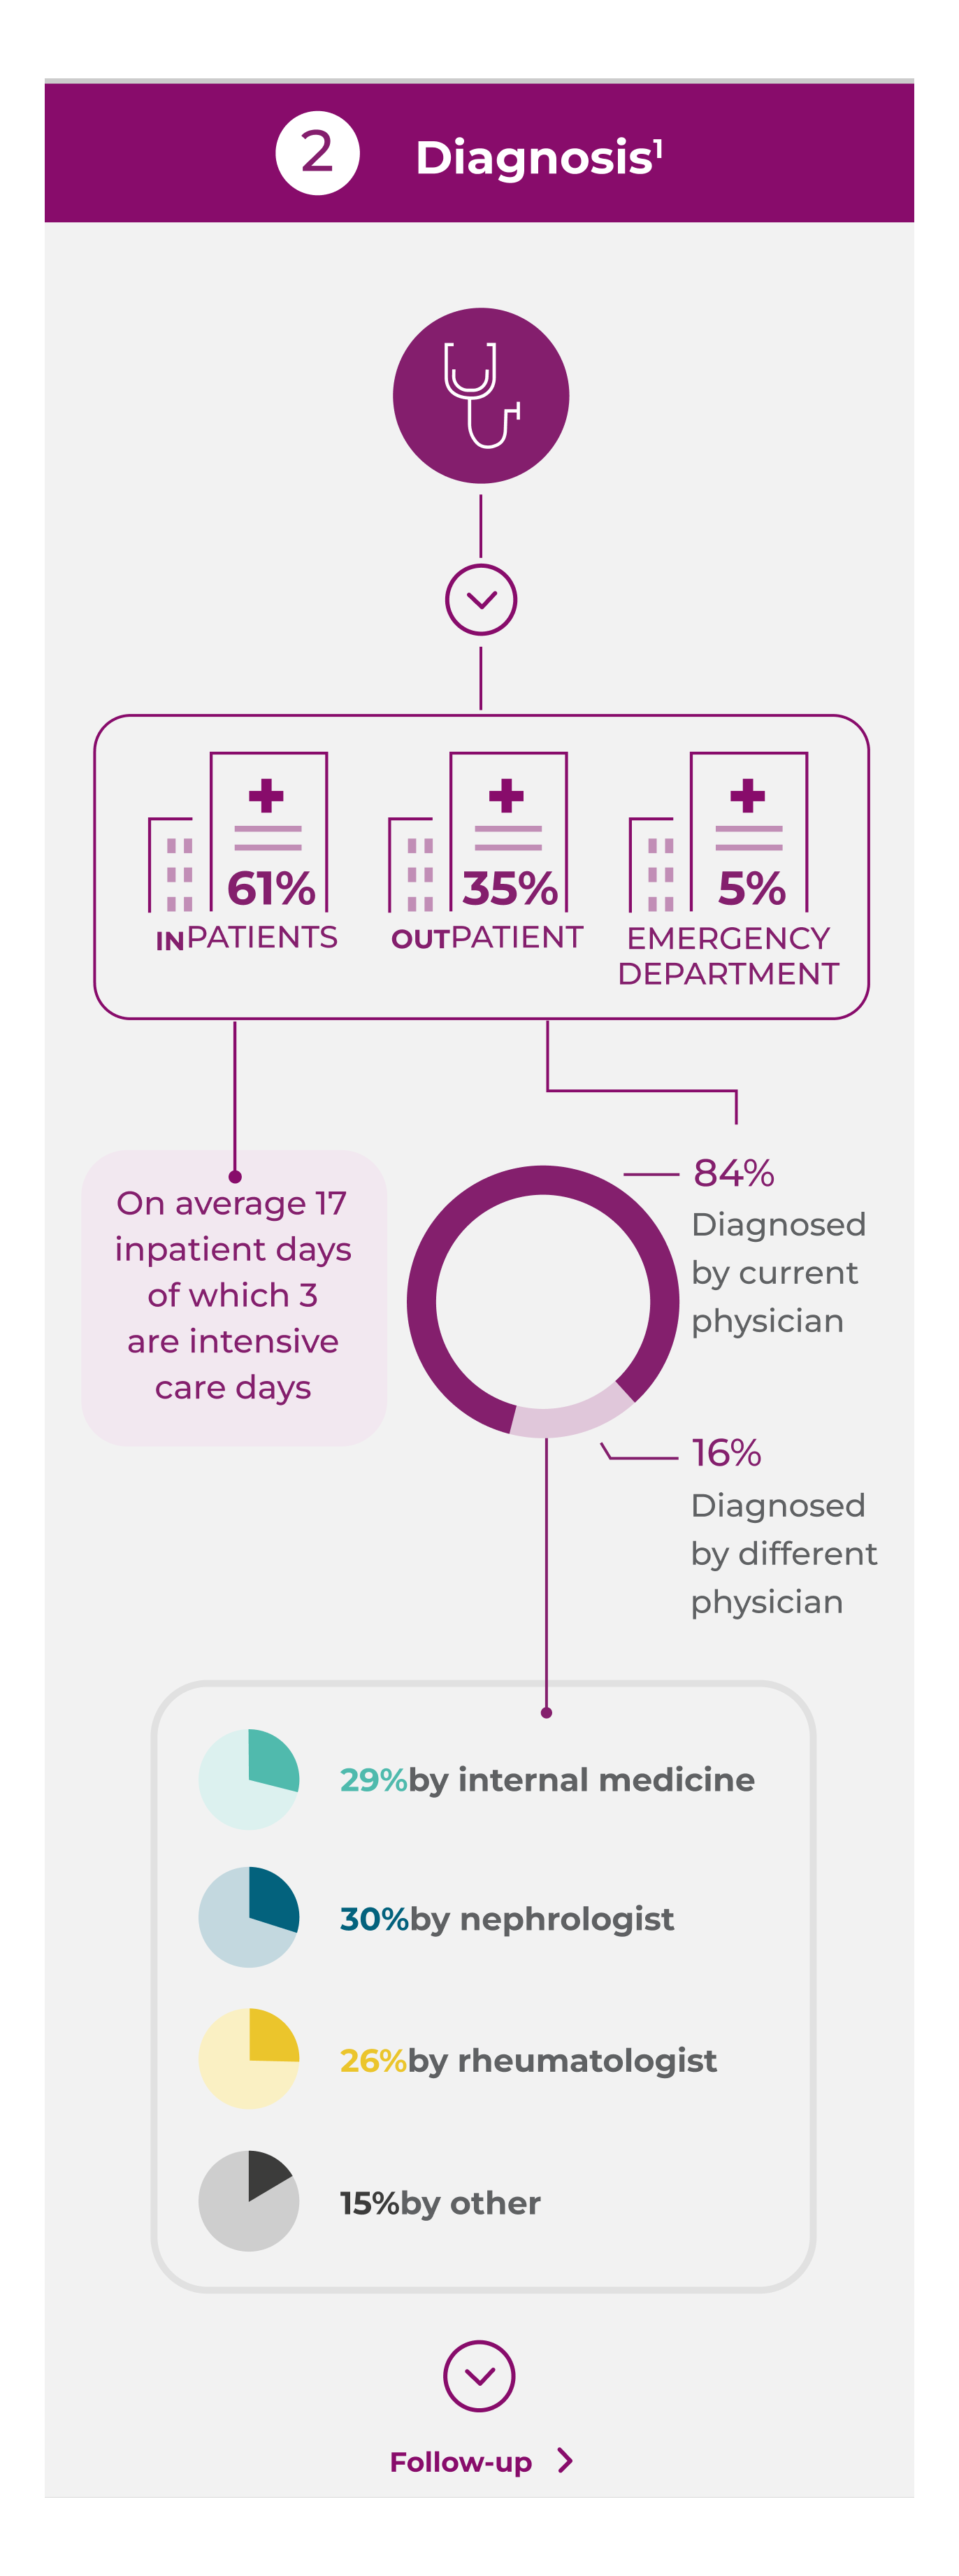
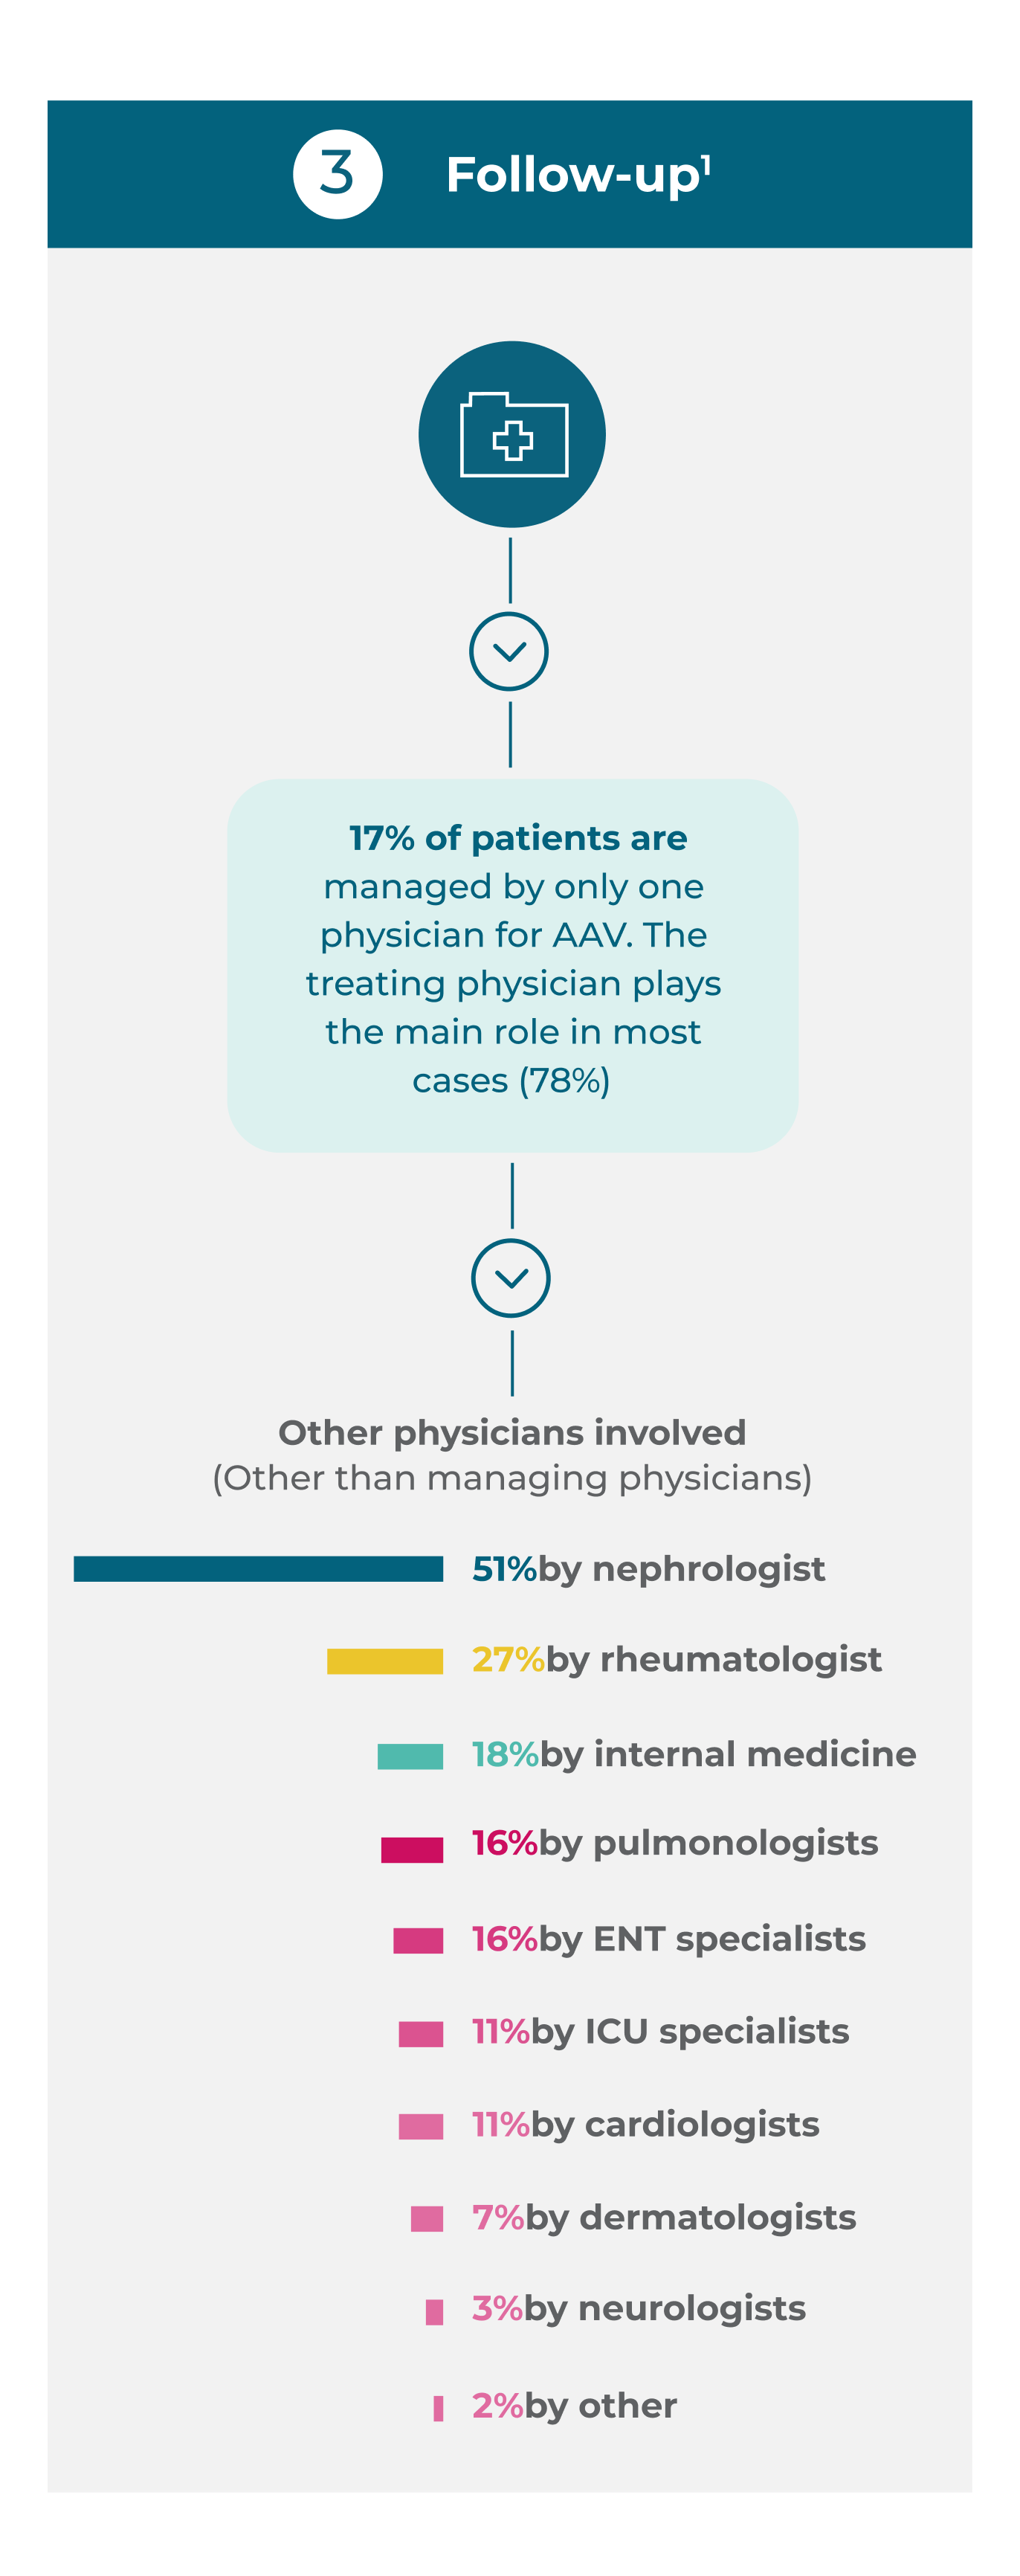
AAV patients often experience a complex pathway of patient referral and diagnosis1*
EULAR recommendations state that patients should have access to education focusing on the impact of AAV and its prognosis, key warning symptoms and treatment (including treatment-related complications). AAV requires multidisciplinary management by centres with, or with ready access to, specific vasculitis expertise.2
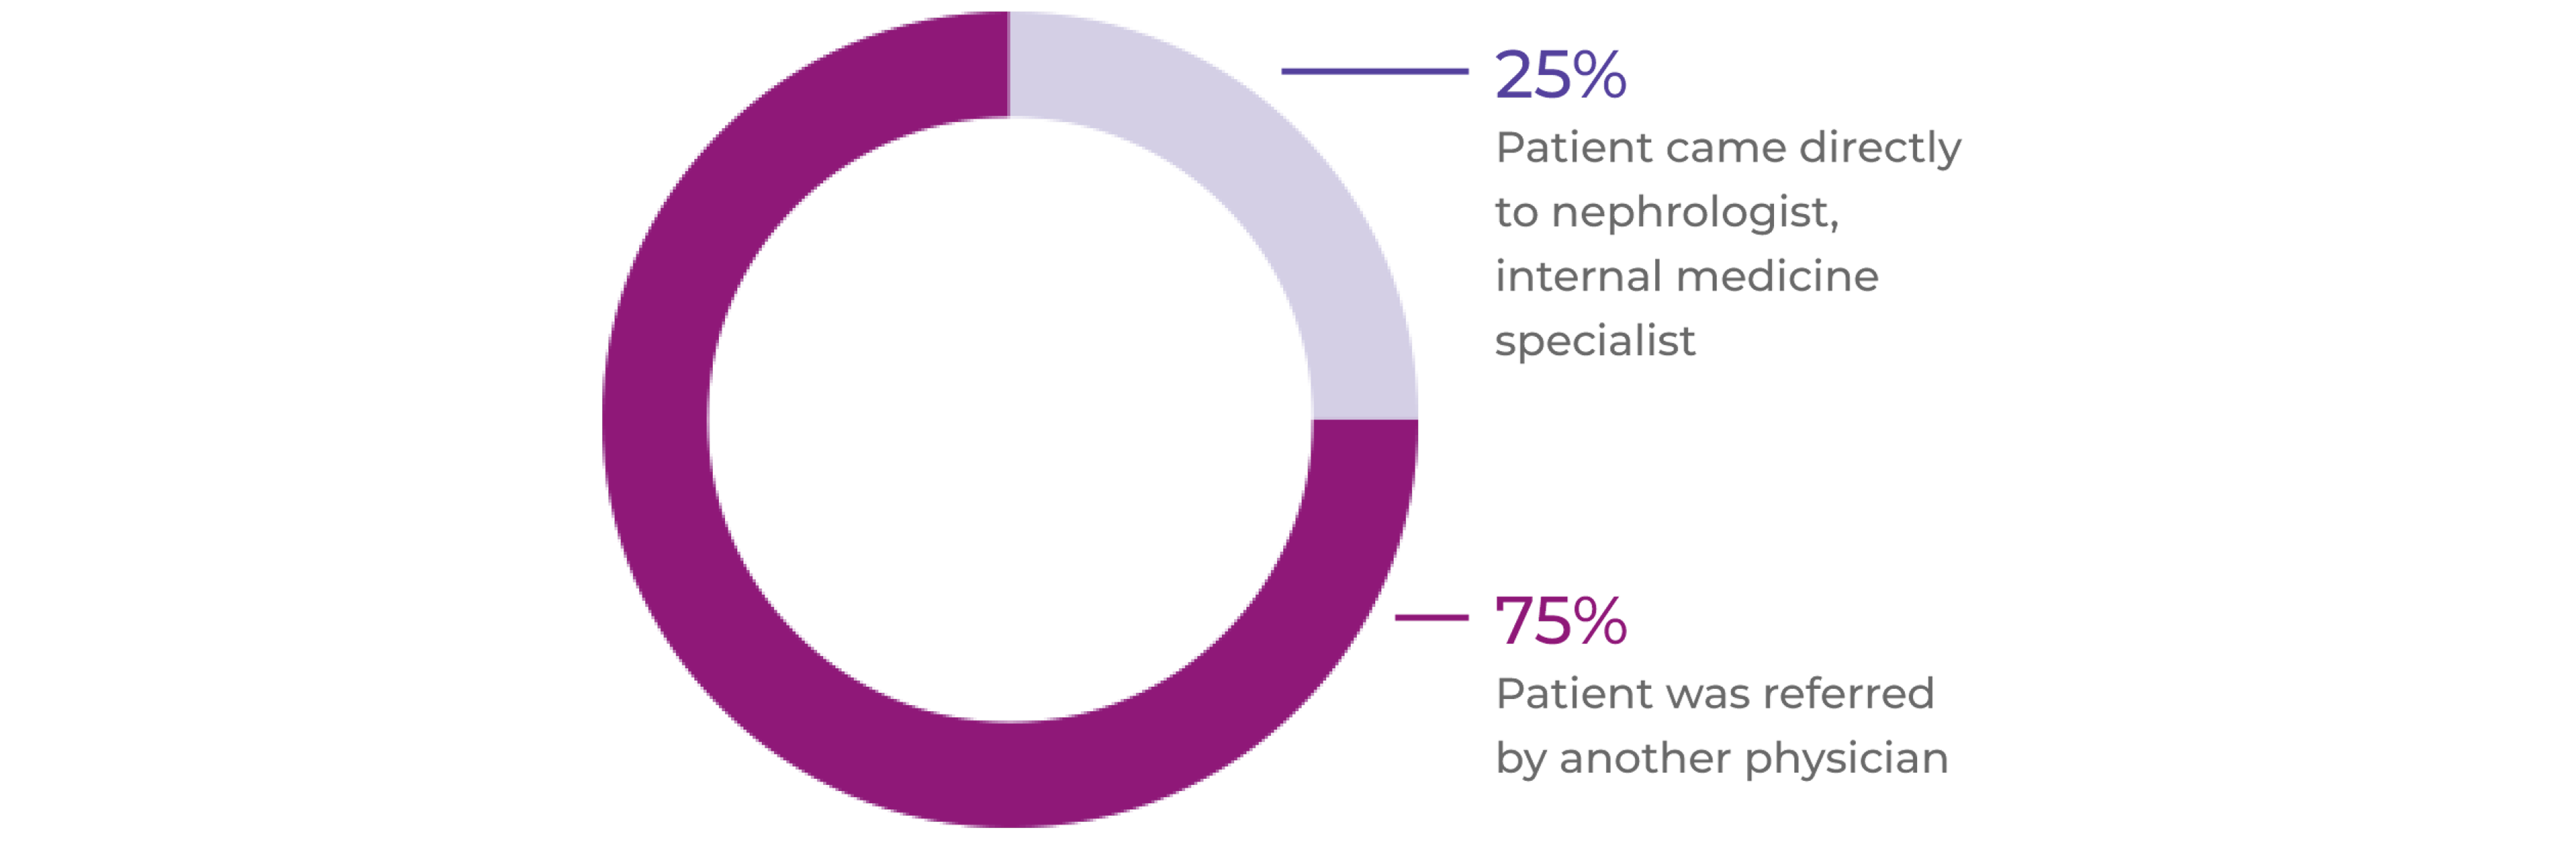
Most patients are referred by other physicians1
Many patients have renal disease at presentation, but general non-specific referral symptoms predominate1
Renal disease: 64%
Fatigue: 58%
Fever: 54%
Weight loss: 53%
Joint pain: 47%
16% of patients have had their referral symptoms for over 3 months before receiving an AAV diagnosis1
Comorbidities at diagnosis are common (65% of patients)1
Hypertension: 45%
Type 2 diabetes: 16%
COPD/asthma: 15%
Coronary arterial disease: 10%
Arthritis: 9%
Osteoporosis: 7%
BMI > 35: 6%
Cardiac failure: 6%
The relative rarity and non-specific presentation of AAV can lead to a delay in disease diagnosis of more than 6 months in one-third of patients.3
Diagnosis of AAV and differentiation into the GPA, MPA or EGPA subtype depends on the patient’s clinical symptom constellation, the results of imaging studies and laboratory investigation.3,4
Due to the linkage of anti-PR3 with GPA and anti-MPO with MPA, ANCA testing is critical for diagnosis.3–7
- Up to 20% of GPA and MPA patients and over 60% of EGPA patients are ANCA negative4
- A positive ANCA test result can be found in other conditions, e.g. autoimmune hepatitis, ulcerative colitis, infection with hepatitis C virus or HIV, or infectious endocarditis, without associated vasculitis4
An organ biopsy, usually renal, is often performed to confirm the diagnosis.3,4

References & footnotes
Footnotes
*Retrospective study reviewing 929 incident AAV patients (GPA: 54%; MPA: 46%; mean age: 57 years; male: 53.7%) in France, Germany, Italy and the United Kingdom (399 physicians) who initiated remission induction therapy between November 2014 and February 2017 with data collected at baseline presentation, and after 1, 3, 6 and 12 months of treatment.1
Abbreviations
AAV, ANCA-associated vasculitis; ANCA, anti-neutrophil cytoplasmic antibody; BMI, body mass index; COPD, chronic obstructive pulmonary disease; EGPA, eosinophilic granulomatosis with polyangiitis; ENT, ear, nose and throat; EULAR, European Alliance of Associations for Rheumatology; GP, general practitioner; GPA, granulomatosis with polyangiitis; HIV, human immunodeficiency virus; ICU, intensive care unit; MPA, microscopic polyangiitis; MPO, myeloperoxidase; PR3, proteinase 3
References
- Rutherford PA, et al. J Am Soc Nephrol 2018;29:839(Abstract SA-PO403).
- Hellmich B, et al. Ann Rheum Dis 2023;0:1–18.
- Yates M, Watts R. Clin Med (Lond) 2017;17(1):60–4.
- Pagnoux C. Eur J Rheumatol 2016;3(3):122–33.
- Al-Hussain T, et al. Adv Anat Pathol 2017;24(4):226–34.
- Chen M, et al. Medicine (Baltimore) 2008;87(4):203–9.
- Lionaki S, et al. Arthritis Rheum 2012;64(10):3452–62.
Additional resources


























GCC-AVA-2500012 | Date of preparation: October 2025
AAV treatment
Treatment pathway
A framework of practice for the treatment and management of AAV patients
AAV is a chronic condition with a relapsing course that needs long-term immunosuppressive therapy1–4
EULAR recommendations state that AAV patients should be offered best care which must be based on shared decision-making between the patient and the physician, considering efficacy, safety and costs5
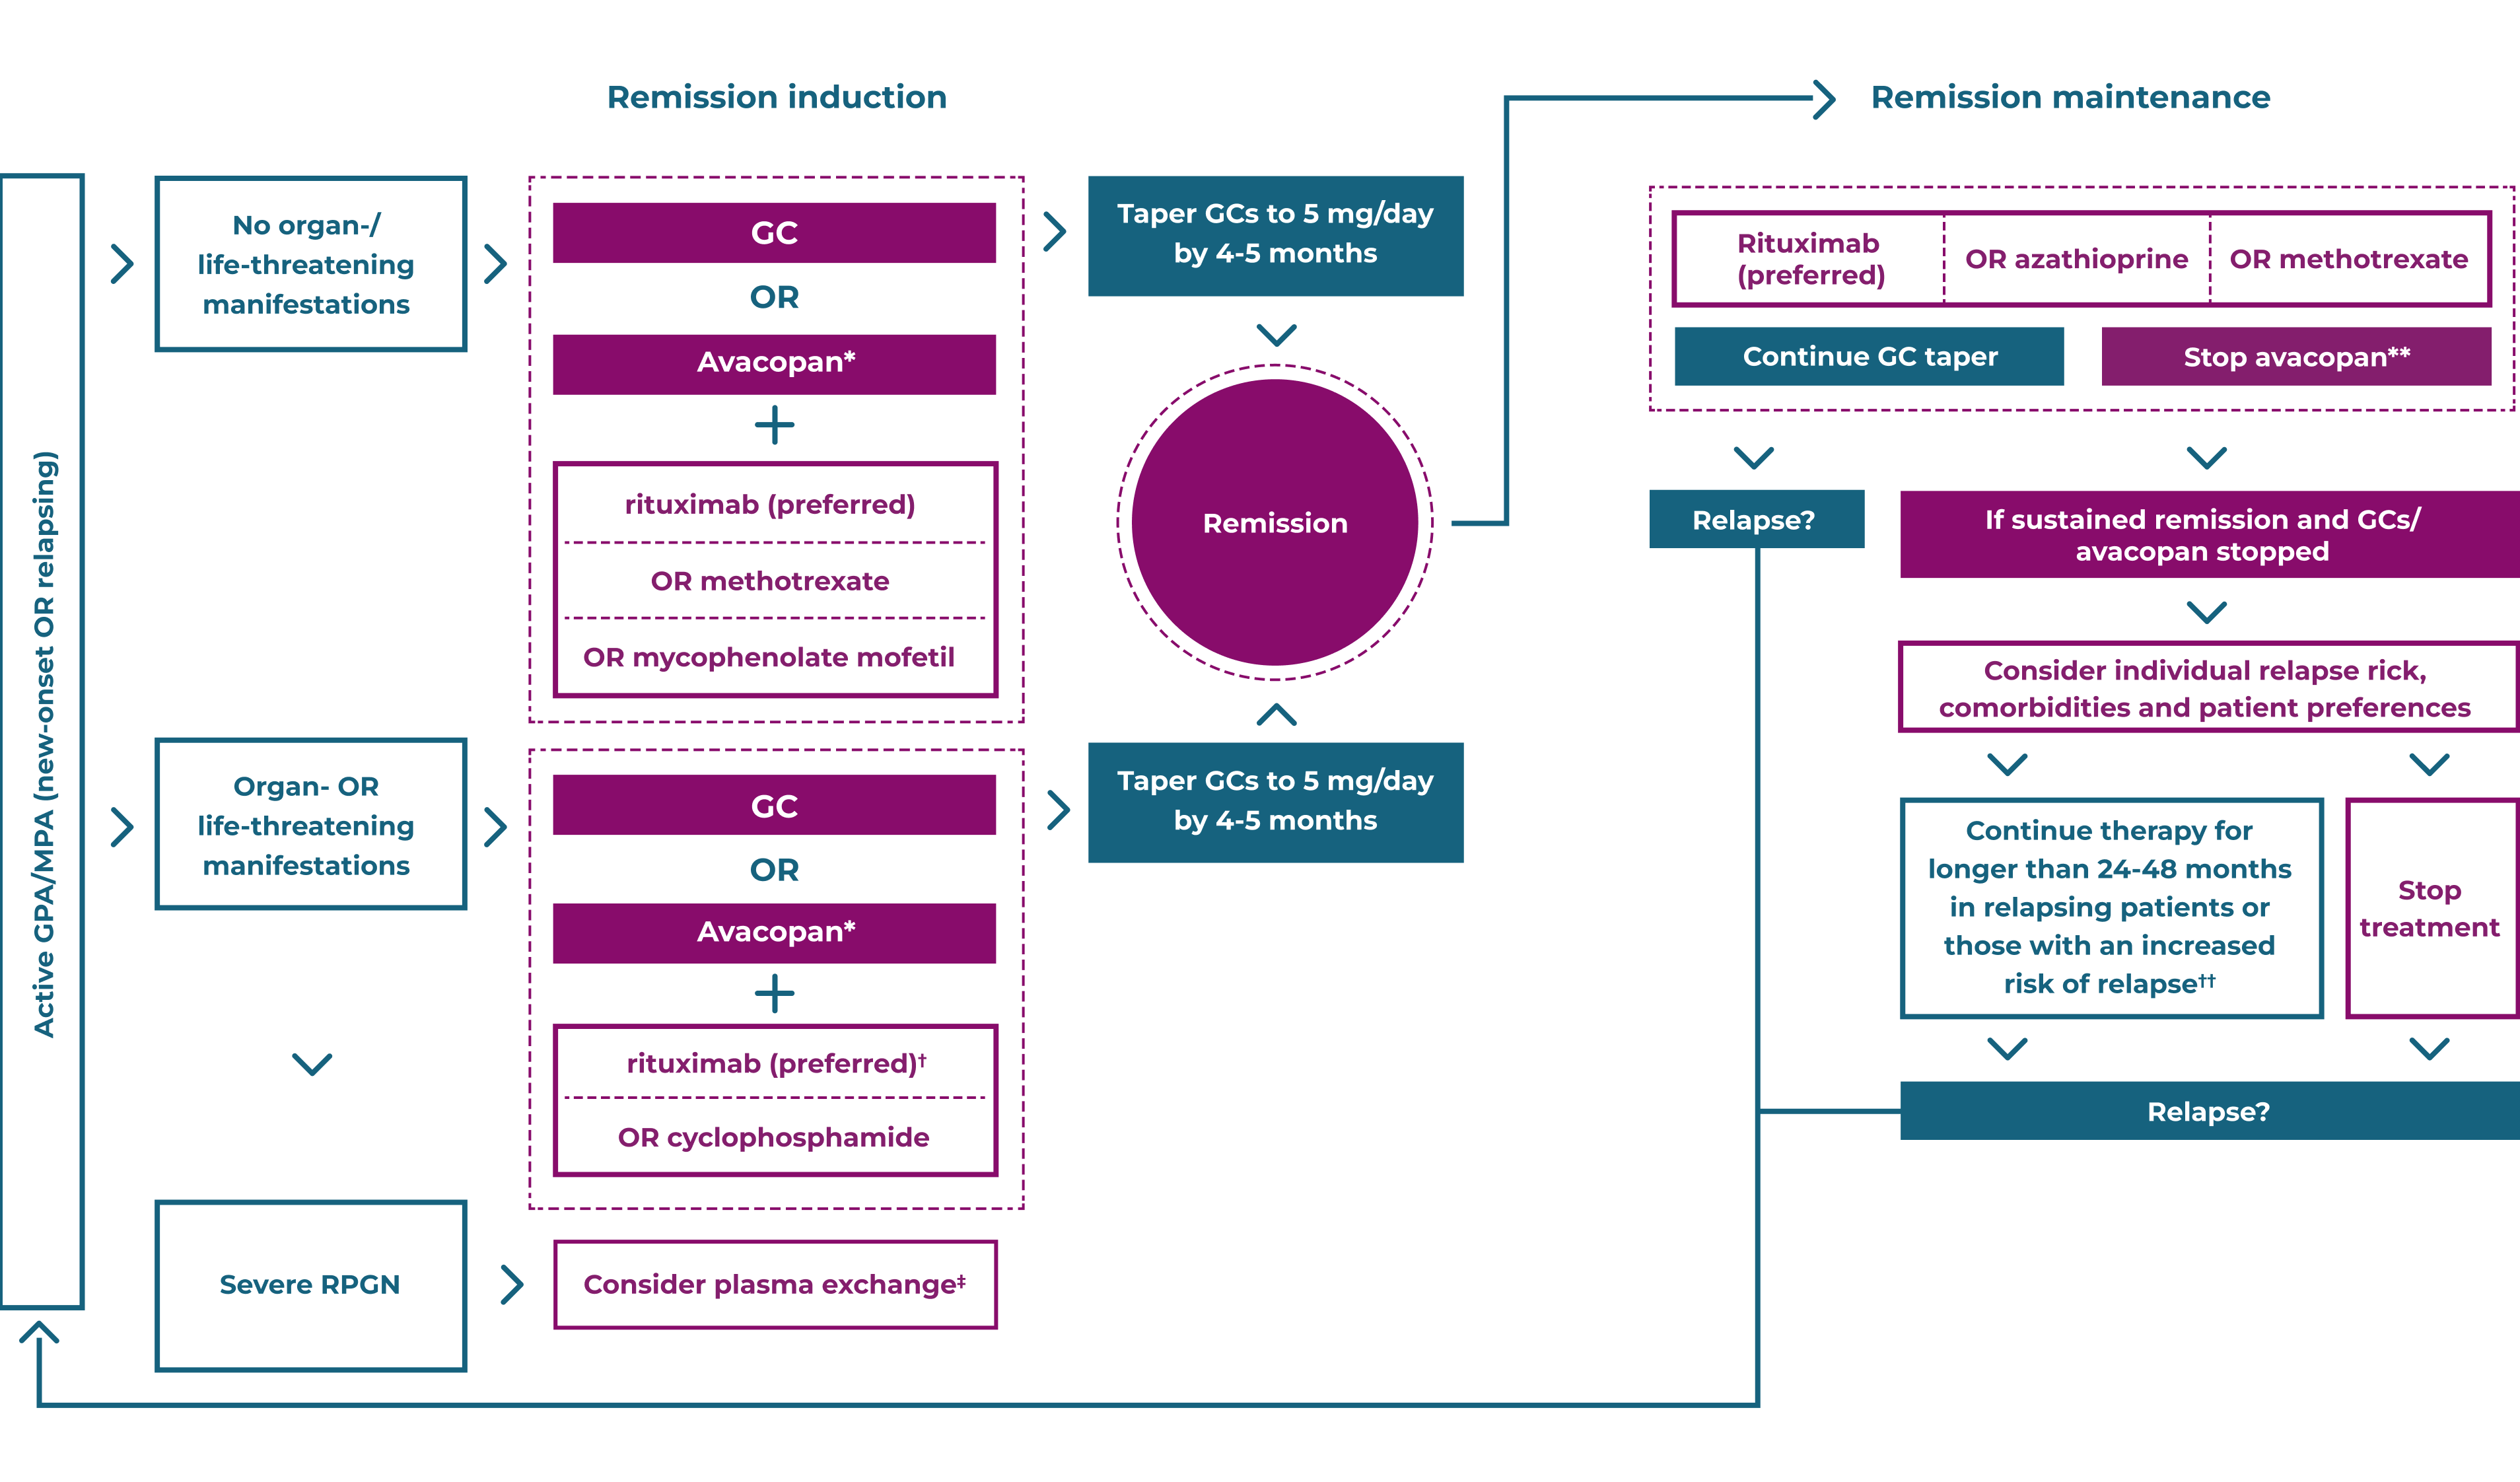
Diagram adapted from Hellmich B, et al. Ann Rheum Dis 2023. Always refer to the product SmPC for approved indications before prescribing.
References & footnotes
Footnotes
*As part of a strategy to substantially reduce exposure to GCs.
†Rituximab preferred in relapsing disease.
‡In patients with serum creatinine >300 μmol/L due to active glomerulonephritis.
§If remission not achieved, consult an expert centre; if remission achieved, proceed to maintenance phase.
**Stop avacopan after duration of treatment of 6–12 months (there are no data on use of avacopan beyond 1 year, so longer-term use cannot be recommended); in ADVOCATE, remission sustained until Week 52 (the second primary endpoint) was reached at a higher rate in the avacopan (65.7%) than GC (54.9%) treatment groups, suggesting that avacopan may have efficacy for maintenance of remission.
††Longer duration of treatment should be balanced against patient preferences and risks of continuing immunosuppression.
Abbreviations
EULAR, European Alliance of Associations for Rheumatology; GC, glucocorticoid; RPGN, rapidly progressive glomerulonephritis.
References
- Yates M, Watts R. ANCA-associated vasculitis. Clin Med (Lond) 2017;17(1):60–4.
- Ntatsaki E, et al. Rheumatology (Oxford) 2014;53(12):2306–9.
- Yates M, et al. EULAR/ERA-EDTA recommendations for the management of ANCA-associated vasculitis. Ann Rheum Dis 2016;75(9):1583–94.
- Rutherford PA, et al. Real world experience in ANCA-associated vasculitis (AAV) – a complex pathway of patient referral, diagnosis and management. J Am Soc Nephrol 2018;29:839(Abstract SA-PO403).
- Hellmich B, et al. EULAR recommendations for the management of ANCA-associated vasculitis: 2022 update. Ann Rheum Dis 2023;0:1–18.
AAV treatment
Treatment pathway
A framework of practice for the treatment and management of AAV patients
AAV is a chronic condition with a relapsing course that needs long-term immunosuppressive therapy1–4
EULAR recommendations state that AAV patients should be offered best care which must be based on shared decision-making between the patient and the physician, considering efficacy, safety and costs5
Diagram adapted from Hellmich B, et al. Ann Rheum Dis 2023. Always refer to the product SmPC for approved indications before prescribing.
References & footnotes
Footnotes
*As part of a strategy to substantially reduce exposure to GCs.
†Rituximab preferred in relapsing disease.
‡In patients with serum creatinine >300 μmol/L due to active glomerulonephritis.
§If remission not achieved, consult an expert centre; if remission achieved, proceed to maintenance phase.
**Stop avacopan after duration of treatment of 6–12 months (there are no data on use of avacopan beyond 1 year, so longer-term use cannot be recommended); in ADVOCATE, remission sustained until Week 52 (the second primary endpoint) was reached at a higher rate in the avacopan (65.7%) than GC (54.9%) treatment groups, suggesting that avacopan may have efficacy for maintenance of remission.
††Longer duration of treatment should be balanced against patient preferences and risks of continuing immunosuppression.
Abbreviations
EULAR, European Alliance of Associations for Rheumatology; GC, glucocorticoid; RPGN, rapidly progressive glomerulonephritis.
References
- Yates M, Watts R. ANCA-associated vasculitis. Clin Med (Lond) 2017;17(1):60–4.
- Ntatsaki E, et al. Rheumatology (Oxford) 2014;53(12):2306–9.
- Yates M, et al. EULAR/ERA-EDTA recommendations for the management of ANCA-associated vasculitis. Ann Rheum Dis 2016;75(9):1583–94.
- Rutherford PA, et al. Real world experience in ANCA-associated vasculitis (AAV) – a complex pathway of patient referral, diagnosis and management. J Am Soc Nephrol 2018;29:839(Abstract SA-PO403).
- Hellmich B, et al. EULAR recommendations for the management of ANCA-associated vasculitis: 2022 update. Ann Rheum Dis 2023;0:1–18.
AAV treatment
The balance of treatment
Treatment must balance controlling vasculitis with minimising treatment-related damage1–4
At the time of AAV diagnosis or relapse, the major concerns around treatment involve controlling vasculitis activity and minimising the acute adverse effects from therapy.1,2 Later when remission is achieved, cumulative organ damage, often related to long-term low dose glucocorticoids, and patient experience are more important.1–4
The EULAR Guidelines now state that patients should be periodically screened for treatment-related adverse effects and co-morbidities. They recommend prophylaxis and life-style advice to reduce treatment-related complications and other co-morbidities.5
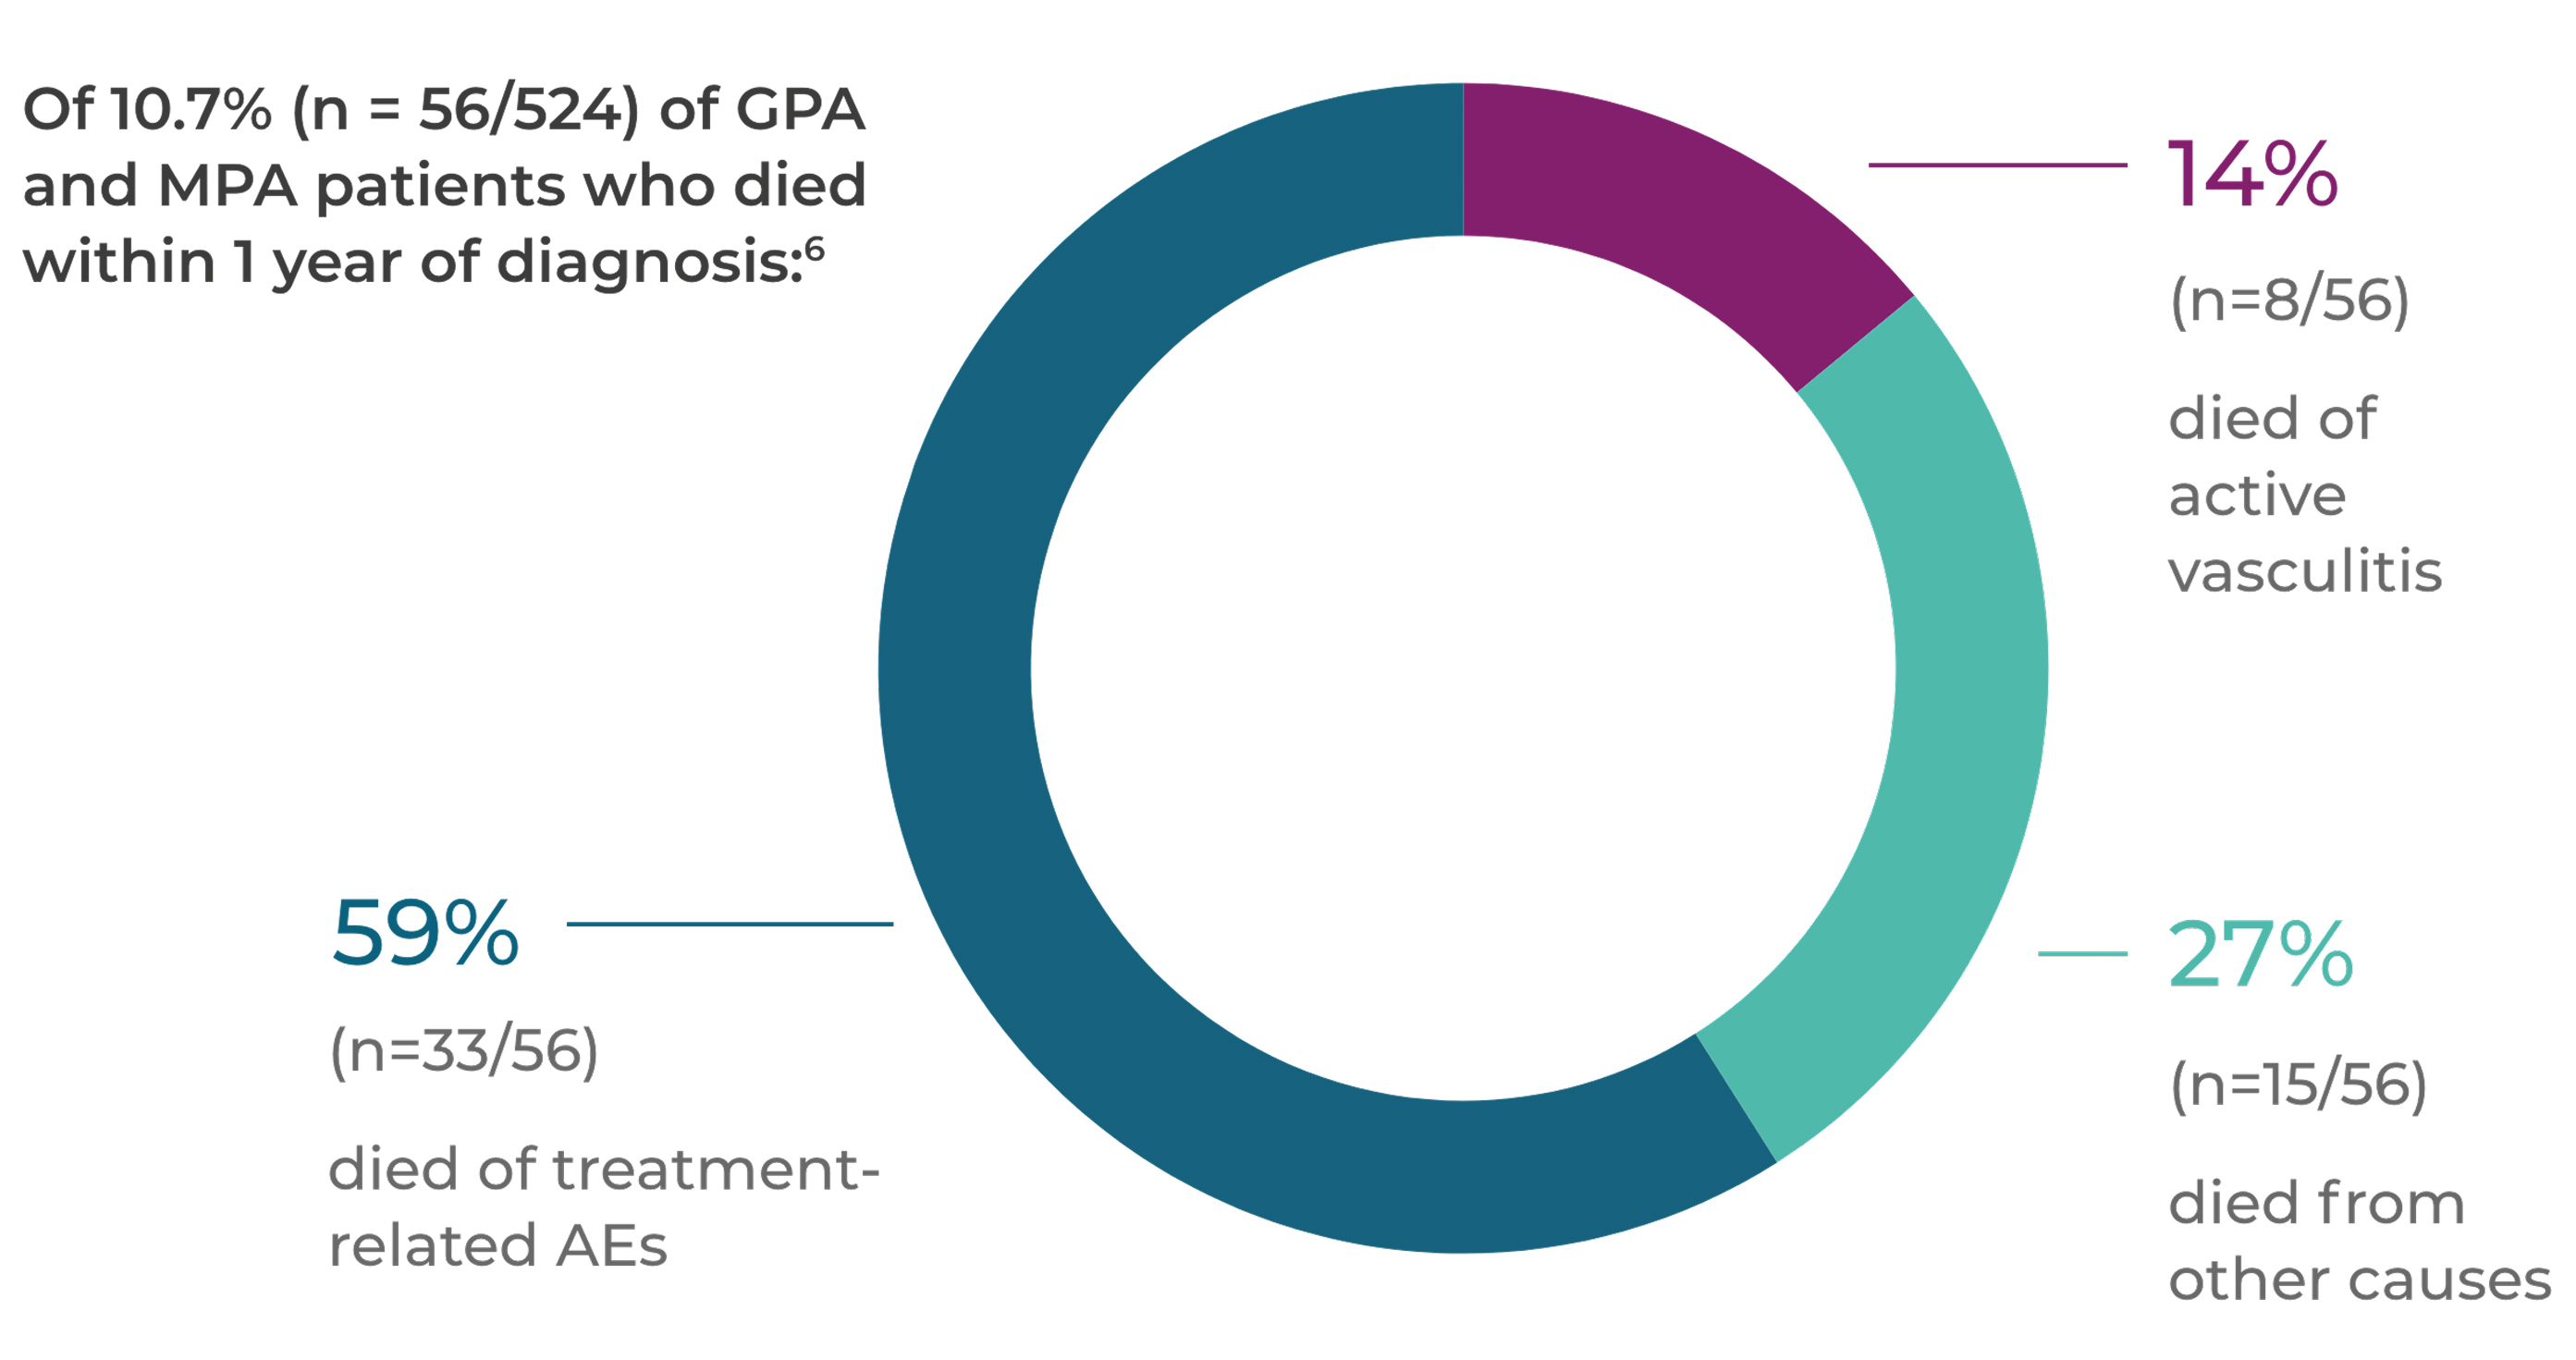
Treatment-related AEs are the leading cause of acute mortality6
In the first year after a GPA or MPA diagnosis, 56 of 524 patients died. A total of 59% (n=33/56) of these deaths were as a result of treatment-related AEs.6*
A systematic literature review of glucocorticoid-related AEs in AAV clinical studies published between 1 January 2007 and 30 January 2018 identified mortality (33%) as the glucocorticoid-related serious AE with the highest frequency observed during early induction treatment. Other common glucocorticoid-related serious AEs experienced by patients include infections (20%), musculoskeletal (17%) and renal disorders (15%).7†
References & footnotes
Footnotes
*Patients (n=524) with newly diagnosed GPA or MPA (adapted Chapel Hill disease definitions) recruited into four EUVAS RCTs in 42 hospitals in 11 European countries and Mexico between 1995 and 2005, and followed for 1 year.6
†Systematic literature review of 33 studies published between 1 January 2007 and 30 January 2018 containing data on glucocorticoid-related AEs (any untoward medical occurrence) and serious AEs (defined in European Medicines Agency CPMMP/ICH/377/95) which threaten life or function.7
Abbreviations
AAV, ANCA-associated vasculitis; AE, adverse event; ANCA, anti-neutrophil cytoplasmic antibody; EULAR, European Alliance of Associations for Rheumatology; EUVAS, European Vasculitis Study Group; GPA, granulomatosis with polyangiitis; MPA, microscopic polyangiitis; RCT, randomised controlled trial.
References
- Yates M, et al. EULAR/ERA-EDTA recommendations for the management of ANCA-associated vasculitis. Ann Rheum Dis 2016;75(9):1583–94.
- Robson JC, et al. Patient perceptions of glucocorticoids in anti-neutrophil cytoplasmic antibody-associated vasculitis. Rheumatol Int 2018;38(4):675–82.
- Yates M, Watts R. ANCA-associated vasculitis. Clin Med (Lond) 2017;17(1):60–4.
- Robson J, et al. Glucocorticoid treatment and damage in the anti-neutrophil cytoplasm antibody-associated vasculitides: long-term data from the European Vasculitis Study Group trials. Rheumatology (Oxford) 2015;54(3):471–81.
- Hellmich B, et al. EULAR recommendations for the management of ANCA-associated vasculitis: 2022 update. Ann Rheum Dis 2023;0:1–18.
- Little MA, et al. Early mortality in systemic vasculitis: relative contribution of adverse events and active vasculitis. Ann Rheum Dis 2010;69(6):1036−43.
- Rutherford PA, et al. Adverse events due to glucocorticoids in ANCA-associated vasculitis are frequent but reporting should improve. J Am Soc Nephrol 2018;29:840(2. Abstract SA-PO405).
GCC-AVA-2500012 | Date of preparation: October 2025
AAV treatment
Latest clinical data in AAV

2021
Avacopan-based regimen is superior at sustaining remission at Week 52 compared to a GC-based regimen1
- At Week 26, avacopan-based regimen demonstrated non-inferiority in achieving clinical remission vs a GC-based regimen (p<0.001)
- At Week 52, avacopan-based regimen demonstrated superiority at sustaining clinical remission vs a GC-based regimen (p=0.007)
- Incidences of serious adverse events were similar in avacopan-based regimen and GC-based regimen groups (37.3% vs 39%, respectively)


2020
Reducing the GC dose in severe AAV patients did not significantly impact the primary outcome of death or ESRD, but did reduce the rate of infection (HR=0.69)2
- Risk of death or ESRD with reduced GC dose was non-inferior to standard GC dose
- Reduced-dose regimen decreased the risk of serious infections (0.69; 95% CI, 0.52 to 0.93) without increasing the risk of other adverse events
- The continued use of a standard-dose GC regimen, even in patients with severe AAV should be re-evaluated
- Use of PLEX in this patient population provided no added benefit
2020
Extended maintenance therapy leads to better clinical outcomes3
- Relapse rates were reduced in patients receiving long-term RTX
treatment compared to standard maintenance therapy - With standard maintenance therapy, relapse rates remain high. At month 28, 25% of patients experienced a relapse.
- There was no difference in the incidence of AEs with long-term treatment
2019
Preliminary results show that a reduced GC dose can be effective for reinducing remission in AAV, and RTX was superior to AZA at maintaining remission4,5
- Remission induction with a reduced GC dose should be considered clinically, as it was as effective as a typical GC dose regimen
- Initial findings show RTX to be superior to AZA in reducing relapses
- Relapses still occurred in both treatment groups. By 24 months, 13% of the RTX patients and 38% of the AZA patients experienced a relapse.
2018
Tailored and fixed-schedule RTX regimens are equally as effective at maintaining remission, but relapses still occur6
- Relapse rates were similar with tailored and fixed-schedule RTX treatment
- The tailored regimen demonstrated that remission maintenance can be achieved with fewer RTX infusions
- Further research is required to establish reliable laboratory tests that can predict the appearance of relapse
2014
RTX is more effective than AZA for maintenance of remission, but GC use and relapse remain common7-10
- RTX was shown to be a more effective maintenance therapy than AZA for newly diagnosed AAV patients
- Minor and major relapses occurred throughout the maintenance phase of treatment. By Month 28, 17% of patients suffered a major relapse, increasing to 38% by Month 60.
- GC use remained common amongst all patients throughout the 60-month follow-up period
2010
RTX was found to be non-inferior to daily CYC for the induction and maintenance of remission, but remission rates remain variable11–13
- Patient achievement and maintenance of full remission remains variable with current therapies
- 1 in 3 patients fail to achieve remission at 6 months without use of GCs, and 1 in 2 fail to sustain remission at 12 months
- Non-severe relapse is an under-recognised clinical problem; these patients suffer subsequent relapses resulting in high GC exposure
References & footnotes
Abbreviations
AAV, ANCA-associated vasculitis; AE, adverse event; ANCA, anti-neutrophil cytoplasmic antibody; AZA, azathioprine; CYC, cyclophosphamide; ESRD, end-stage renal disease; GC, glucocorticoid; HR, hazard ratio; PLEX, plasma exchange; RTX, rituximab
References
- Jayne D, et al. Avacopan for the Treatment of ANCA-Associated Vasculitis. N Engl J Med 2021;384(7):599–609.
- Walsh M, et al. Plasma Exchange and Glucocorticoids in Severe ANCA-Associated Vasculitis. N Engl J Med 2020:382(7):622–31.
- Charles P, et al. Long-Term Rituximab Use to Maintain Remission of Antineutrophil Cytoplasmic Antibody-Associated Vasculitis: A Randomized Trial. Ann Intern Med 2020;173(30):179–87.
- Smith RM, et al. Rituximab as therapy to induce remission after relapse in ANCA-associated vasculitis. Ann Rheum Dis 2020;79(9):1243–96
- Smith RM, et al. A Randomized Controlled Trial of Rituximab (RTX) vs. Azathioprine (AZA) After Induction of Remission with RTX for Patients with ANCA-Associated Vasculitis (AAV) and Relapsing Disease. J Am Soc Nephrol 2019:30.
- Charles P, et al. Comparison of individually tailored versus fixed-schedule rituximab regimen to maintain ANCA-associated vasculitis remission: results of a multicentre, randomised controlled, phase III trial (MAINRITSAN2). Ann Rheum Dis 2020;173(30):1143–9.
- Guillevin L, et al. Rituximab versus azathioprine for maintenance in ANCA-associated vasculitis. N Engl J Med 2014;371(19):1771–80.
- Terrier B, et al. Long-term efficacy of remission-maintenance regimens for ANCA-associated vasculitides. Ann Rheum Dis 2018;77(8):1150–6.
- Terrier B, et al. Long-term efficacy of remission-maintenance regimens for ANCA-associated vasculitides. Ann Rheum Dis 2018;77(8): 1150–6. [Supplementary appendix].
- Guillevin L, et al. Rituximab versus azathioprine for maintenance in ANCA-associated vasculitis. N Engl J Med 2014;371(19):1771–80. [Supplementary appendix].
- Stone JH, et al. Rituximab versus Cyclophosphamide for ANCA-Associated Vasculitis. N Engl J Med 2010;363(3):221–32.
- Specks U, et al. Efficacy of remission-induction regimens for ANCA-associated vasculitis. N Engl J Med 2013;369(5):417–27.
- Miloslavsky EM, et al. Outcomes of nonsevere relapses in antineutrophil cytoplasmic antibody-associated vasculitis treated with glucocorticoids. Arthritis Rheum 2015;67(6):1629–36.
GCC-AVA-2500012 | Date of preparation: October 2025
AAV treatment
Real-world experience
Many patients do not achieve or sustain full remission1*
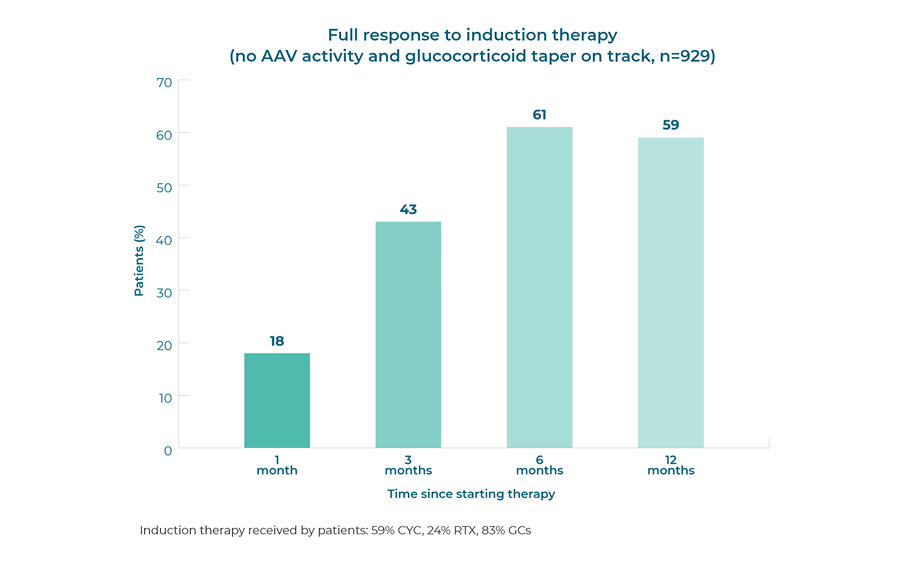
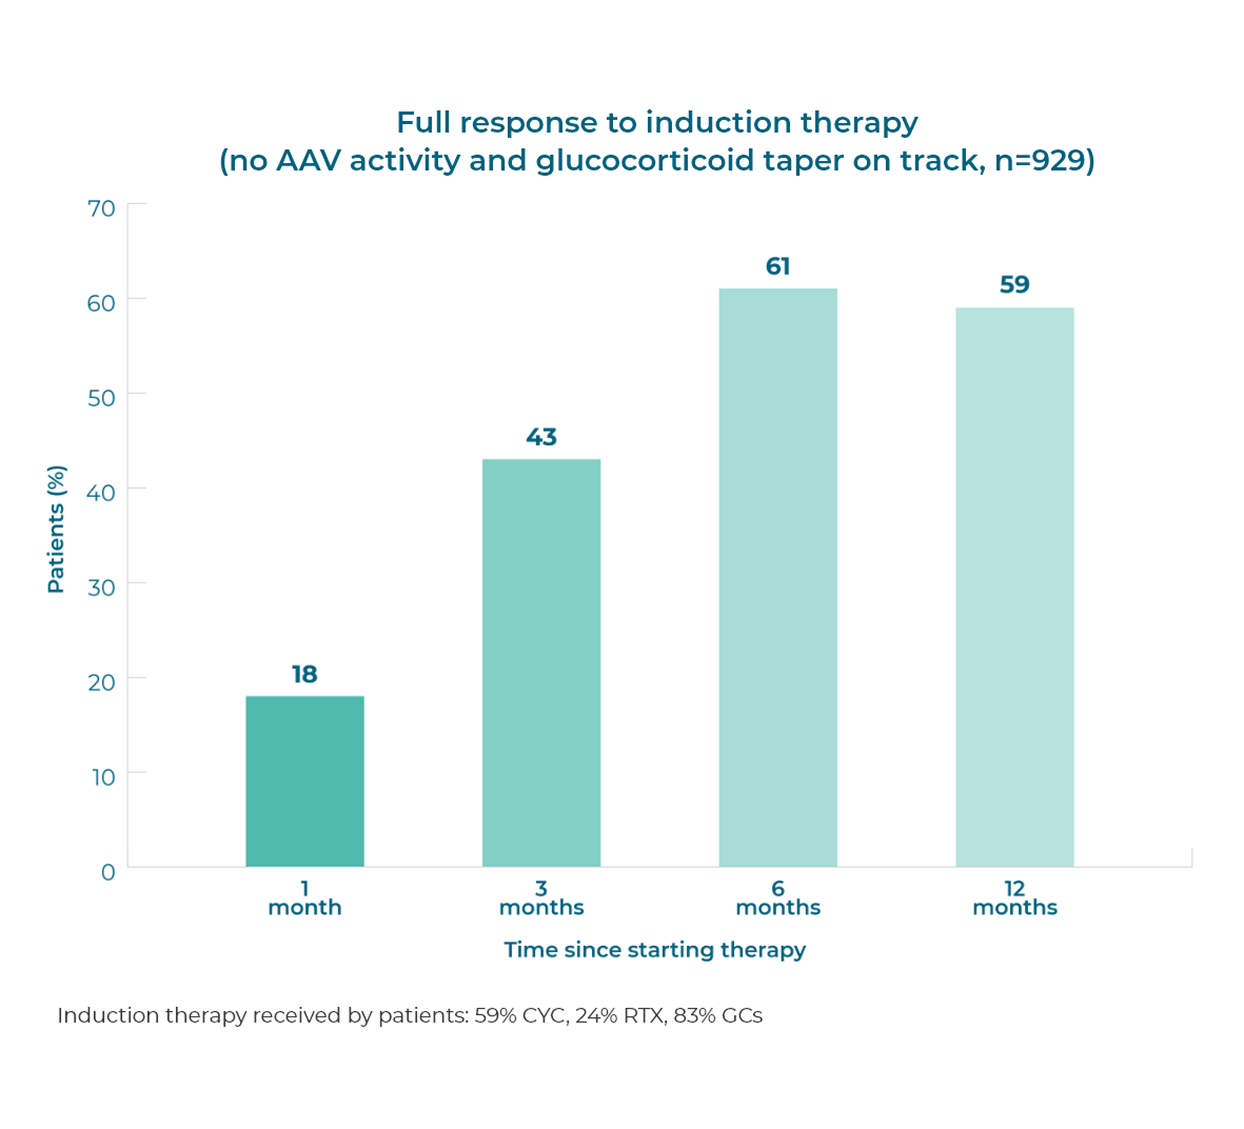
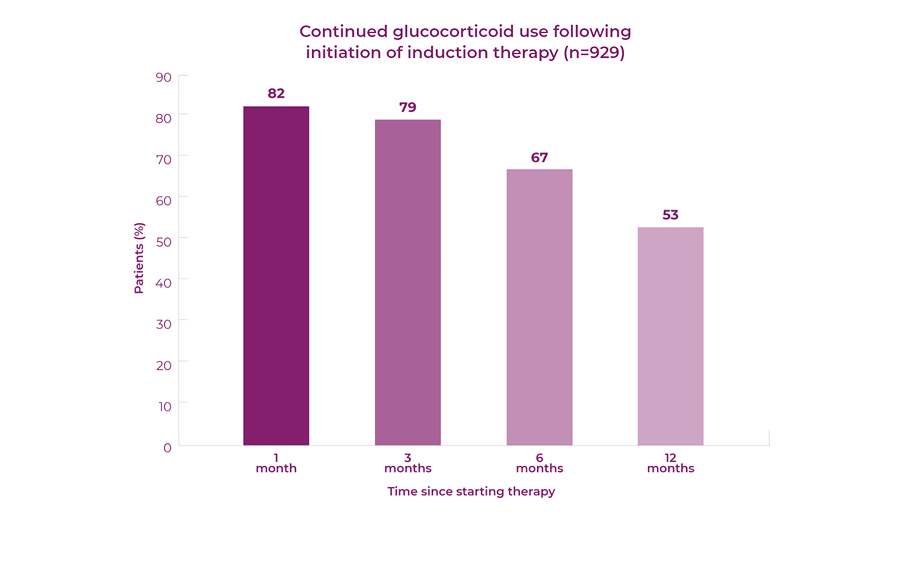
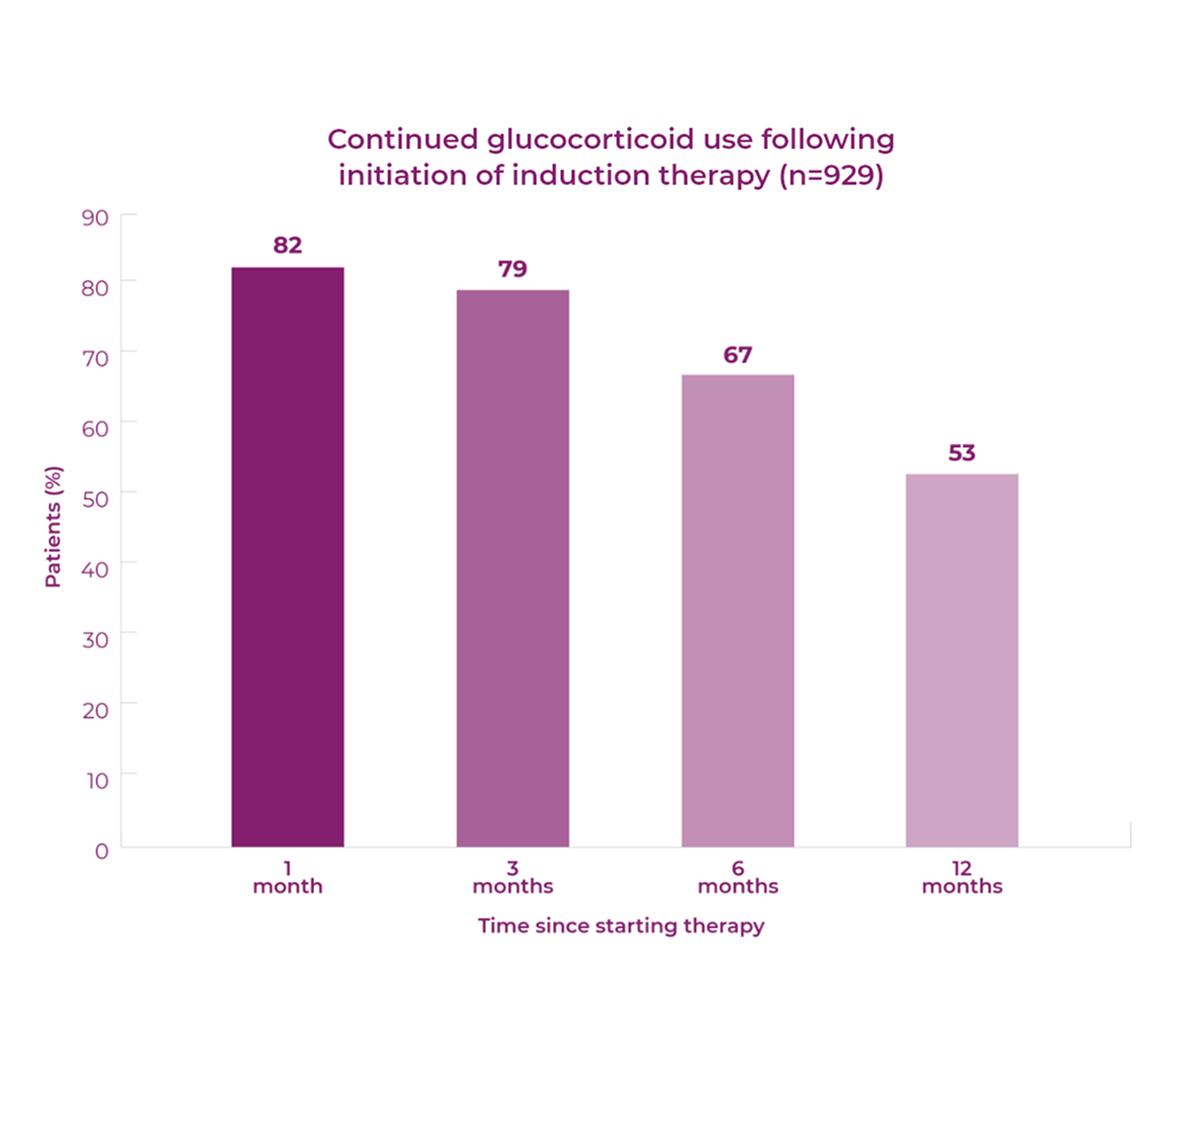
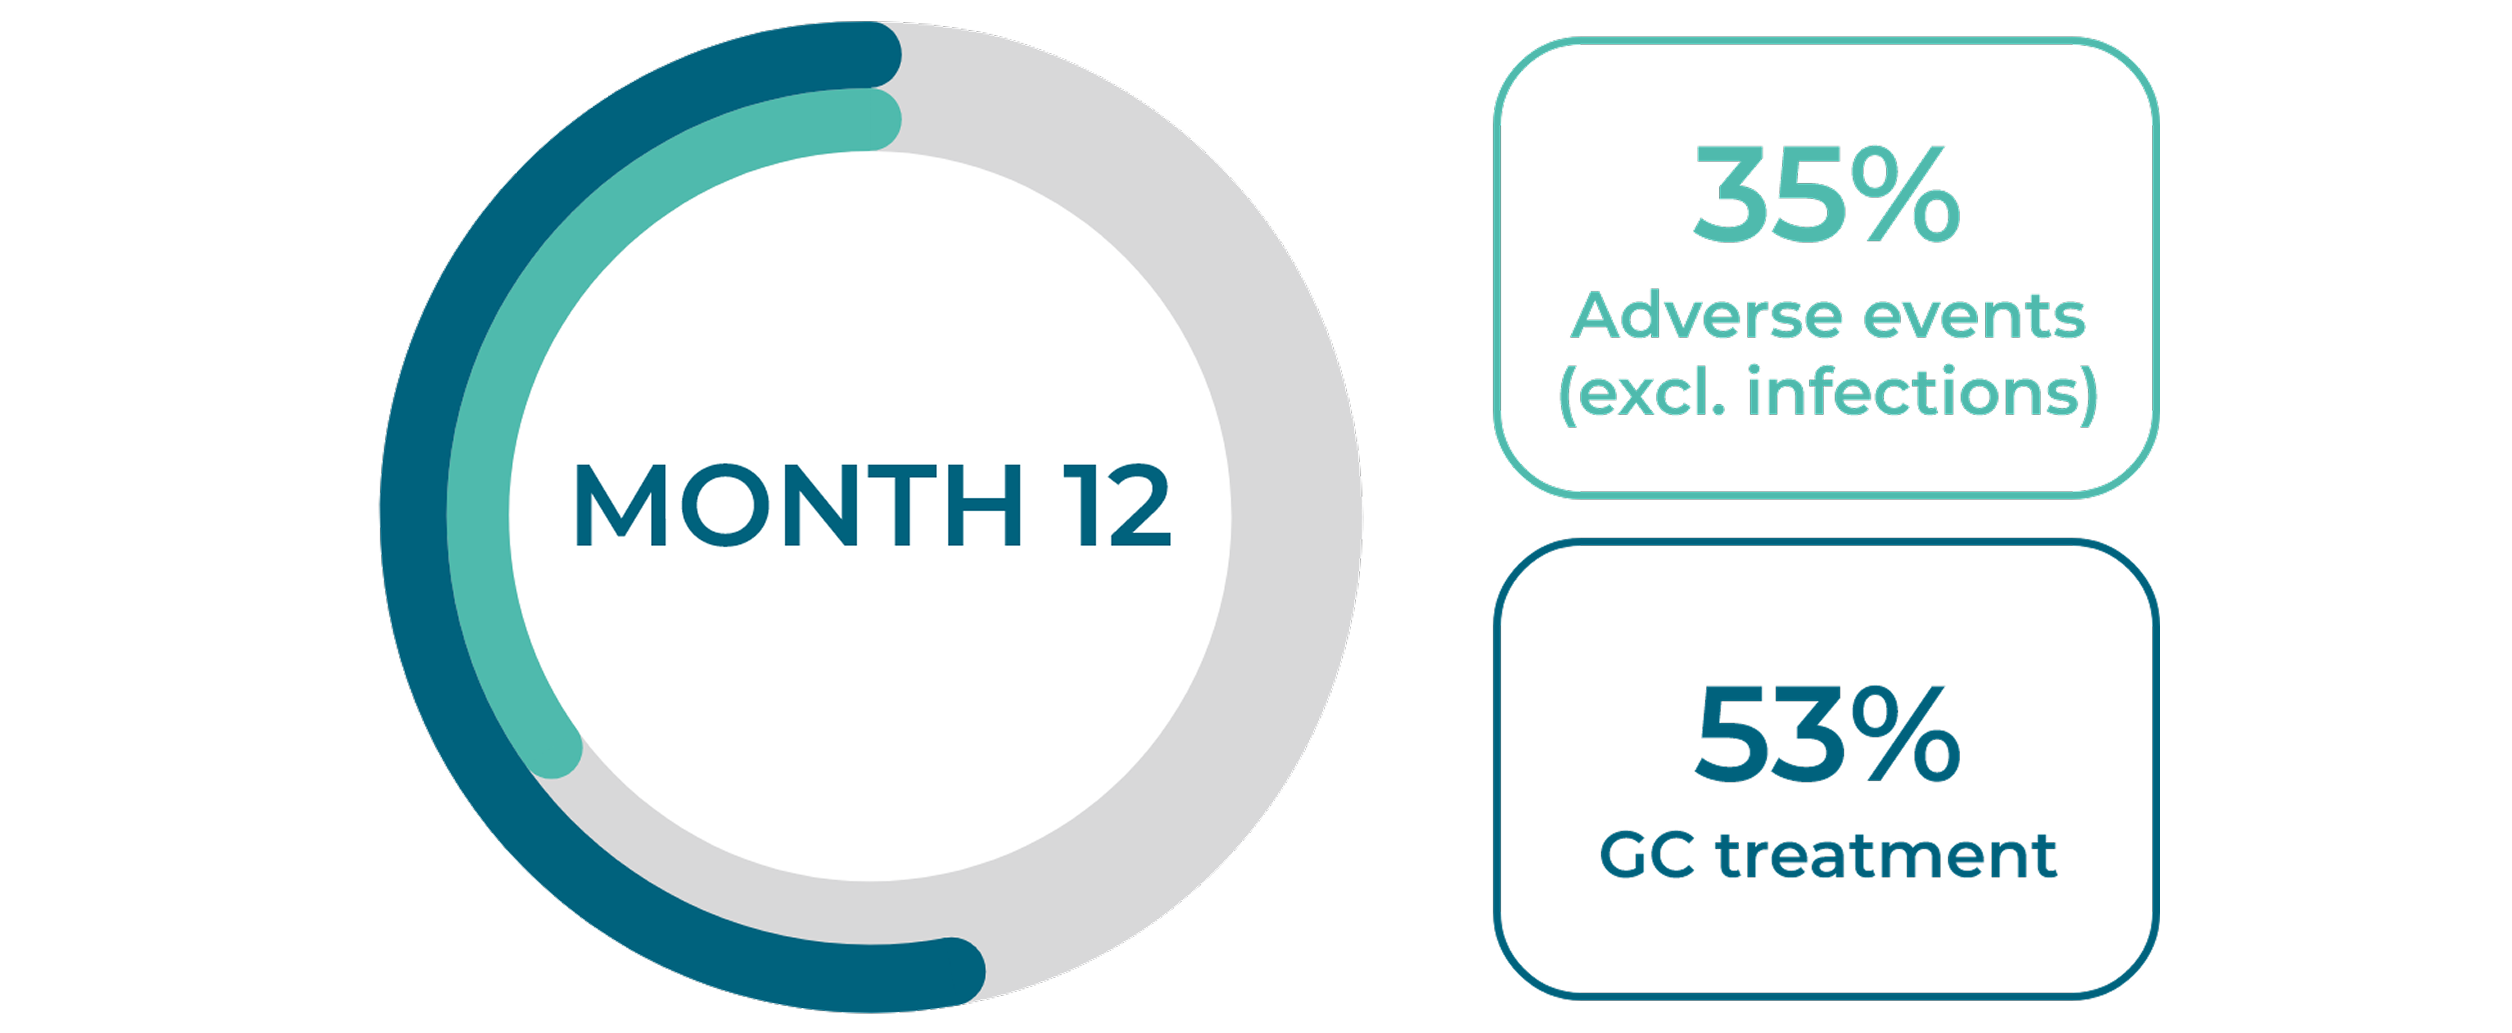
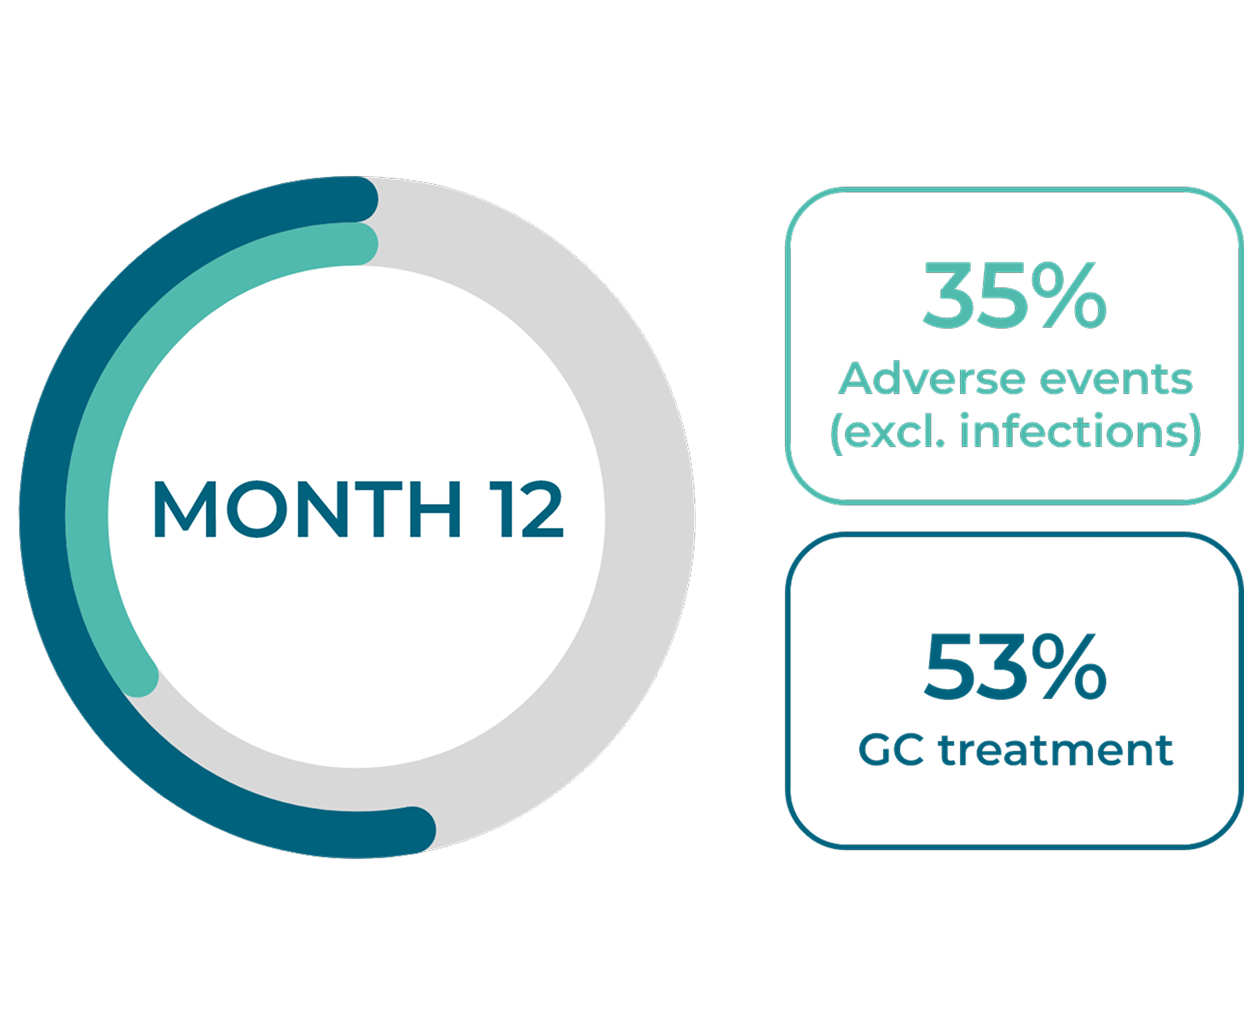
Patient response to remission induction therapy is variable. After 12 months of therapy (n=929), 59% of GPA (granulomatosis with polyangiitis, previously called Wegener’s) and MPA (microscopic polyangiitis) patients achieve full remission, and >50% of patients continue glucocorticoid use.1 More patients need to achieve and sustain remission without prolonged glucocorticoid use.
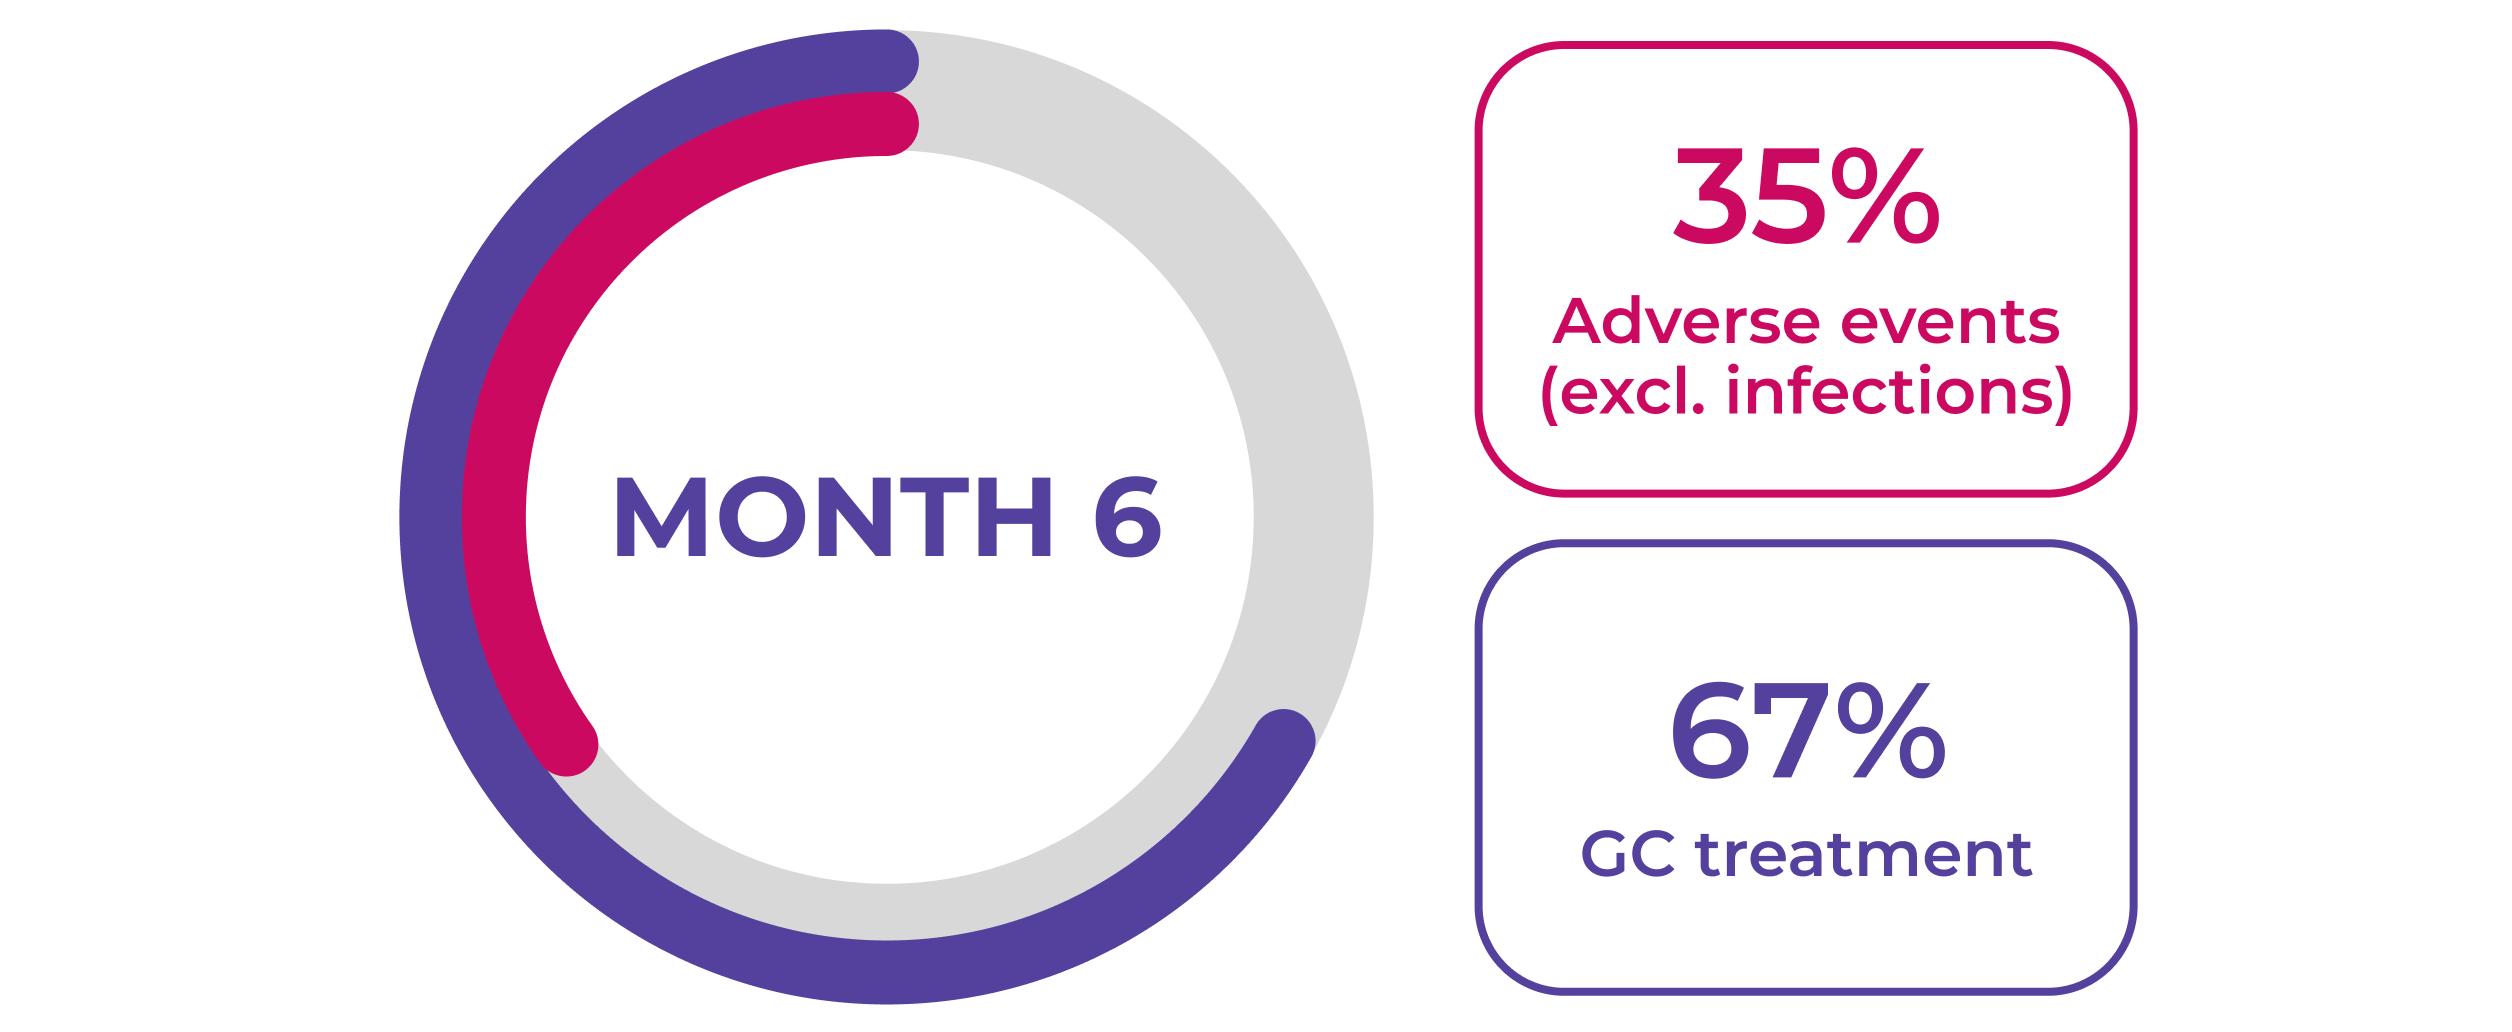
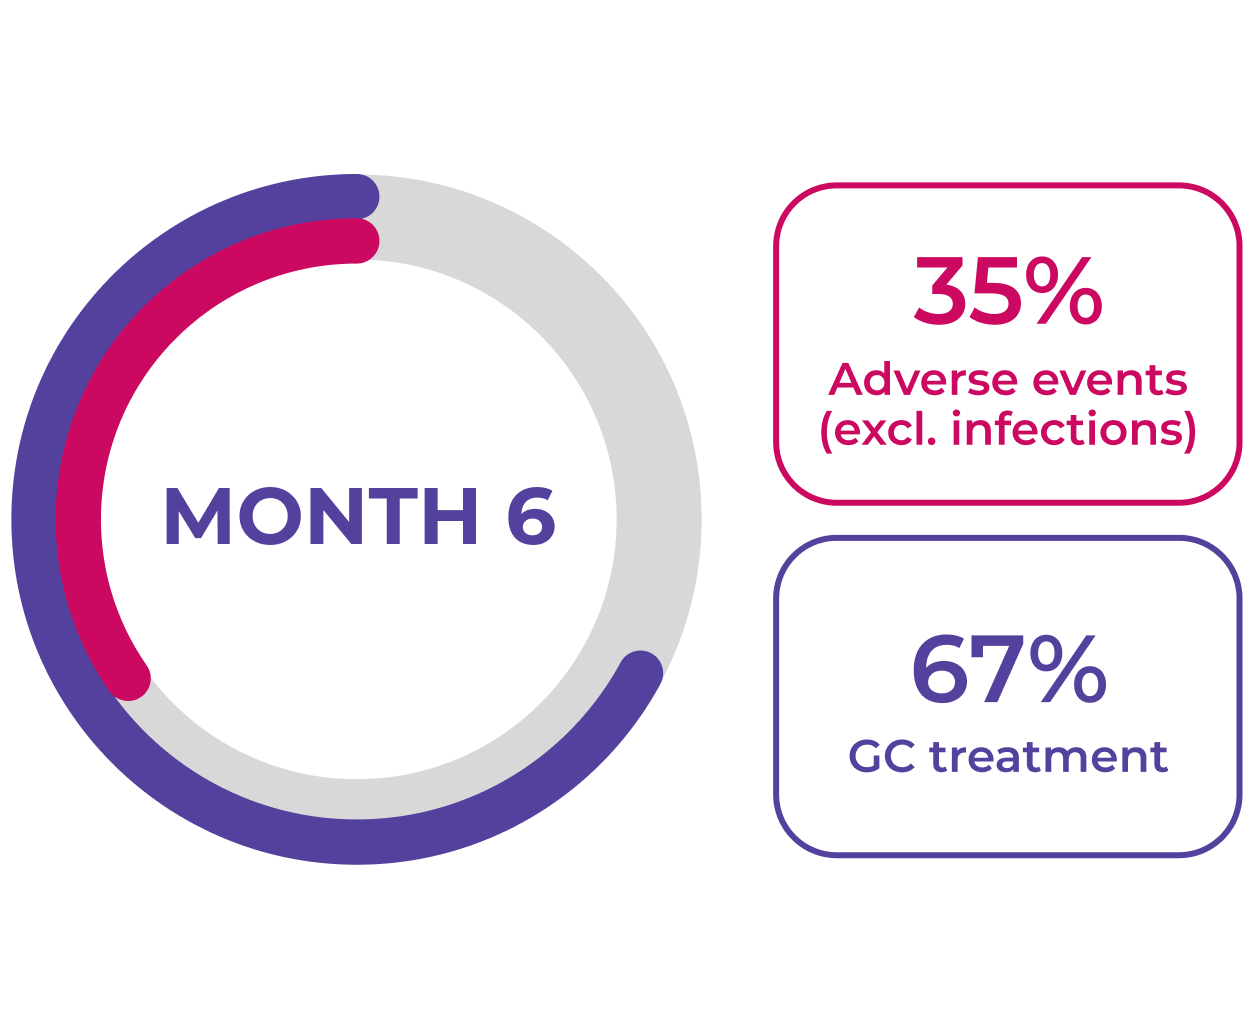
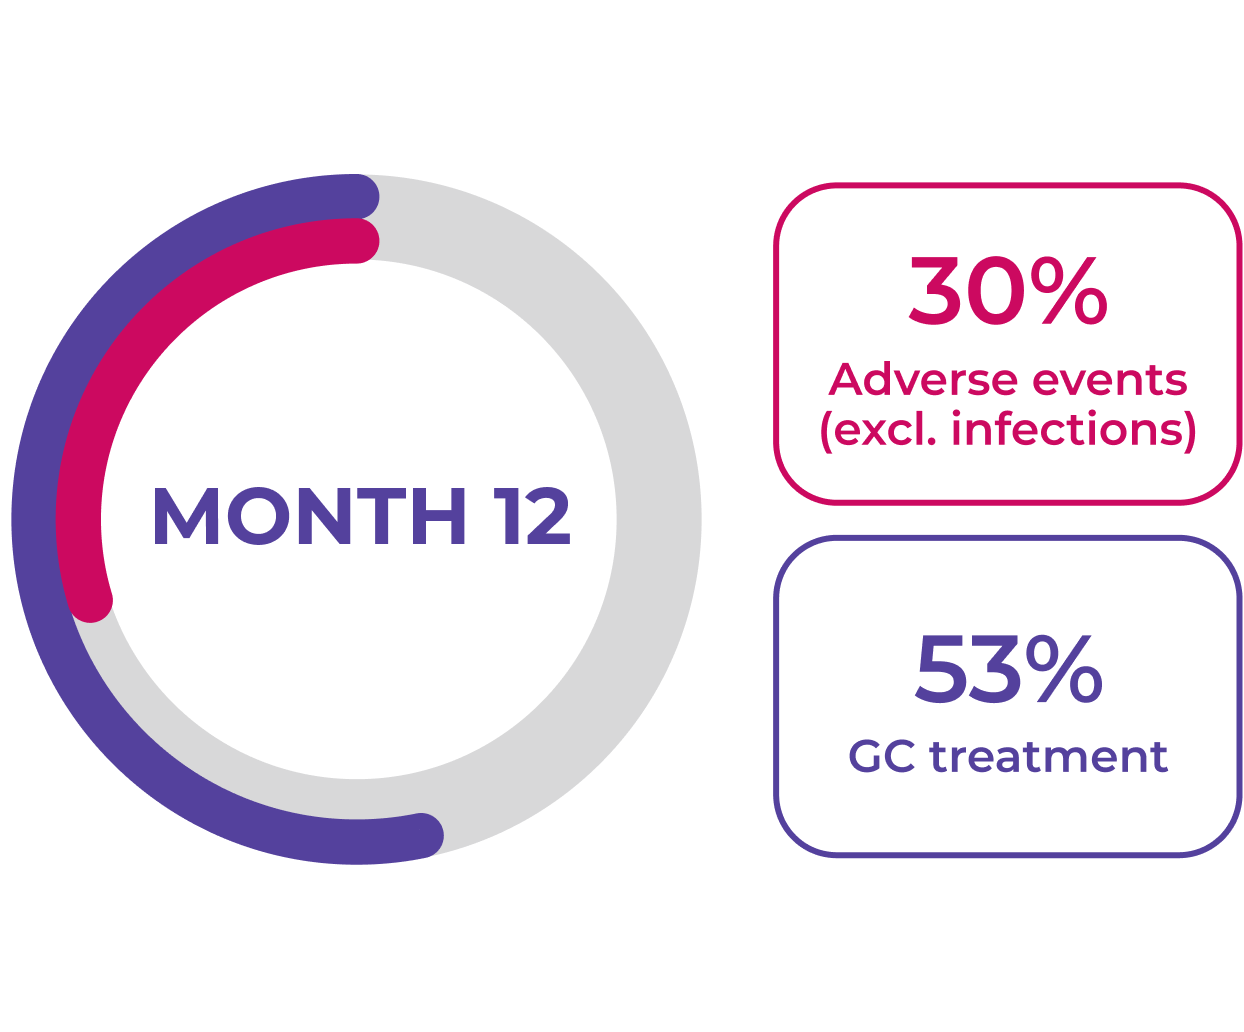
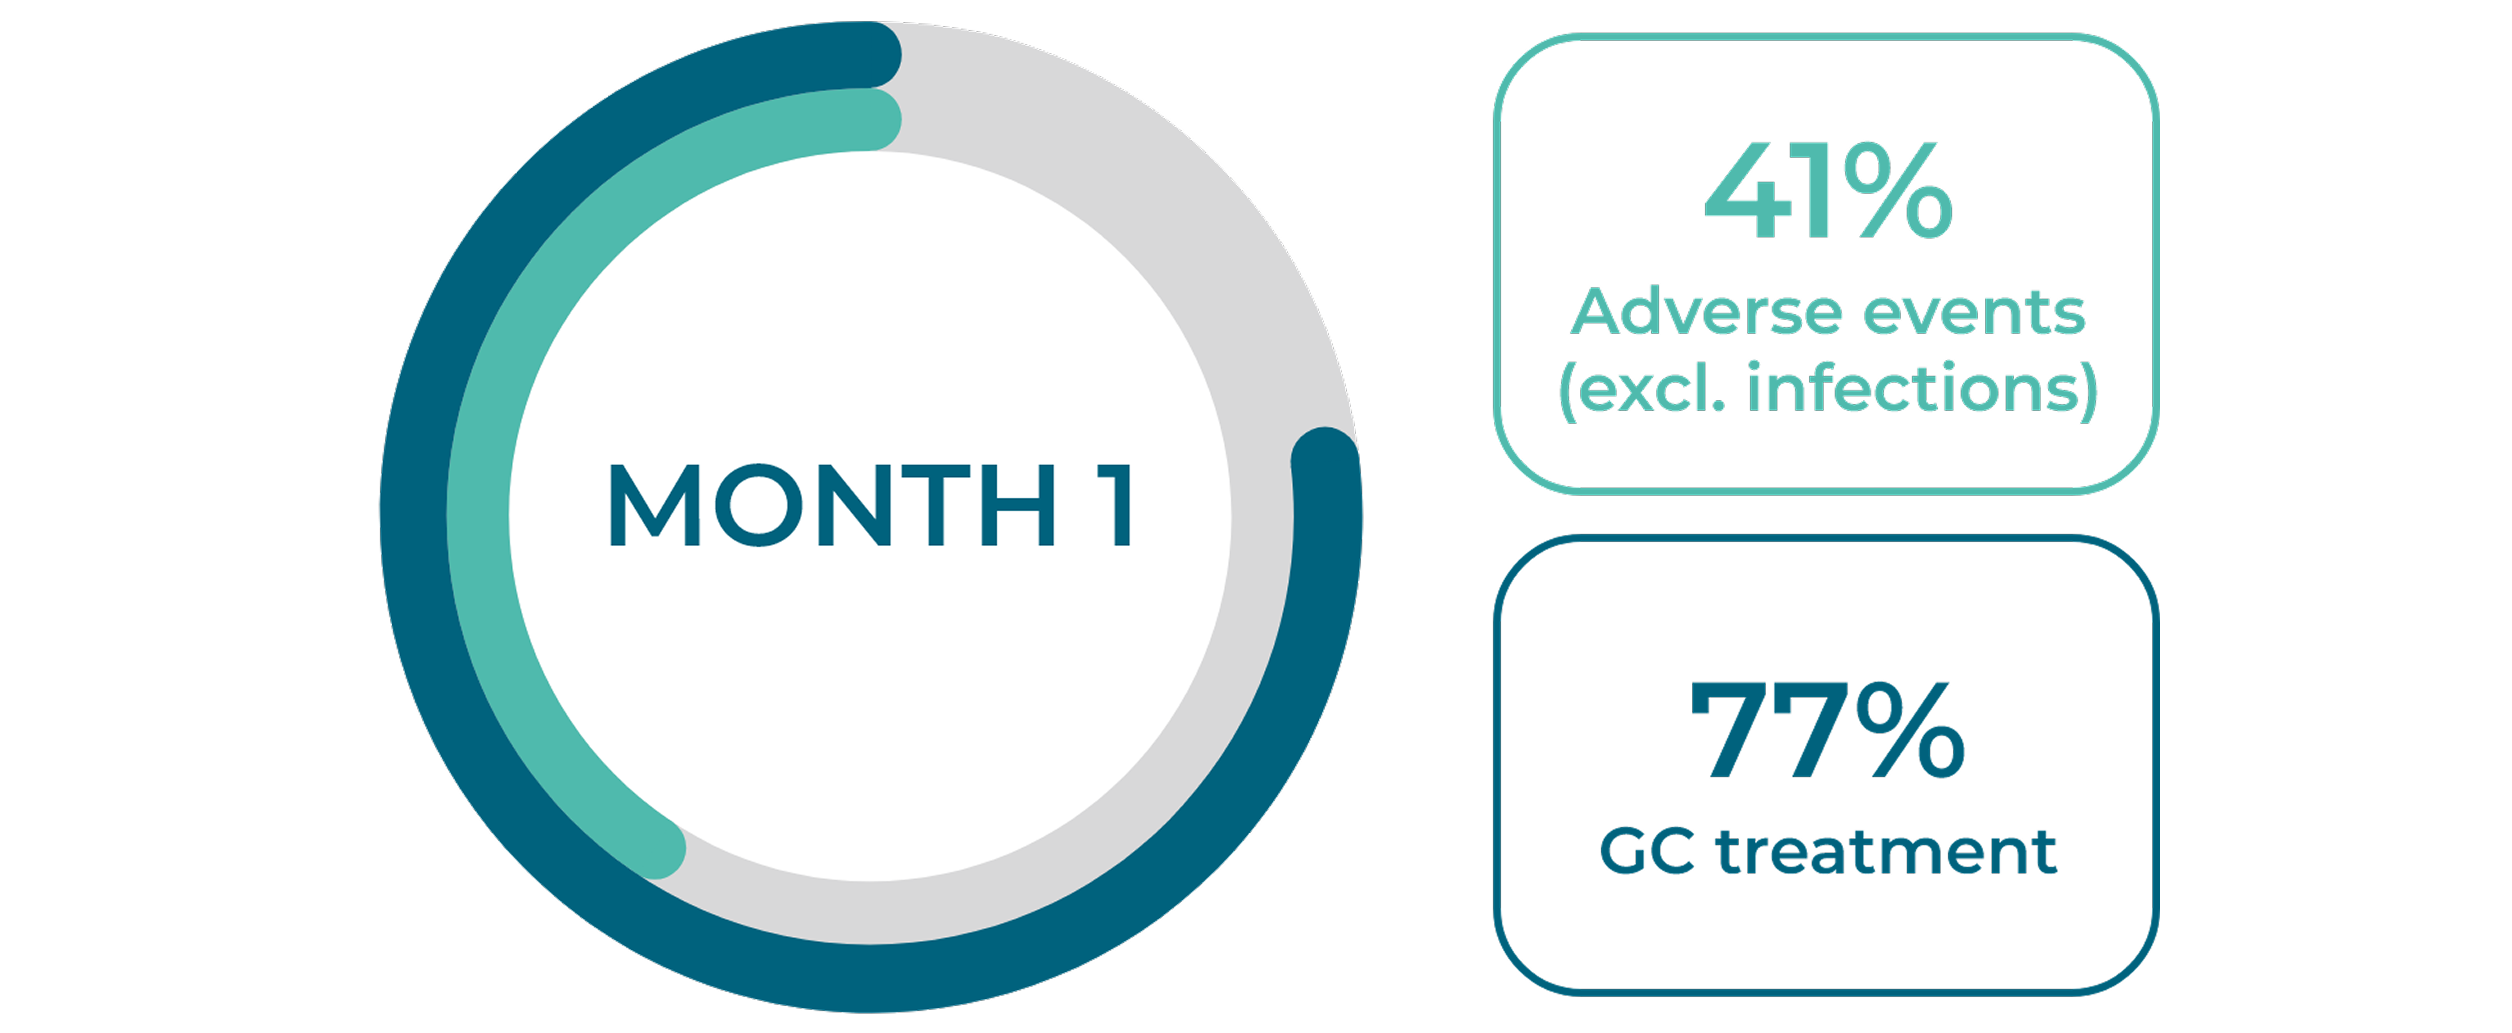
Response to induction therapy is variable and many patients do not achieve a full response, even at 12 months1

>50% of patients continue to use glucocorticoids 12 months after starting induction therapy1

AEs remain an issue for new and relapsing patients1,2
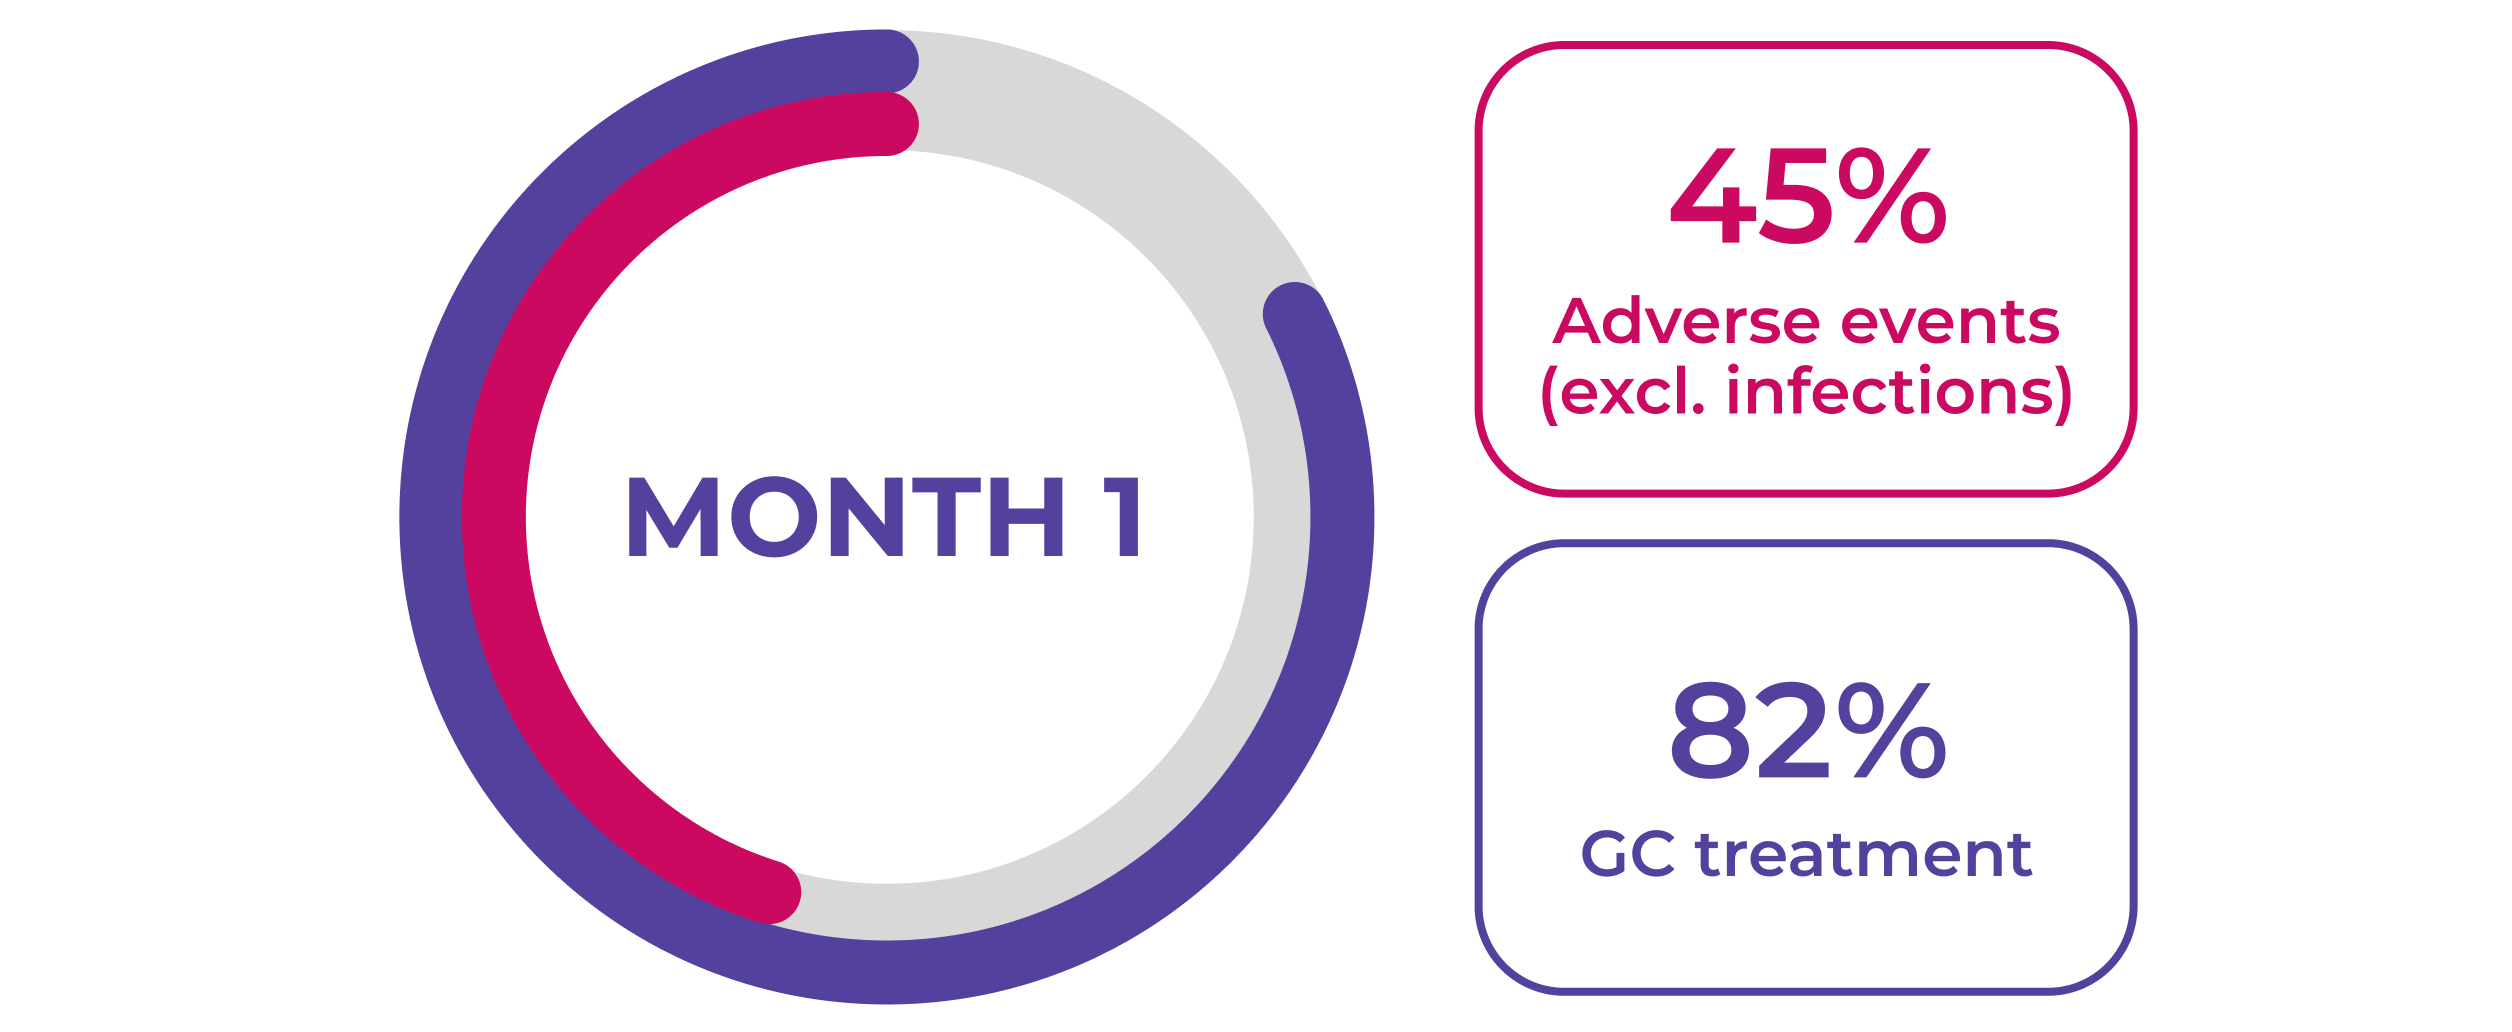
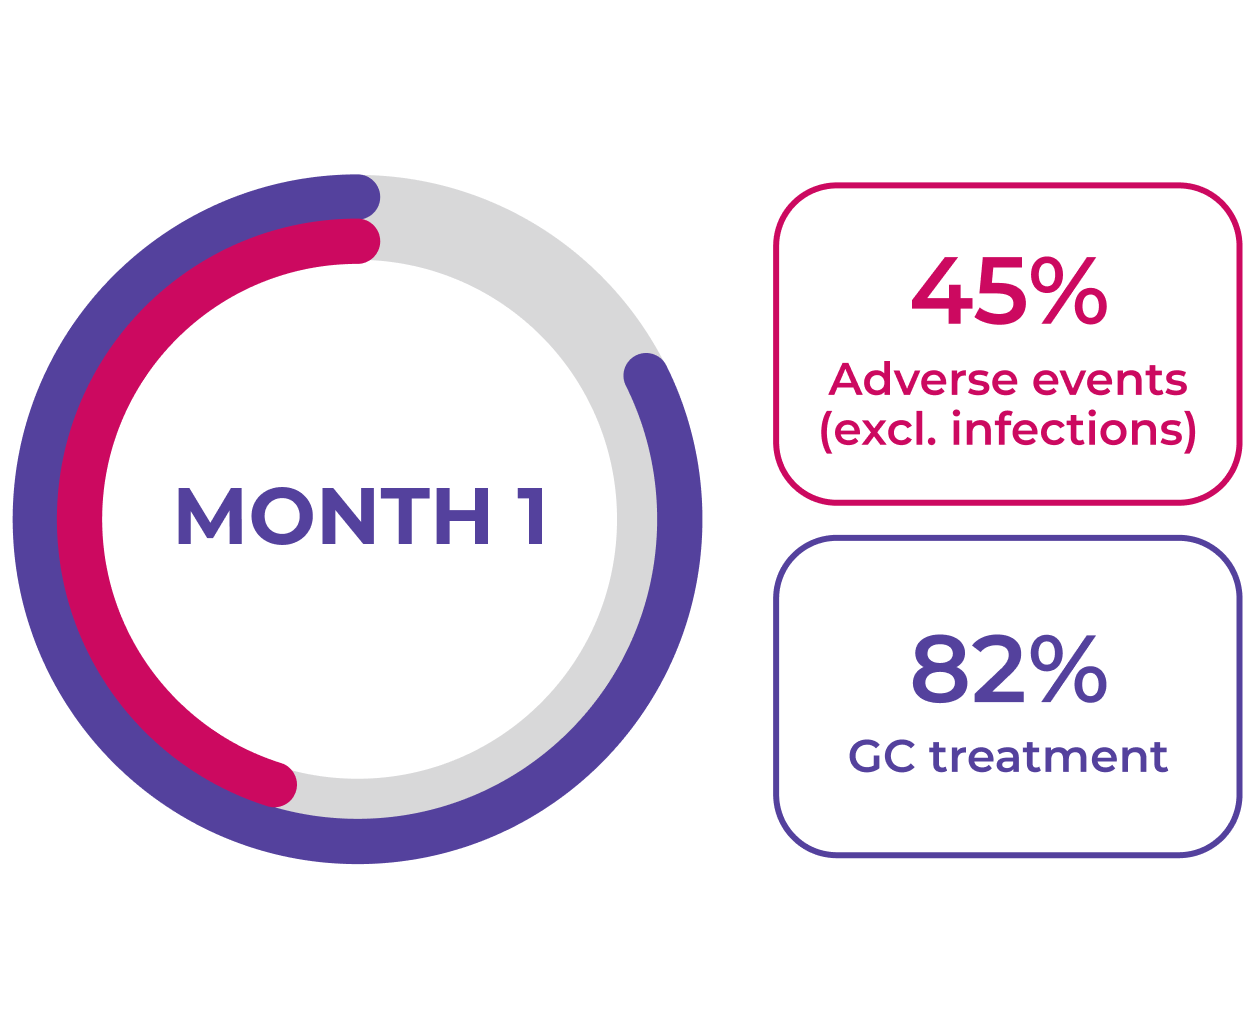
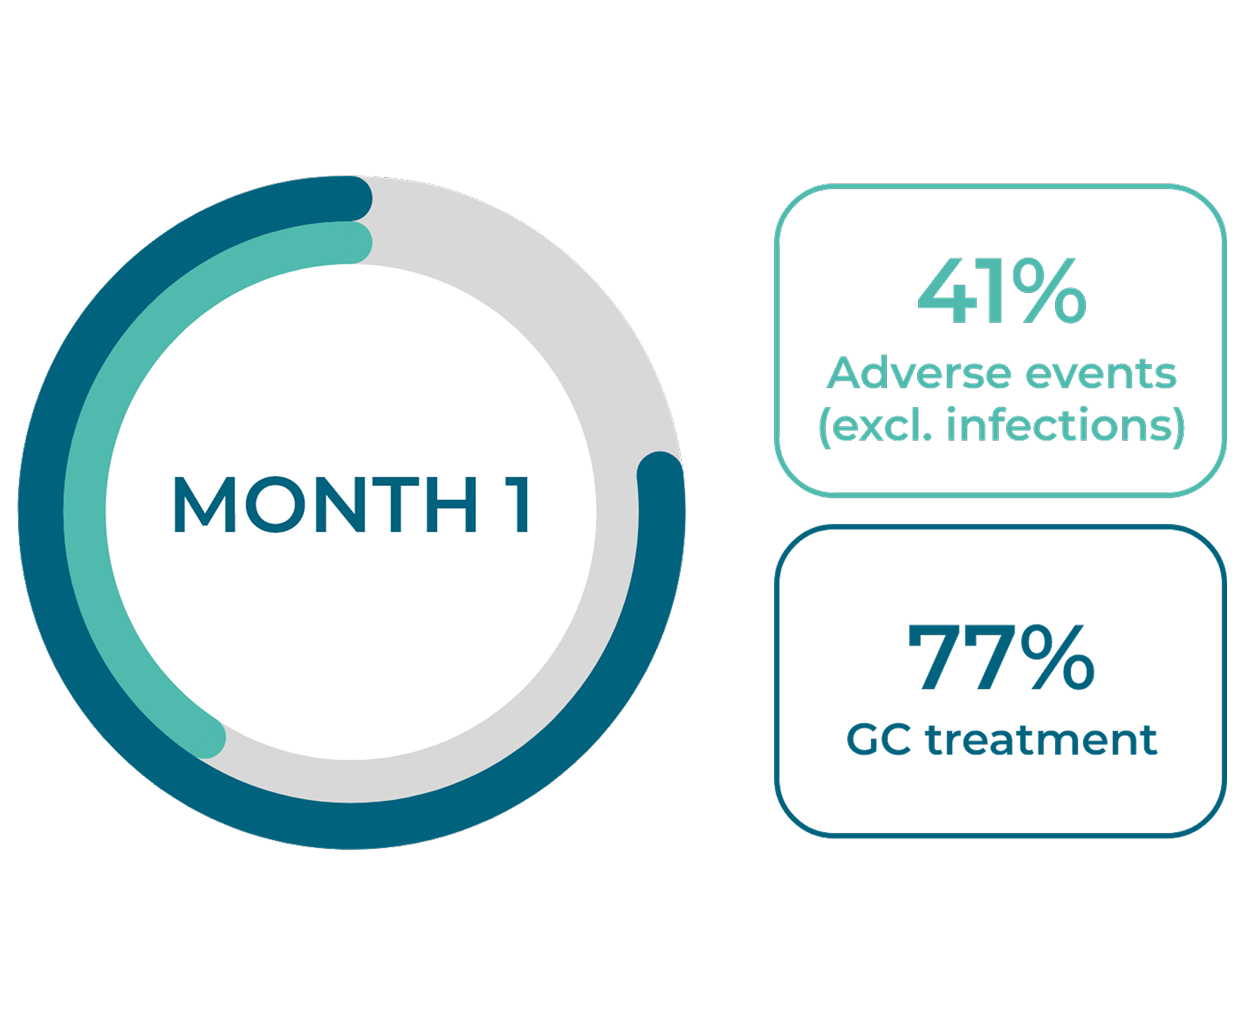
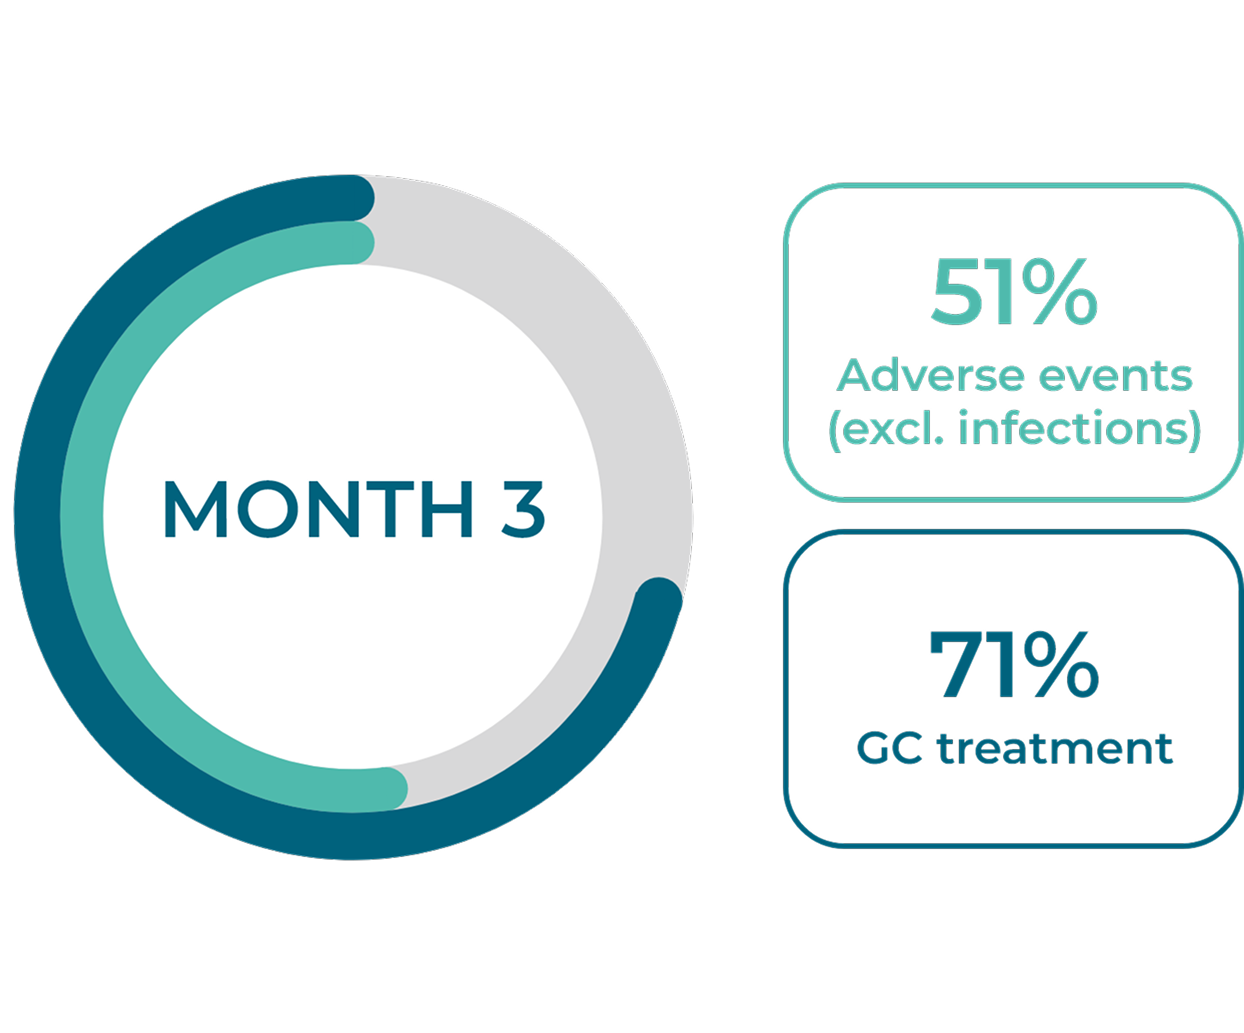
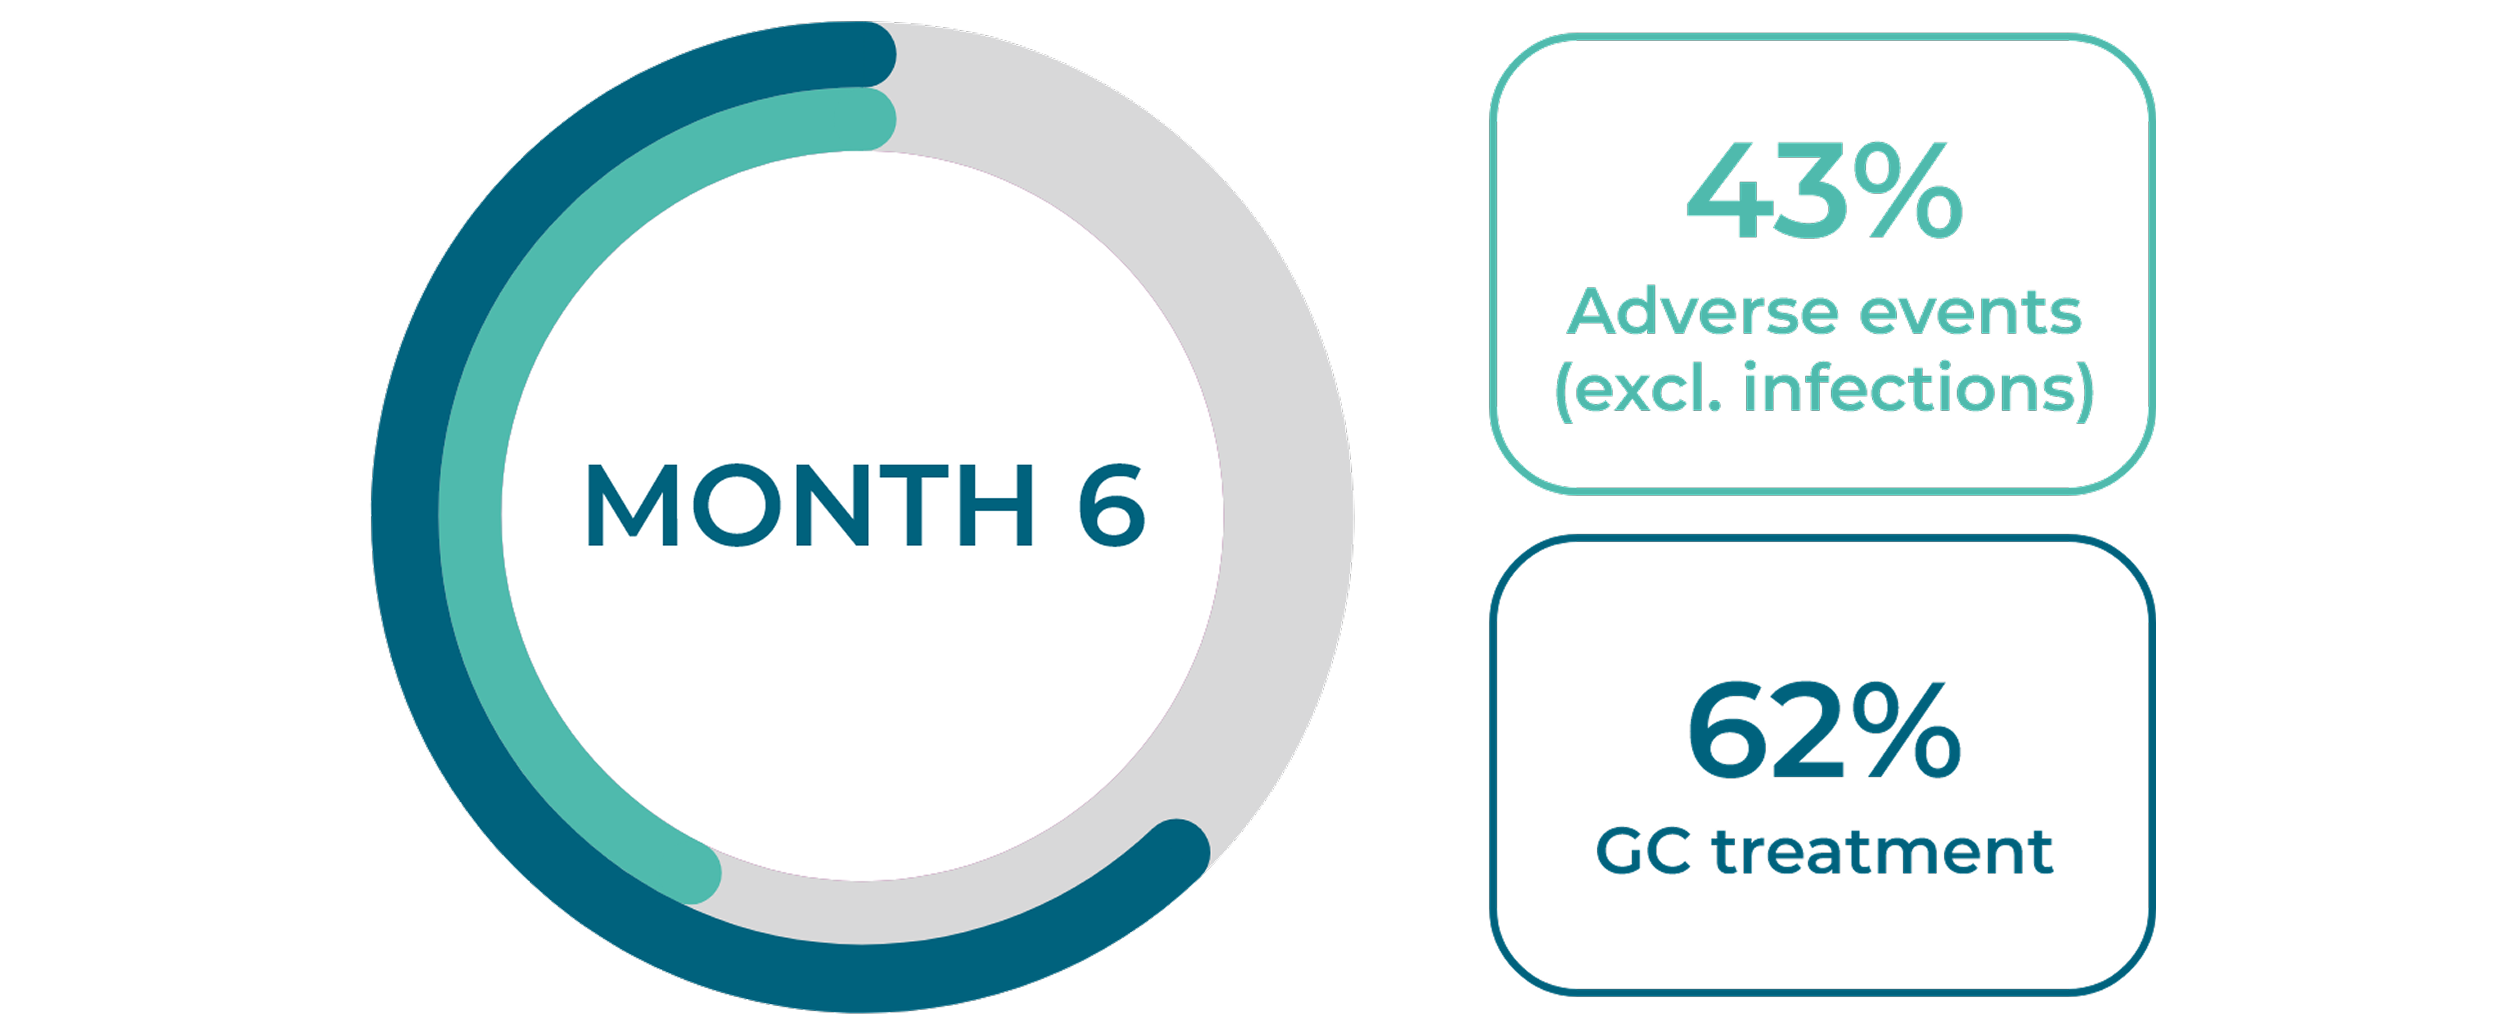
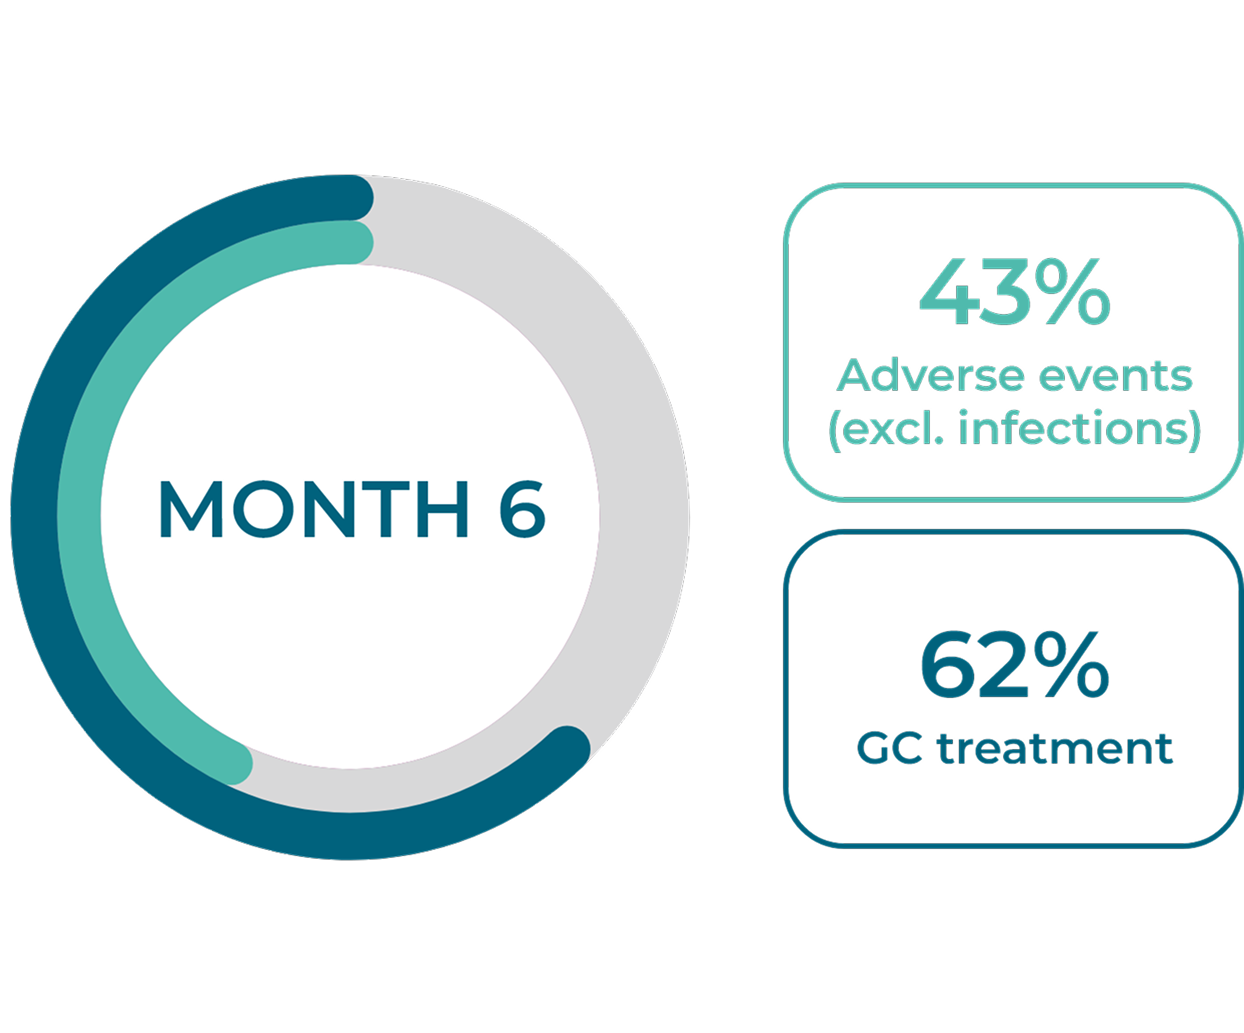
Over the first 12 months of treatment in patients with GPA or MPA, AEs are common.1,2 At this time, glucocorticoid dose is typically highest, as current treatment guidelines recommend the use of glucocorticoids for remission induction.1-3 The majority of patients continue to use glucocorticoids 12 months after starting remission induction.1,2
New patients (n=929)1†
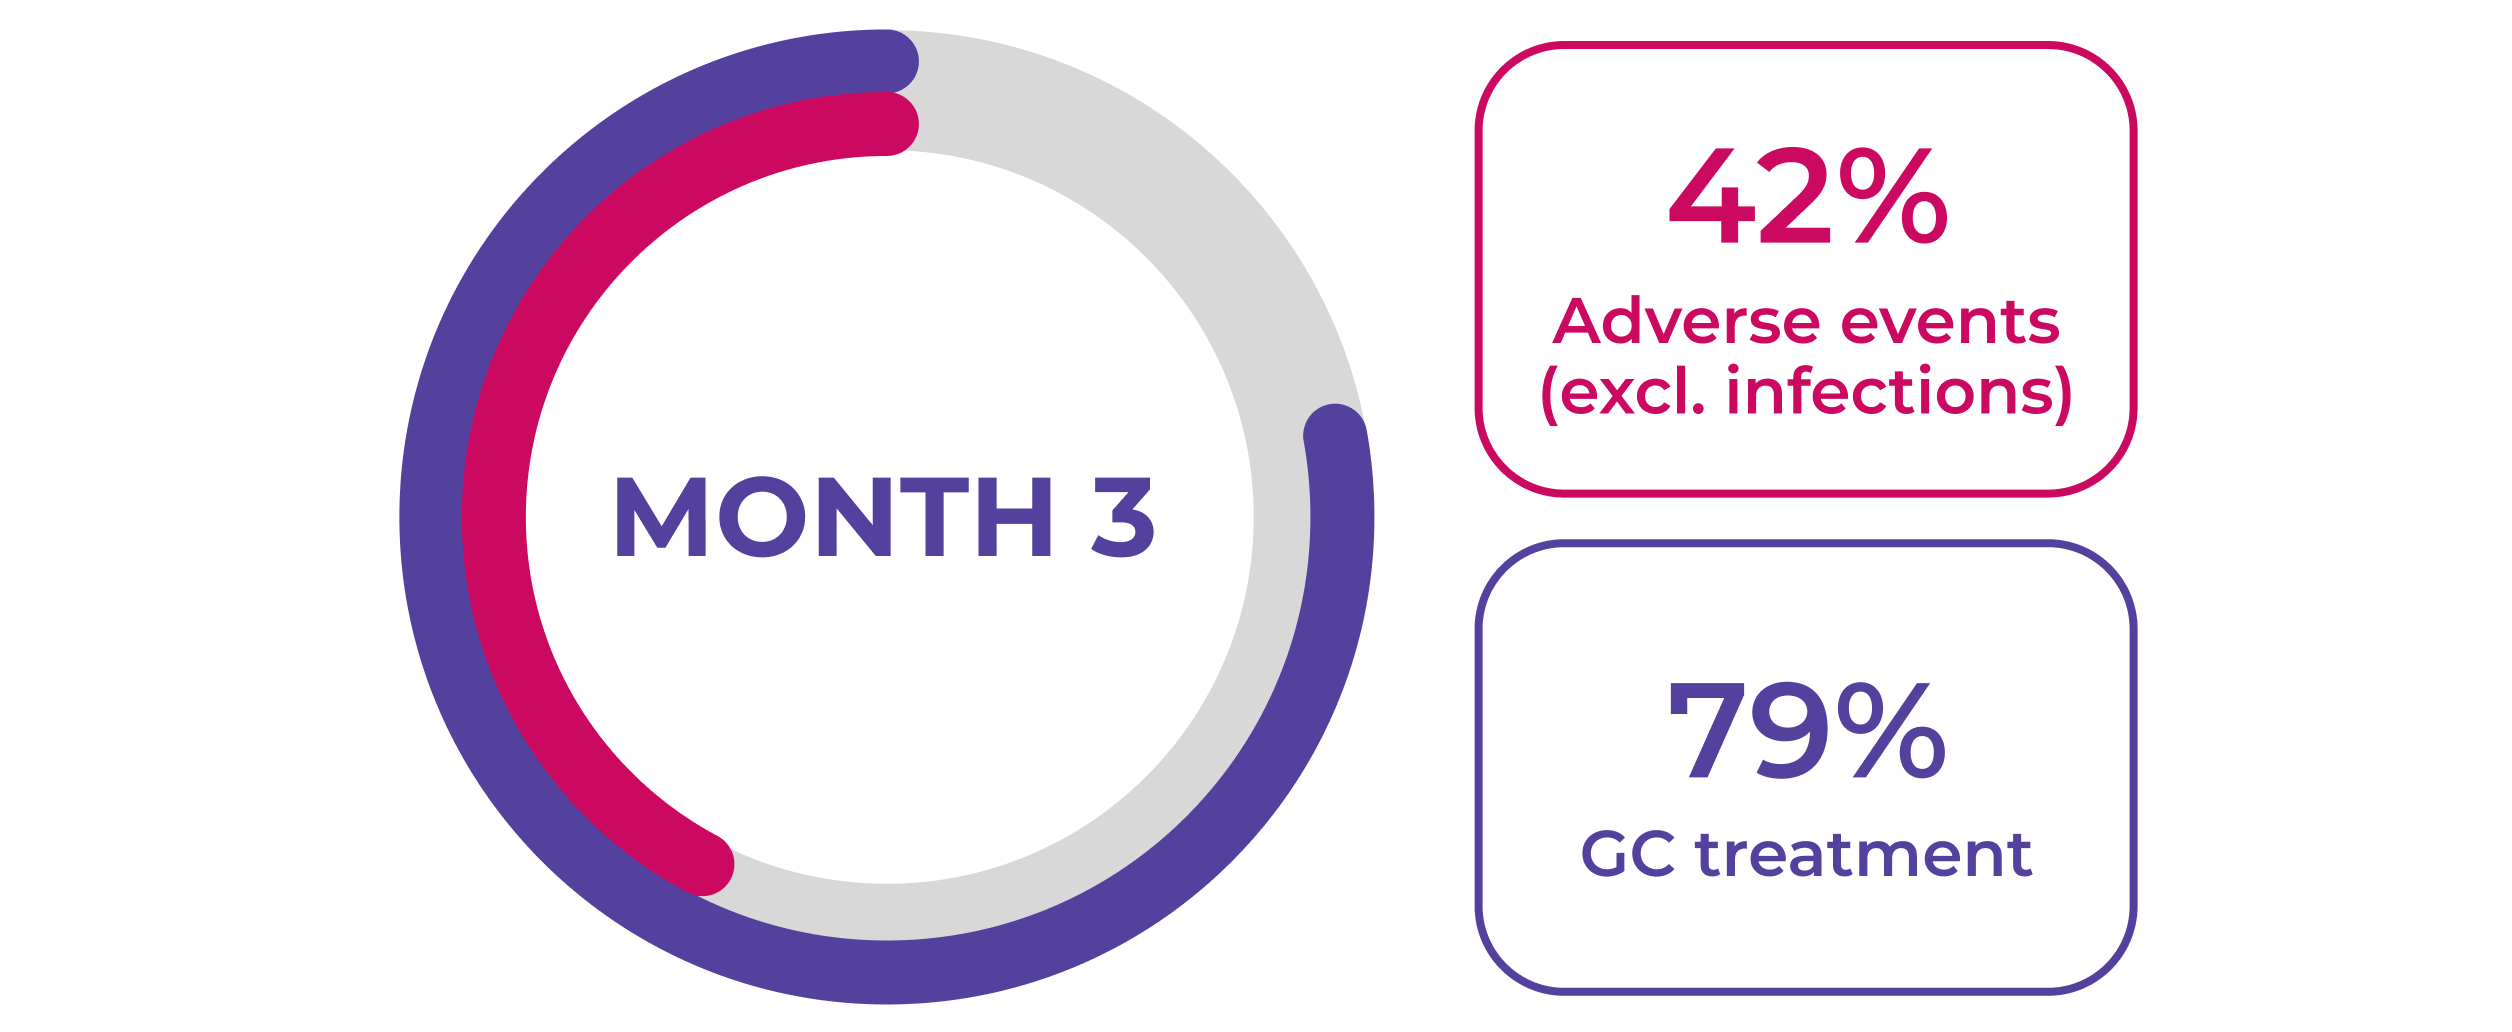


Relapsing patients (n=268)2†


References & footnotes
Footnotes
*Retrospective clinical audit of healthcare records from 929 incident AAV patients (GPA: 54%; MPA: 46%; mean age: 57 years; male: 54%) in France, Germany, Italy and the United Kingdom (399 physicians) who initiated remission induction therapy between November 2014 and February 2017 with data collected at baseline presentation, and after 1, 3, 6 and 12 months of treatment.1
†Retrospective study reviewing 929 incident AAV patients (GPA: 54%; MPA: 46%; mean age: 57 years; male: 54%) and 268 relapsing AAV patients (GPA: 54%; MPA:46%; mean age: 58 years; male: 60%) from France, Germany, Italy and the United Kingdom (399 physicians) who initiated remission induction therapy between November 2014 and February 2017 with data collected at baseline presentation, and after 1, 3, 6 and 12 months of treatment.1,2
Abbreviations
AAV, ANCA-associated vasculitis; AE, adverse event; ANCA, anti-neutrophil cytoplasmic antibody; CYC, cyclophosphamide; GC, glucocorticoid; GPA, granulomatosis with polyangiitis; MPA, microscopic polyangiitis; RTX, rituximab
References
- Rutherford P, et al. Arthritis Rheumatol 2018;70(Suppl 10):Abstract 2724.
- Rutherford PA, et al. J Am Soc Nephrol 2018;29:839(Abstract SA-PO402).
- Yates M, et al. Ann Rheum Dis 2016;75(9):1583–94.
Disease mechanism
AAV pathogenesis
The interaction between the activated alternative complement pathway, neutrophils and C5a is associated with vasculitis damage in AAV.1
The development of AAV is a complex and multifactorial autoimmune process2,3
The initial causes of AAV are currently unclear.3 Predisposing factors such as microbial infection, genetic influence, environmental agents and specific drugs are all fundamental to the development of AAV.2,3
Exposure to silica, pesticides, fumes, construction materials, hydrocarbon (cleaning agents, paint, diesel), drugs (propylthiouracil, hydralazine, D-penicillamine, cefotaxime, minocycline, anti-TNF agents, phenytoin) and certain psychoactive agents may all cause AAV.2,3
ANCA involvement
Loss of immune tolerance to ANCA antigens and development of ANCA by plasma cells2
ANCAs are most commonly directed against the neutrophil lysosomal enzymes PR3 and MPO in GPA and MPA, respectively2-6
Neutrophils are primed
Neutrophils are primed by inflammatory cytokines (TNF-α, IL-1 and IL-18) produced in response to an infection or another event, with genetic predisposition also relevant3,7,8
ANCA antigens presented
Primed neutrophils present ANCA antigens (e.g. MPO and PR3) at their cell surface that bind to ANCA, resulting in neutrophil activation2,3,7,8
Inflammation mediators released
Activated neutrophils adhere to and penetrate the blood vessel wall, and release mediators of inflammation and cell injury, e.g. NETS2,3,7
Alternative complement pathway activated
Activated neutrophils also release factors such as properdin that have an autocrine role in activating the alternative complement pathway, leading to the generation of C5a2,7
Binding of C5a to C5aR1
Binding of C5a to C5aR1 amplifies ANCA-induced inflammation and vascular damage7
Necrotising vasculitis
This process leads to necrotising vasculitis in small blood vessels7
Chronic inflammation
Over a few days, acute inflammation and necrosis are replaced by chronic inflammation and scarring7
References & footnotes
Abbreviations
AAV, ANCA-associated vasculitis; ANCA, anti-neutrophil cytoplasmic antibody; C5a, complement 5a; GPA, granulomatosis with polyangiitis; IL, interleukin; MPA, microscopic polyangiitis; MPO, myeloperoxidase; NETS, neutrophil extracellular traps; PR3, proteinase 3; R, receptor; TNF, tumour necrosis factor
References
- Bekker P, et al. Characterization of Pharmacologic and Pharmacokinetic Properties of CCX168, a Potent and Selective Orally Administered Complement 5a Receptor Inhibitor, Based on Preclinical Evaluation and Randomized Phase 1 Clinical Study. PLoS One 2016;11(10):e0164646.
- Hutton HL, et al. ANCA-Associated Vasculitis: Pathogenesis, Models, and Preclinical Testing. Semin Nephrol 2017;37(5):418–35.
- Al-Hussain T, et al. Pathophysiology of ANCA-associated Vasculitis. Adv Anat Pathol 2017;24(4):226–34.
- Chen M, et al. Antineutrophil cytoplasmic autoantibody-associated vasculitis in older patients. Medicine (Baltimore) 2008;87(4):203–9.
- Lionaki S, et al. Classification of antineutrophil cytoplasmic autoantibody vasculitides: the role of antineutrophil cytoplasmic autoantibody specificity for myeloperoxidase or proteinase 3 in disease recognition and prognosis. Arthritis Rheum 2012;64(10):3452–62.
- Pagnoux C. Updates in ANCA-associated vasculitis. Eur J Rheumatol 2016;3(3):122–33.
- Jennette JC, Nachman PH. ANCA Glomerulonephritis and Vasculitis. Clin J Am Soc Nephrol 2017;12(10):1680–91.
- von Borstel A, et al. Cellular immune regulation in the pathogenesis of ANCA-associated vasculitides. Autoimmun Rev 2018;17(4):413–21.
Disease mechanism
The importance of complement and neutrophils in AAV activation
C5a plays a major role in the pathogenesis of AAV, amplifying ANCA-induced inflammation and vascular damage1
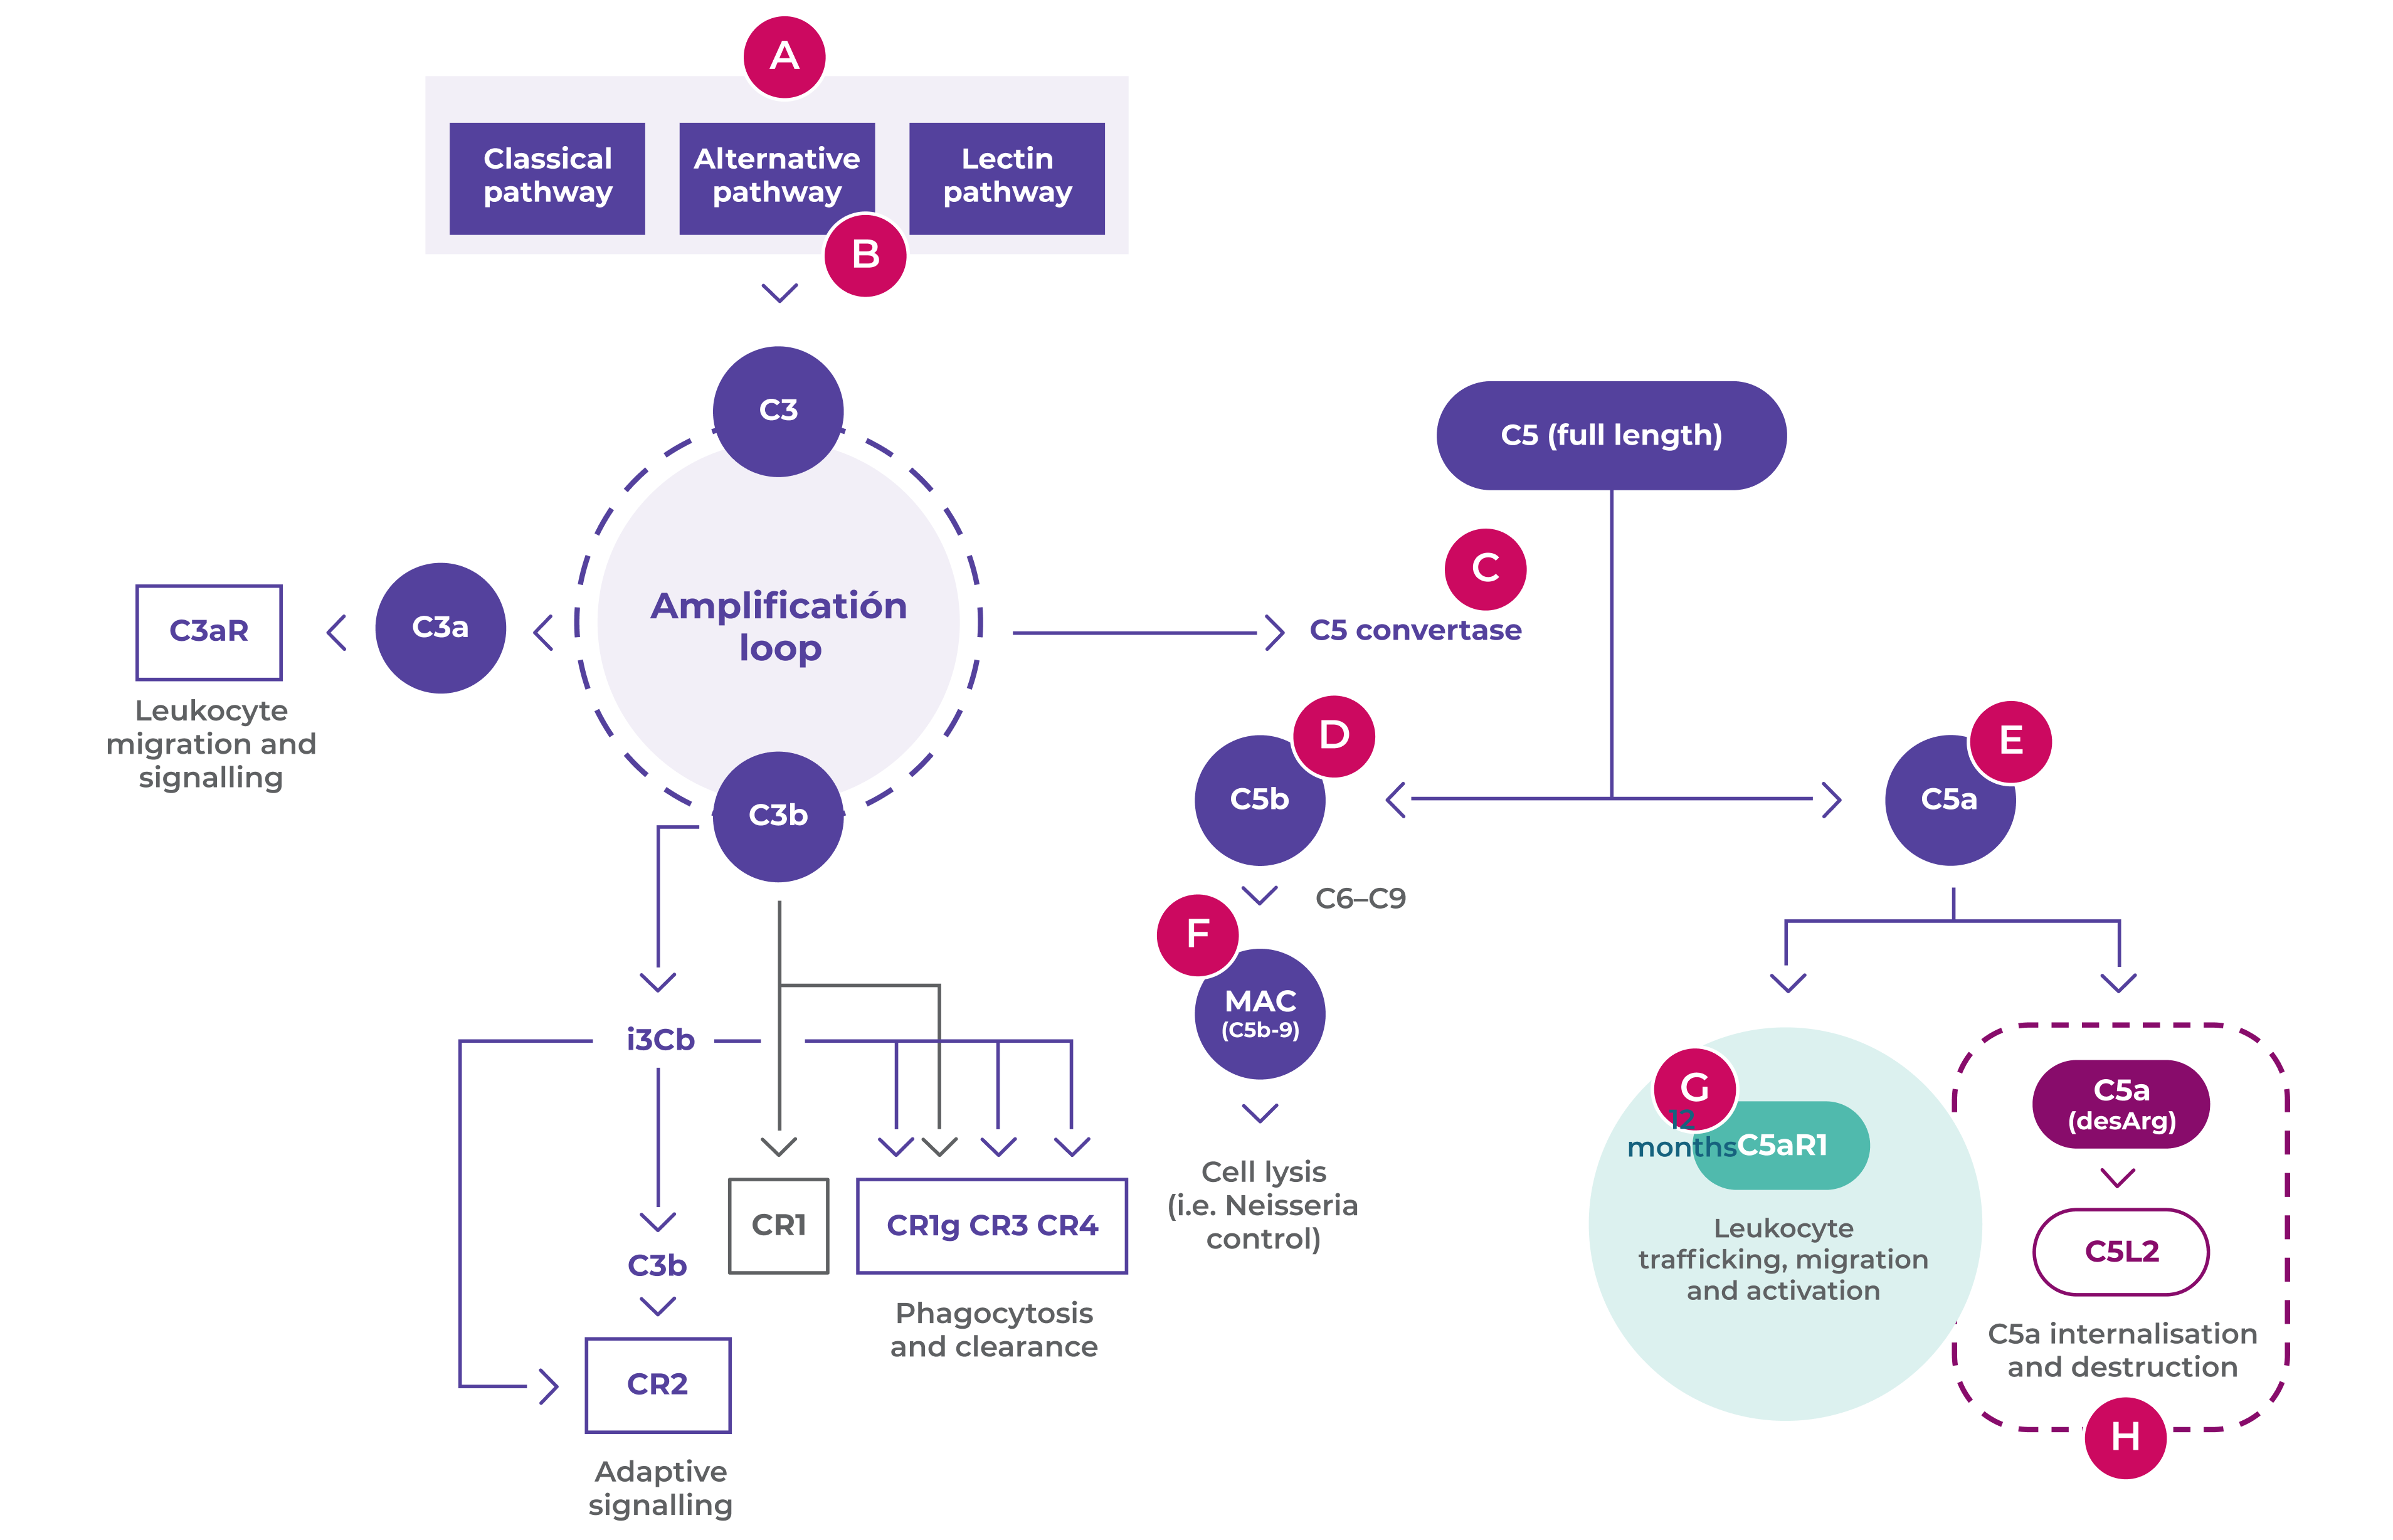
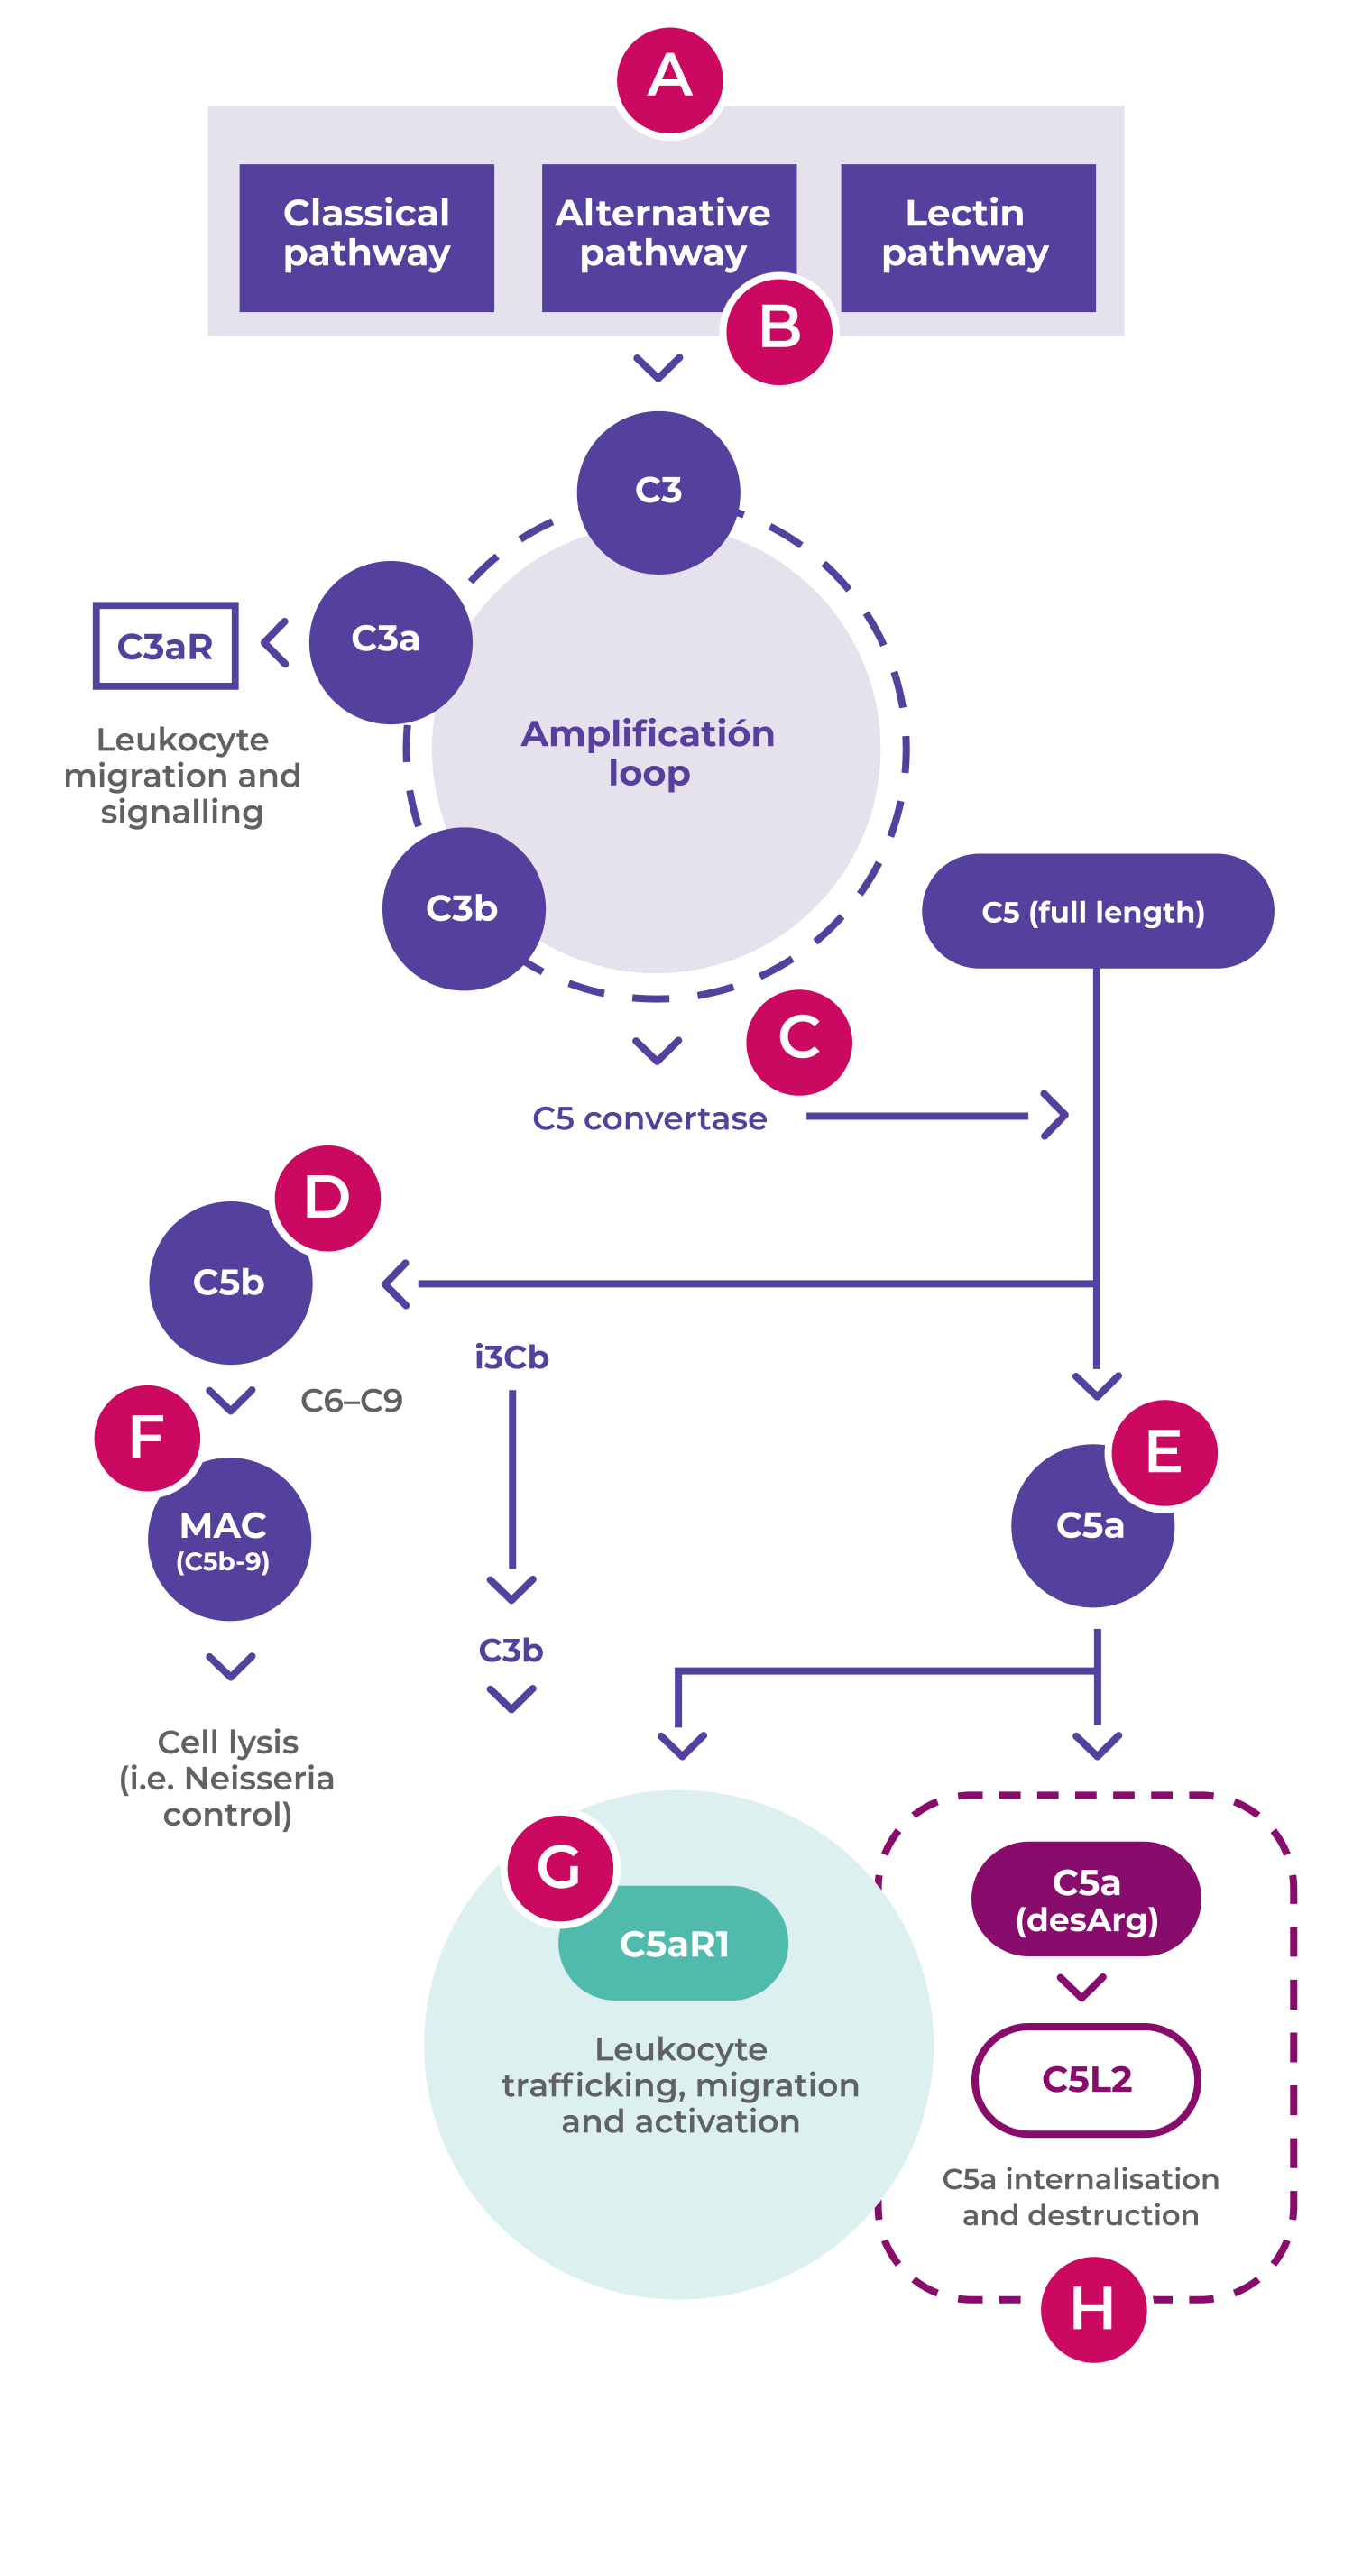
Diagram adapted from Bekker P, et al. PLoS One 2016
A. The three pathways of complement activation (classical, lectin and alternative) result in the formation of C3a, C3b, C5a and C5b-91.
B. The alternative complement pathway is constantly ticking over through the spontaneous breakdown of C3 to C3b.2 It is the dysregulation of this pathway that is relevant in AAV1.
C. C5 convertase formed during the amplification loop cleaves C5 into C5a and C5b1.
D. C5b combines with complement components C6, C7, C8 and C9 to form C5b-9, also known as the terminal complement complex or membrane attack complex1.
E. C5a is the downstream terminal effector molecule in the complement cascade and a potent pro-inflammatory mediator critical in AAV1,4.
F. C5b-9 is needed for host resistance to encapsulated bacterial infections, such as Neisseria meningitides1,3.
G. Binding of C5a to C5aR1 results in two key events that act in a vicious cycle to amplify ANCA-induced inflammation and vascular damage:1,4,5.
- Rapid induction of the expression of adhesion molecules on the cell surface that causes leukocyte chemotaxis1.
- Further exposure of ANCA antigens at the neutrophil cell surface facilitates subsequent neutrophil activation5.
C5aR1 is also thought to play a role in promoting autoimmunity to ANCA antigens andincreasing ANCA production.6
In addition, C5a mediates inflammation by stimulating vascular permeability, neutrophil degranulation, and release of lysosomal proteases and oxidative freeradicals1,7.
H. C5L2 activation does not play a role in AAV; in other conditions, it has a currently unclear pattern of pro- and anti-inflammatory actions1,8.
C5a is rapidly degraded by removal of the C-terminal arginine, forming C5a des Arg with approximately 10-fold reduced activity on C5aR11,9.
C5a des Arg binds with high affinity to the C5L2 receptor, and is subsequently internalised and degraded1,10.
References & footnotes
Abbreviations
AAV, ANCA-associated vasculitis; ANCA, anti-neutrophil cytoplasmic antibody; C-terminal, carboxy terminal; MAC, membrane attack complex; R, receptor
References
- Bekker P, et al. PLoS One 2016;11(10):e0164646.
- Thurman JM, Holers VM. J Immunol 2006;176(3):1305–10.
- Figueroa JE, Densen P. Clin Microbiol Rev 1991;4(3):359–95.
- Jennette JC, Nachman PH. Clin J Am Soc Nephrol 2017;12(10):1680–91.
- Jennette JC, et al. Semin Nephrol 2013;33(6):557–64.
- Dick J, et al. Kidney Int 2018;93(3):615–25.
- Gerard C, et al. Annu Rev Immunol 1994;12:775–808.
- Li R, et al. FASEB J 2013;27(3):855–64.
- Monk PN, et al. Br J Pharmacol 2007;152(4):429–48.
- Cain SA, Monk PN. J Biol Chem 2002;277(9):7165–9.



