


Efficacy

Significant and superior proteinuria reduction vs maximum-labeled dose irbesartan3
FILSPARI delivered significant and superior proteinuria reduction at Week 36 vs maximum-labeled dose irbesartan2,3
% Change from baseline in UP/C at Week 363
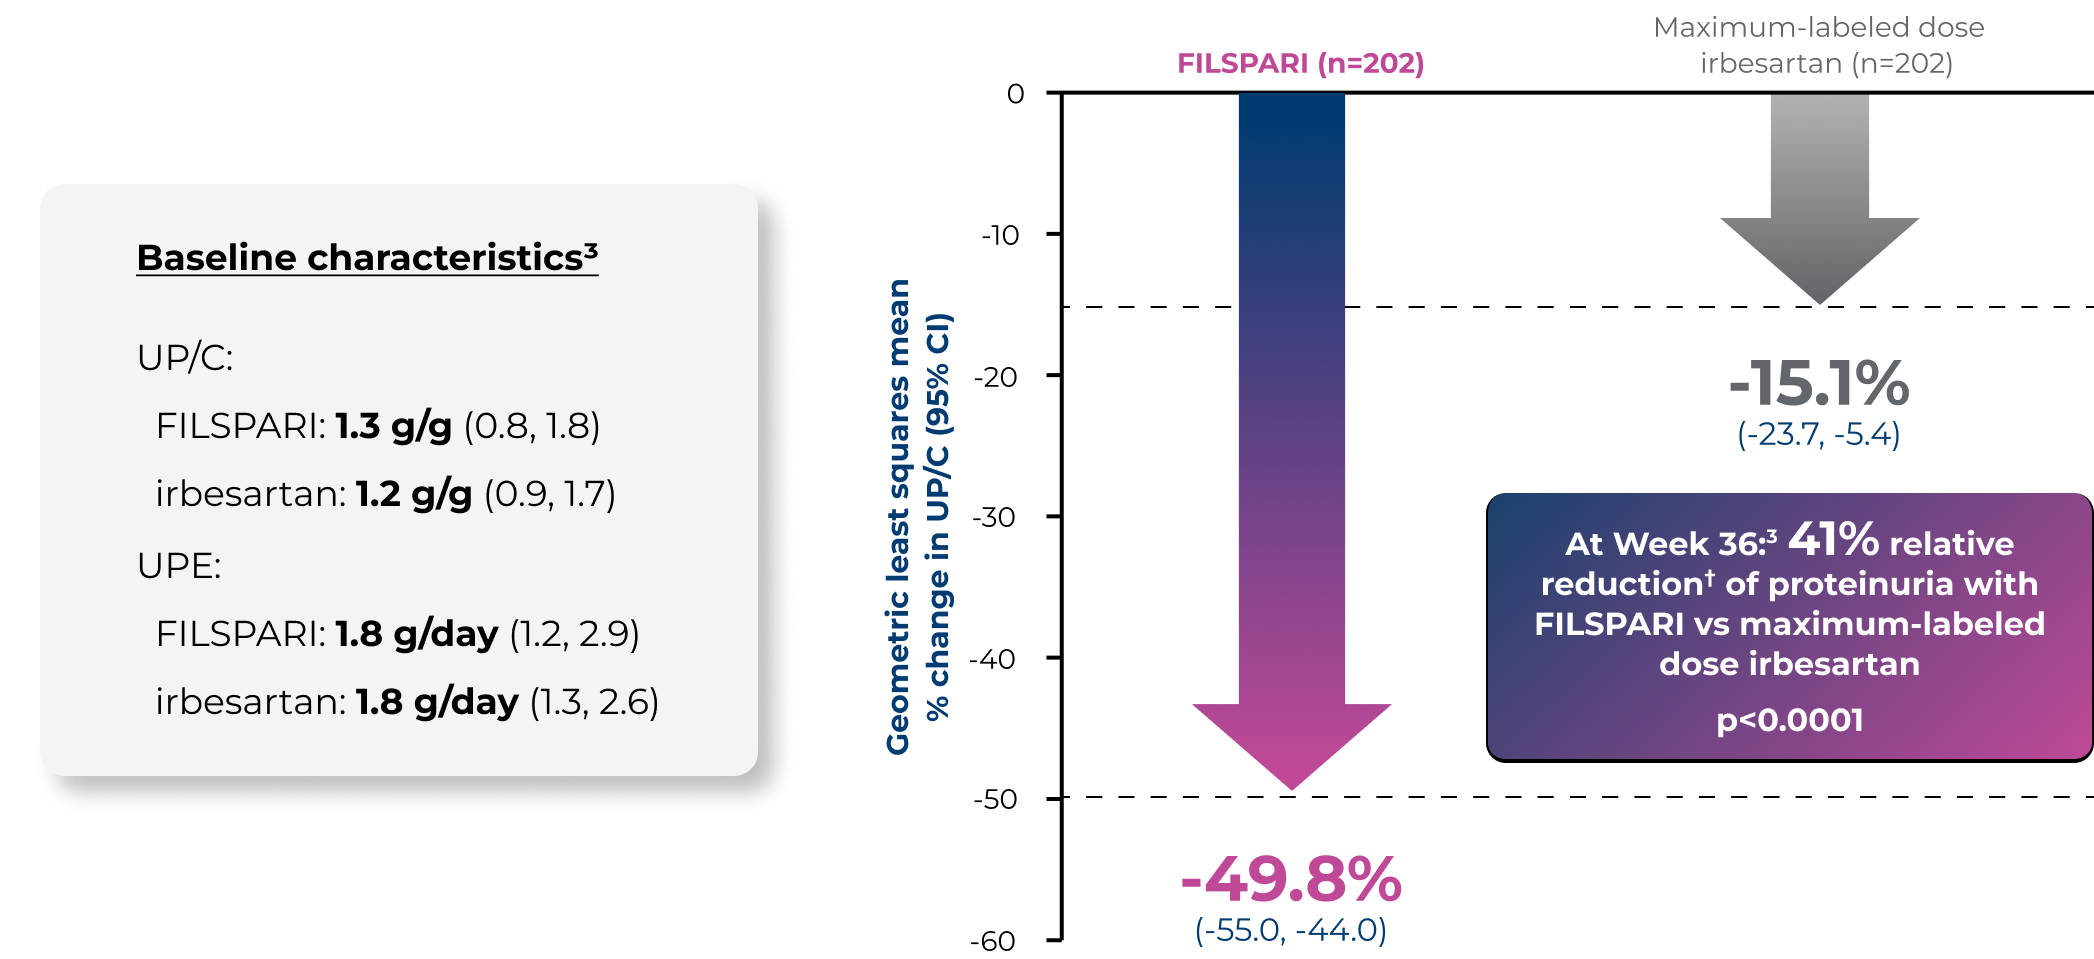

Adapted from Heerspink, et al. 20233
Consistent treatment effect across subgroups including baseline proteinuria and eGFR levels3,7
Subgroups defined by: baseline demographic characteristics such as age, sex, race, geographic region, and baseline BMI; baseline eGFR and UPE; and baseline IgAN and medical history, such as age at IgAN diagnosis, kidney biopsy to time of informed consent, history of hypotension, and baseline use of antihypertensive medications7
Rapid‡ and sustained proteinuria reduction2,3*
FILSPARI achieved rapid‡ and sustained proteinuria reduction vs maximum labeled-dose irbesartan2,3
The significant reduction of proteinuria at Week 36 was sustained through Week 110 vs maximum-labeled dose irbesartan2
% Change from baseline in UP/C to Week 1102
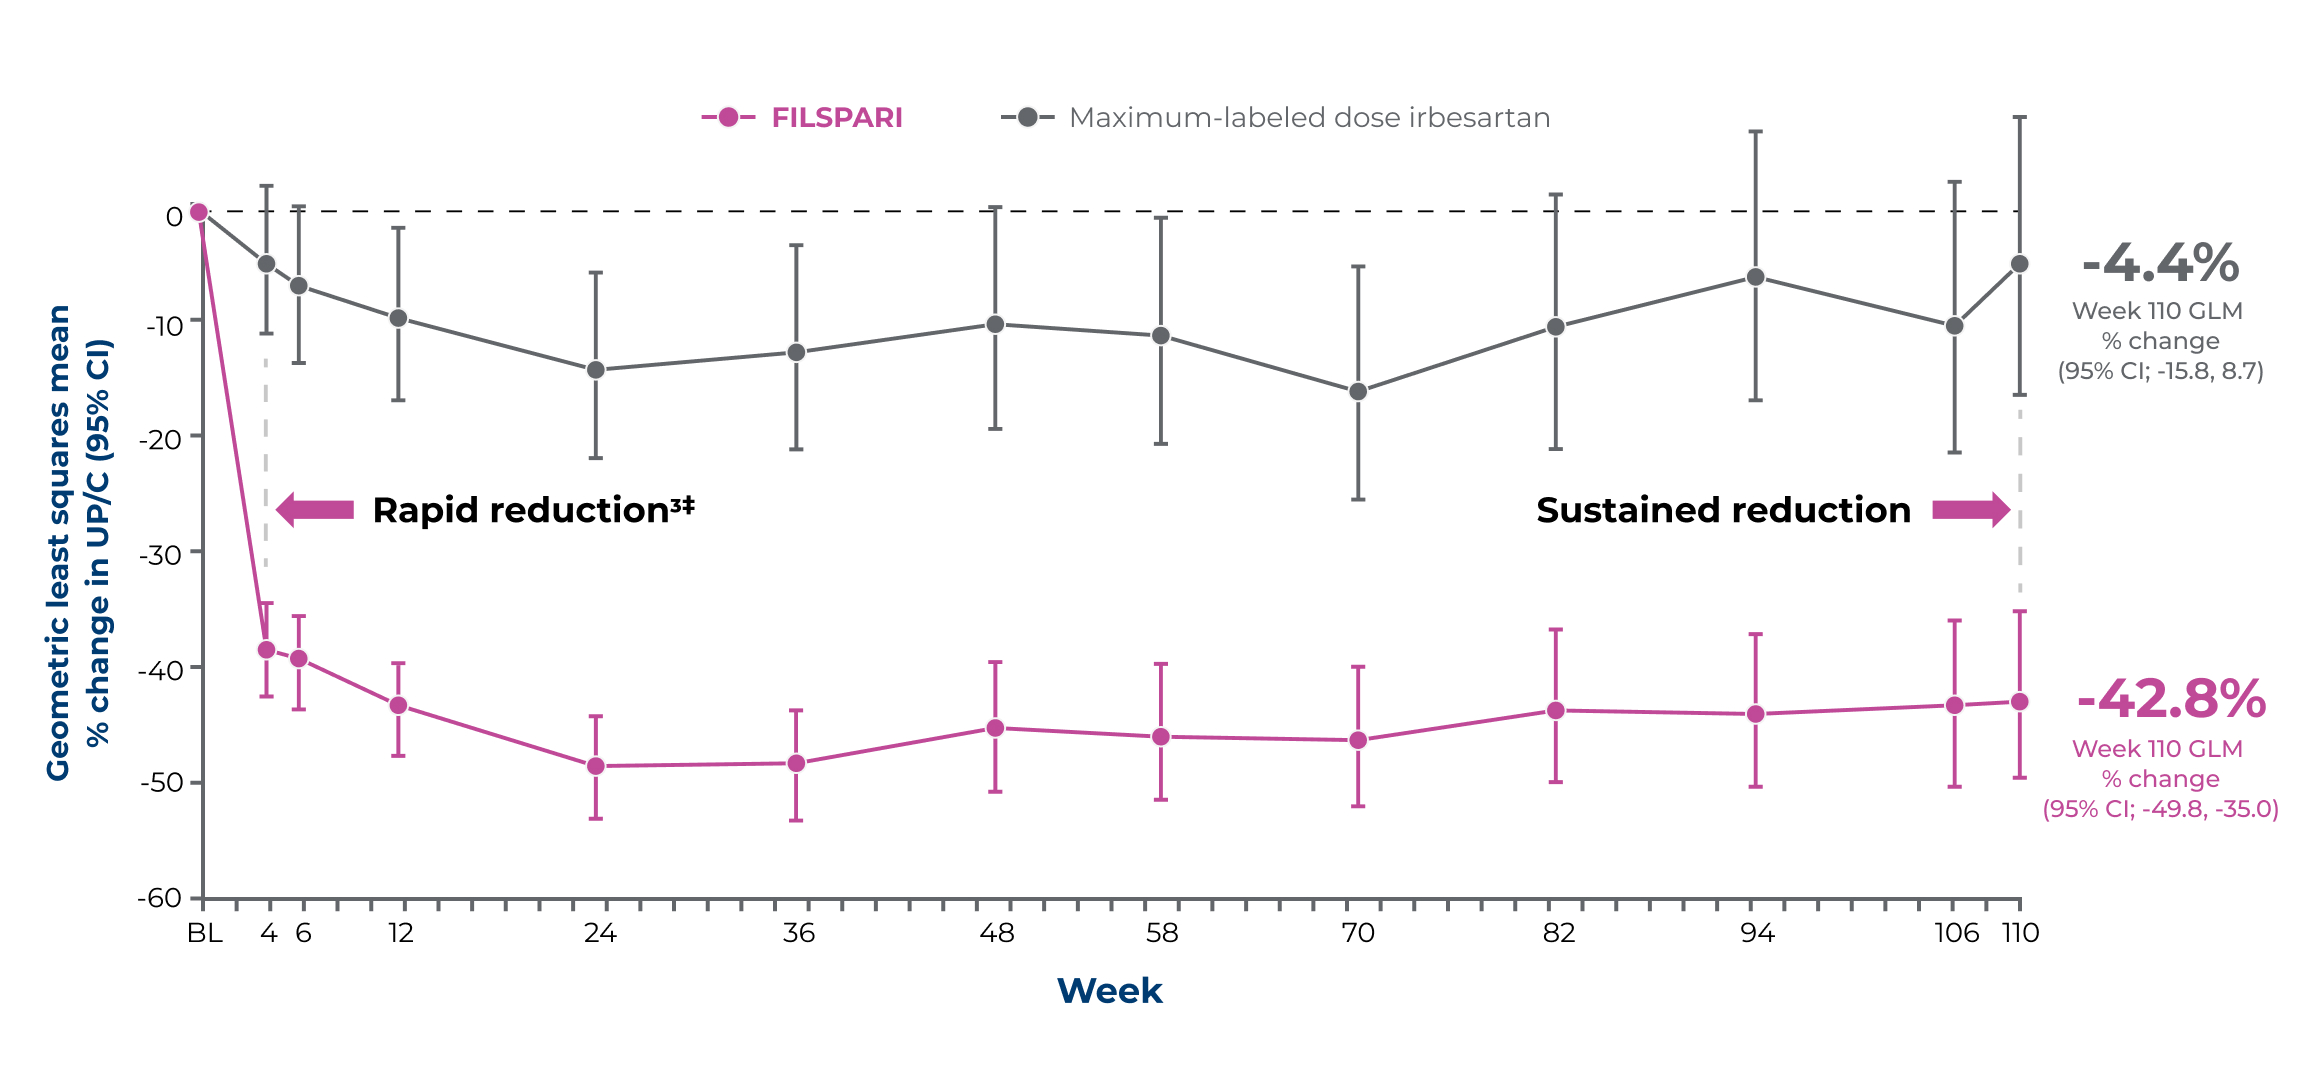
Adapted from Rovin, et al. 20232
Overall small differences in diastolic blood pressure were reported from baseline to Week 110 with FILSPARI and maximum-labeled dose irbesartan2,6§
Under the hierarchical testing procedure, this study did not formally test the statistical hypotheses for other pre-specified secondary efficacy endpoints, as significance was narrowly missed for the eGFR total slope. For these and other efficacy endpoints, nominal 95% CIs are presented2
Significantly slower rates of eGFR decline2*,**
FILSPARI significantly slowed the rate of eGFR decline vs maximum‑labeled dose irbesartan2**
eGFR by visit to Week 1142
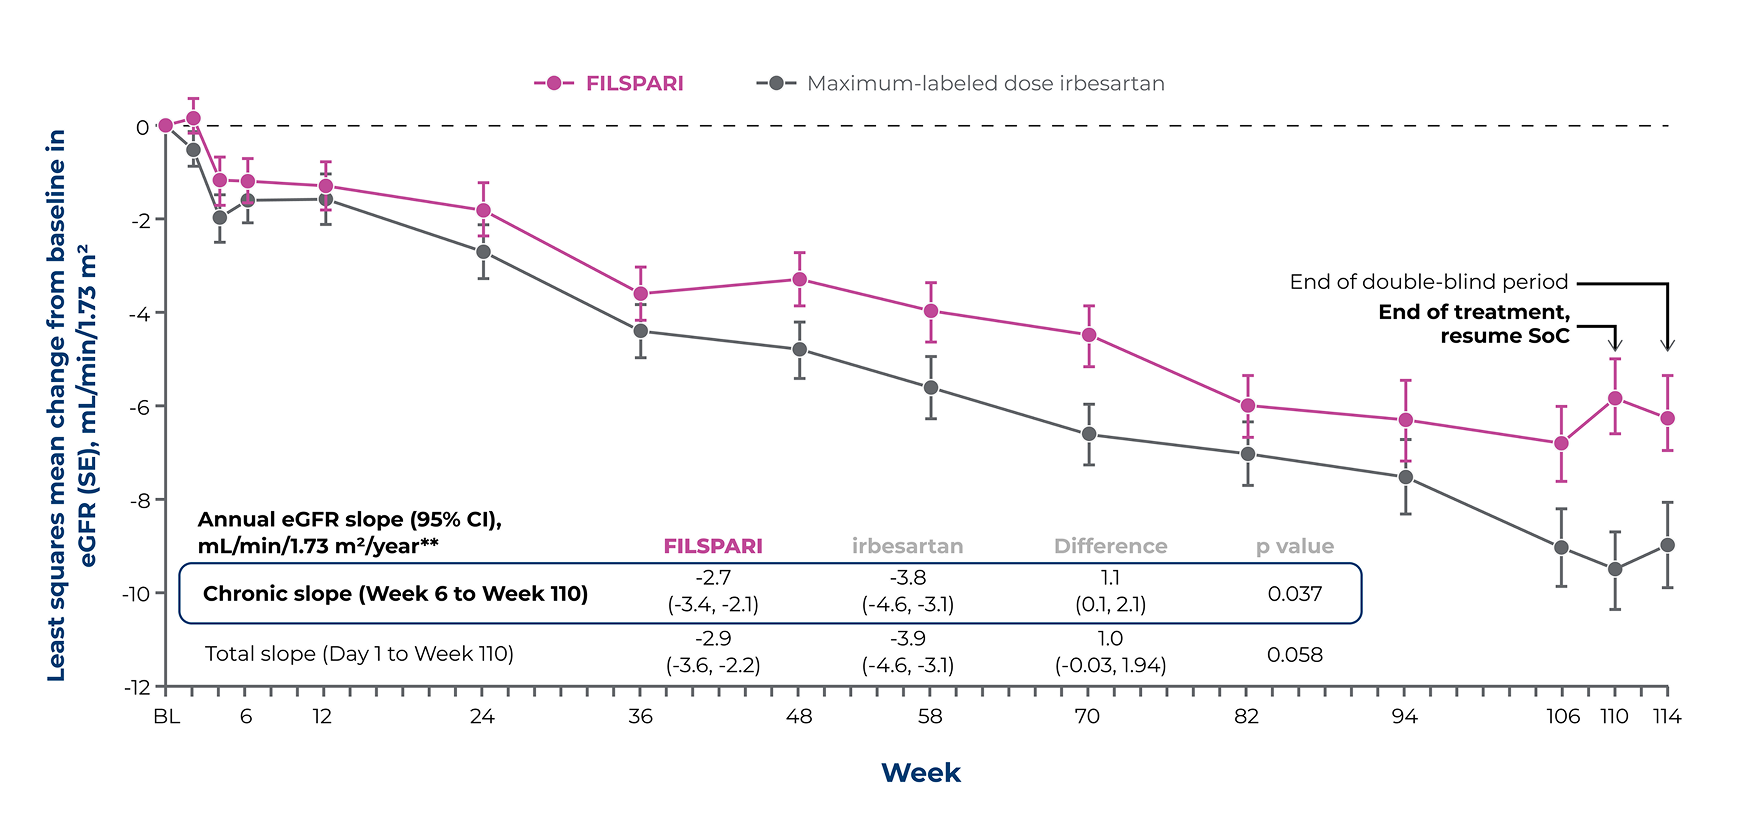
Baseline eGFR, mL/min/1.73 m2, mean (SD): FILSPARI: 56.8 (24.3) irbesartan: 57.1 (23.6)
Adapted from Rovin, et al. 20232
Absolute difference in change in eGFR from baseline to Week 110:2
3.7
mL/min/1.73 m2
(95% CI; 1.5, 6.0)
Least squares mean change in eGFR from baseline to Week 1102

FILSPARI
-5.8
mL/min/1.73 m2
(95% CI; -7.4, -4.2)
VS

maximum-labeled dose irbesartan
-9.5
mL/min/1.73 m2
(95% CI; -11.2, -7.9)
Under the hierarchical testing procedure, this study did not formally test the statistical hypotheses for other prespecified secondary efficacy endpoints, as significance was narrowly missed for the eGFR total slope. For these and other efficacy endpoints, nominal 95% CIs are presented2
Higher rates of proteinuria remission2,6*
FILSPARI increased the rates of proteinuria remission vs maximum-labeled dose irbesartan2,6
Proportion of patients achieving complete or partial proteinuria remission at any point up to Week 1102,6
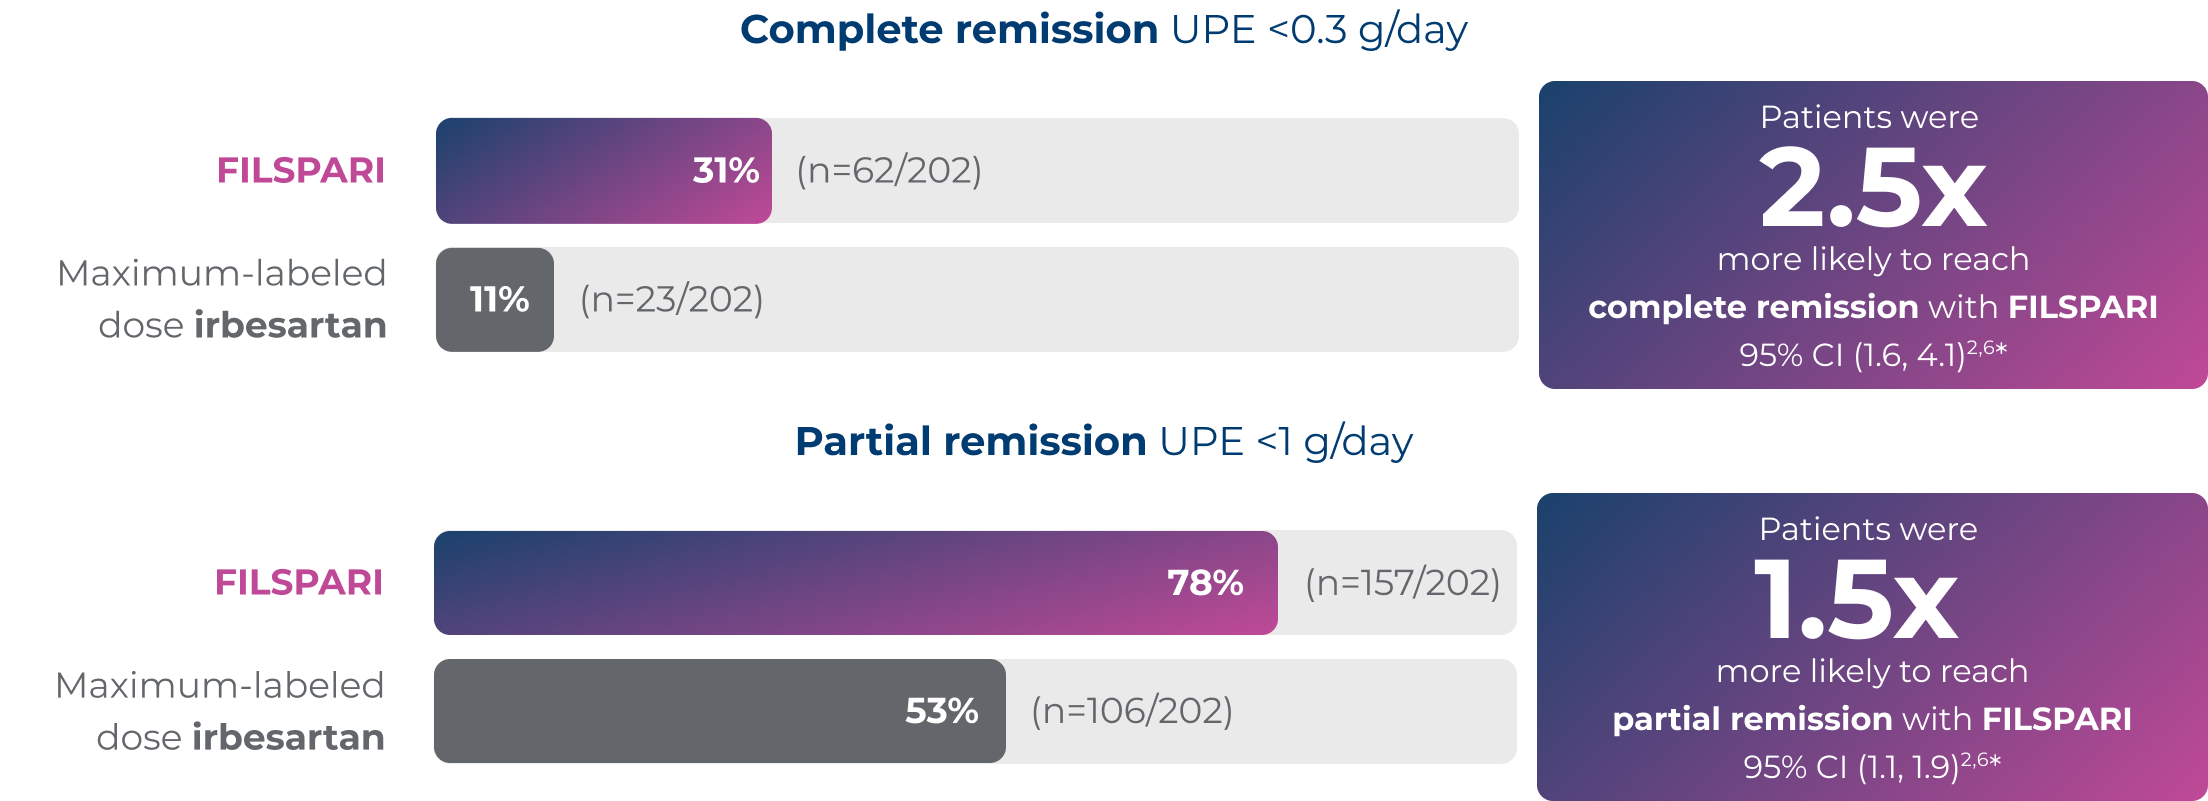
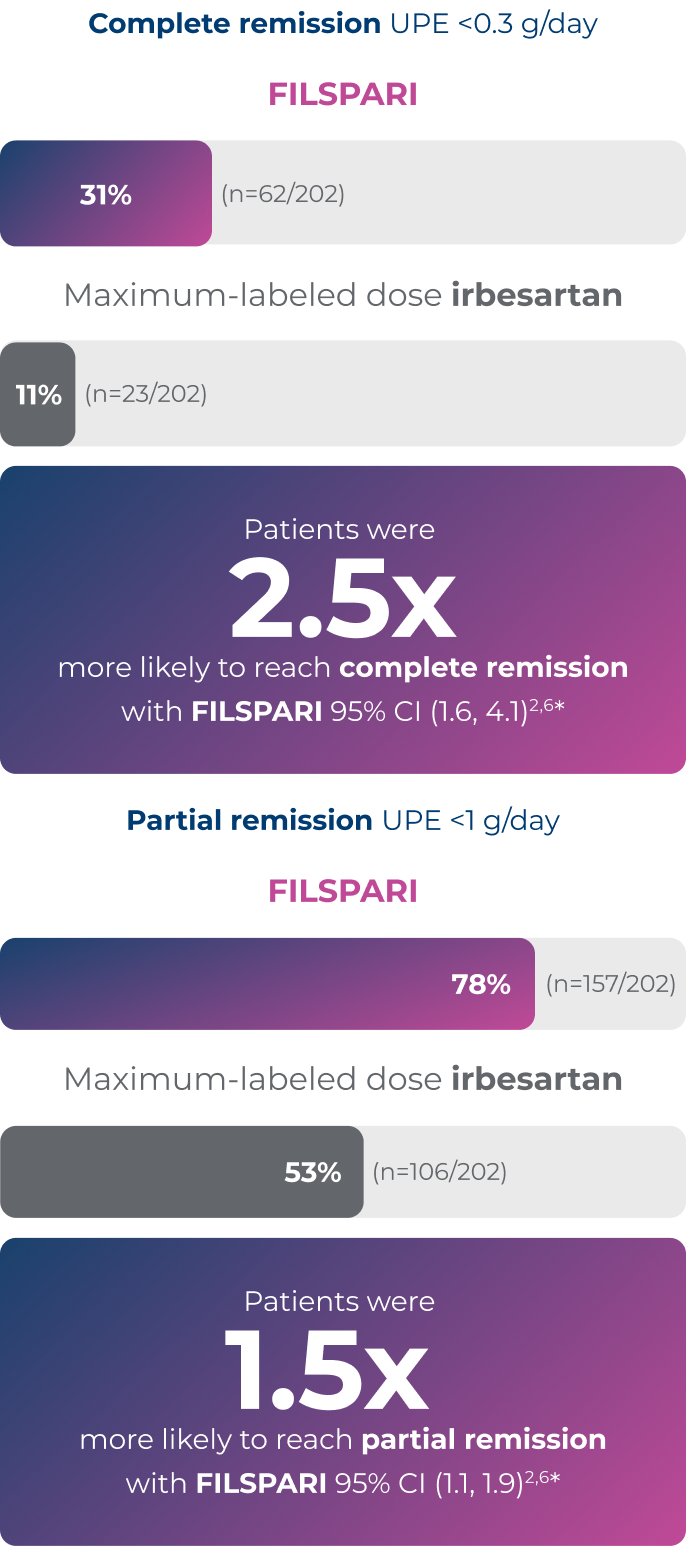
Adapted from Rovin, et al. 20232
Under the hierarchical testing procedure, this study did not formally test the statistical hypotheses for other prespecified secondary efficacy endpoints, as significance was narrowly missed for the eGFR total slope. For these and other efficacy endpoints, nominal 95% CIs are presented2
Have we sparked your interest?
To learn more about FILSPARI please contact: medinfo@viforpharma.com
References & footnotes

Footnotes
*vs maximum-labeled dose irbesartan2
†Geometric least squares mean ratio; 95% CI, 0.51, 0.693
‡An interim analysis was undertaken after the first 280 patients had undergone the Week 36 visit. A significant reduction in UP/C was seen as early as Week 4 and maintained at Week 6, 12, 24, and 36, p<0.0001 at each week until Week 36. The improvement in proteinuria reduction was sustained through Week 1102,3
§In the PROTECT clinical trial, higher rates of hypotension were reported with FILSPARI than maximum-labeled dose irbesartan, 13% vs 4% respectively2
**Chronic slope. Key secondary endpoints included chronic eGFR slope (rate of eGFR change over Week 6 to Week 110) and total eGFR slope (Day 1–Week 110) over the full double-blind treatment period. Chronic slope for FILSPARI vs maximum-labeled dose irbesartan was -2.7 vs -3.8 mL/min/1.73 m2 per year, respectively; difference, 1.1 mL/min/1.73 m2 per year; 95% CI, 0.1, 2.1; p=0.037. Total slope for FILSPARI vs maximum-labeled dose irbesartan was
-2.9 vs -3.9 mL/min/1.73 m2 per year, respectively; difference, 1.0 mL/min/1.73 m2 per year; 95% CI, -0.03, 1.94; p=0.0582
Abbreviations
ACEi, angiotensin-converting enzyme inhibitor; ARB, angiotensin II receptor blocker; BMI, body mass index; BL, baseline; BP, blood pressure; CI, confidence interval; eGFR, estimated glomerular filtration rate; EMA, European Medicines Agency; FDA, US Food and Drug Administration; GLM, geometric least squares mean; IgA, immunoglobulin A; IgAN, immunoglobulin A nephropathy; IQR, interquartile range; MoA, mechanism of action; OLE, open-label extension; RASi, renin-angiotensin system inhibitor; SD, standard deviation; SE, standard error; SoC, standard of care; UP/C, urine protein-to-creatinine ratio; UPE, urine protein excretion
References
- FILSPARI. EU SmPC. April 2024.
- Rovin B, et al. Efficacy and safety of sparsentan versus irbesartan in patients with IgA nephropathy (PROTECT): 2-year results from a randomised, active-controlled, phase 3 trial. Lancet. 2023;402(10417):2077–90.
- Heerspink HJL, et al. Sparsentan in patients with IgA nephropathy: a prespecified interim analysis from a randomised, double-blind, active-controlled clinical trial. Lancet. 2023;401(10388):1584–94.
- Campbell KN, et al. Practical Considerations for the Use of Sparsentan in the Treatment of Patients with IgAN in Clinical Practice. Int J Nephrol Renovasc Dis. 2023;16:281–91
- PROTECT ClinicalTrials.gov: http://clinicaltrials.gov/ct2/show/NCT03762850 (Date accessed: January 2025).
- Rovin B, et al. Efficacy and safety of sparsentan versus irbesartan in patients with IgA nephropathy (PROTECT): 2-year results from a randomised, active-controlled, phase 3 trial. Lancet. 2023;402(10417):2077–90 [Suppl Appendix].
- Heerspink HJL, et al. Sparsentan in patients with IgA nephropathy: a prespecified interim analysis from a randomised, double-blind, active-controlled clinical trial. Lancet. 2023;401(10388):1584–6. 94 [Suppl Appendix].

Filspari is contraindicated during pregnancy. Filspari treatment must only be initiated in women of childbearing potential when the absence of pregnancy has been verified. Women of childbearing potential have to use effective contraception during and up to 1 month after treatment has stopped.
This medicinal product has been granted a conditional marketing authorization by the European Commission.
▼ This medicinal product is subject to additional monitoring. This will allow identification of new safety information. This SmPC may be updated from time to time as necessary. Healthcare professionals are asked to report any suspected adverse reactions. Adverse events should also be reported to CSL Vifor at safety@viforpharma.com
Vifor France. 100–101 Terrasse Boieldieu, Tour Franklin La Défense 8, 92042 Paris La Défense Cedex, France
Date of preparation: April 2024 | API job number: HQ-SPT-2400059
Vifor France. 100–101 Terrasse Boieldieu, Tour Franklin La Défense 8, 92042 Paris La Défense Cedex, France
Date of preparation: April 2024 | API job number: HQ-SPT-2400059
HQ-SPT-2500002 | Date of preparation: February 2025